
Elbow fractures in ChildrenGãy xương khuỷu tay ở trẻ em
Radiology department, Rijnland Hospital Leiderdorp, the Netherlands.Khoa Chẩn đoán hình ảnh, Bệnh viện Rijnland Leiderdorp, Hà Lan.
Ngày đăng / cập nhật: 2008-12-01
Bản gốc trên radiologyassistant.nl ↗ · tải về lúc 2026-11-19 20:19 · bản dịch máy có chuẩn hóa thuật ngữ chẩn đoán hình ảnh
Elbow fractures are the most common fractures in children.
The assessment of the elbow can be difficult because of the changing anatomy of the growing skeleton and the subtility of some of these fractures.
In this review important signs of fractures and dislocations of the elbow will be discussed.
Before reading this article you can try one of the cases in the menubar.
You can test your knowledge on pediatric elbow fractures with these interactive cases.
On some of the images you can click to get a larger view. This does not work for the iPhone application
If you want to use images in a presentation, please mention the Radiology Assistant.Gãy xương khuỷu là loại gãy xương thường gặp nhất ở trẻ em.
Việc đánh giá khuỷu tay có thể khó khăn do sự thay đổi giải phẫu của bộ xương đang phát triển và sự tinh tế của một số loại gãy này.
Trong bài tổng quan này, các dấu hiệu quan trọng của gãy xương và trật khớp khuỷu sẽ được thảo luận.
Trước khi đọc bài viết này, bạn có thể thử một trong các trường hợp trong thanh thực đơn.
Bạn có thể kiểm tra kiến thức của mình về gãy xương khuỷu ở trẻ em với những trường hợp tương tác này.
Trên một số hình ảnh, bạn có thể nhấp để có chế độ xem lớn hơn. Điều này không hoạt động đối với ứng dụng iPhone
Nếu bạn muốn sử dụng hình ảnh trong một bài thuyết trình, vui lòng đề cập đến Trợ lý X quang.
Fracture mechanismCơ chế gãy
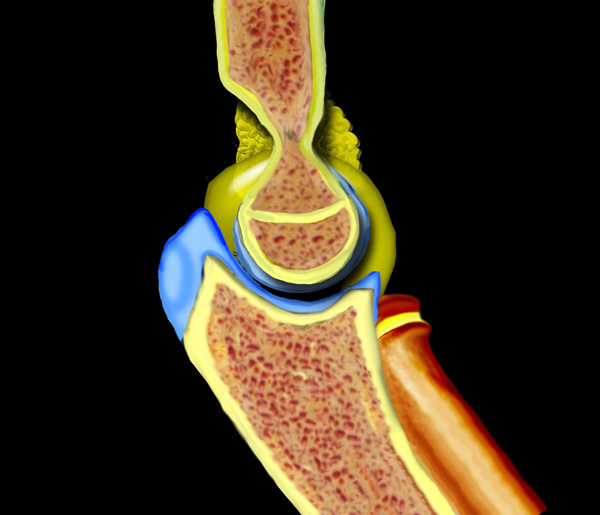
HyperextensionTăng ngoại lực
Injury to the elbow joint is usely the result of hyperextension or extreme valgus due to a fall on the outstretched arm.
Scroll through the images on the left to see how hyperextension leads to a supracondylar fracture.
The hemarthros will result in a displacement of the anterior fat pad upwards and the posterior fat backwards.
Tổn thương khớp khuỷu là hậu quả của việc duỗi quá mức hoặc quá mức do ngã trên cánh tay duỗi ra.
Cuộn qua các hình ảnh bên trái để xem làm thế nào tăng duỗi dẫn đến gãy xương trên lồi cầu.
Các khớp bán phần sẽ dẫn đến sự dịch chuyển của lớp mỡ phía trước lên trên và mỡ phía sau về phía sau.
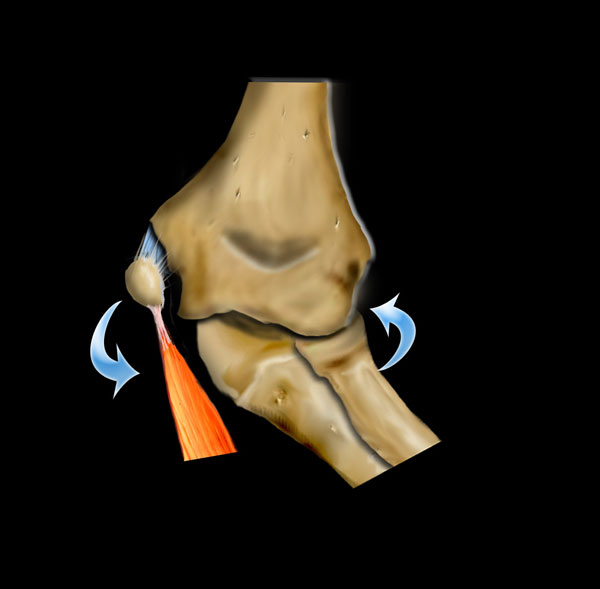
Extreme valgusCực valgus
The other important fracture mechanism is extreme valgus of the elbow.
The normal elbow already has a valgus positioning.
When a child falls on the outstrechted arm, this can lead to extreme valgus.
On the lateral side this can result in a dislocation or a fracture of the radius with or without involvement of the olecranon.
When the forces have more effect on the humerus, the extreme valgus will result in a fracture of the lateral condyle.
On the medial side the valgus force can lead to avulsion of the medial epicondyle.
Sometimes the medial epicondyl becomes trapped within the joint.
Because of the valgus position of the normal elbow an avulsion of the lateral epicondyle will be uncommon.
Cơ chế gãy xương quan trọng khác là gãy quá mức khớp khuỷu.
Khuỷu tay bình thường đã có tư thế valgus.
Khi một đứa trẻ ngã trên cánh tay không được bảo vệ, điều này có thể dẫn đến valgus cực độ.
Ở bên ngoài, điều này có thể dẫn đến trật khớp hoặc gãy xương quay có hoặc không có sự tham gia của mỏm khuỷu.
Khi các lực tác động nhiều hơn lên xương cánh tay, sự quá mức của valgus sẽ dẫn đến gãy lồi cầu ngoài.
Ở phía trong, lực valgus có thể dẫn đến sự nhổ của lồi cầu trong.
Đôi khi lồi cầu trong bị mắc kẹt trong khớp.
Do vị trí valgus của khuỷu tay bình thường nên việc nhổ lồi cầu ngoài sẽ không phổ biến.
Radiological InterpretationGiải thích X quang

Methodical reviewĐánh giá phương pháp
When looking at radiographs of the elbow after trauma a methodical review of the radiographs is needed .
You should ask yourself the following important questions.
Is there a sign of joint effusion?
After trauma this almost always indicates the presence of hemarthros due to a fracture (either visible or occult).Khi xem xét các phim X quang của khuỷu tay sau chấn thương, cần phải xem xét lại các phim Xquang một cách có phương pháp.
Bạn nên tự hỏi mình những câu hỏi quan trọng sau đây.
Có dấu hiệu của tràn dịch khớp không?
Sau chấn thương, dấu hiệu này hầu như luôn cho thấy sự hiện diện của khớp bị gãy (có thể nhìn thấy hoặc ẩn).
Is there a normal alignment between the bones?
In children dislocations are frequent and can be very subtle.Có sự liên kết bình thường giữa các xương không?
Ở trẻ em trật khớp thường xuyên và có thể rất khó phát hiện.
Are the ossification centres normal?
Is the piece of bone that you're looking at a normal ossification centre and is this ossification centre in the normal position. .
Look especially for the position of the radial epiphysis and the medial epicondyle (figure).Các trung tâm cốt hóa có bình thường không?
Là mảnh xương mà bạn đang nhìn vào một trung tâm cốt hóa bình thường và trung tâm cốm hóa này ở vị trí bình thường.
Đặc biệt chú ý vị trí của mỏm trên lồi cầu quay và mỏm giữa lồi cầu trong (hình).
Is there a subtle fracture?
Some of the fractures in children are very subtle.
So you need to be familiar with the typical picture of these fractures. .
Có gãy xương kín đáo không?
Một số loại gãy xương ở trẻ em rất khó phát hiện.
Vì vậy bạn cần phải làm quen với hình ảnh điển hình của những loại gãy xương này.
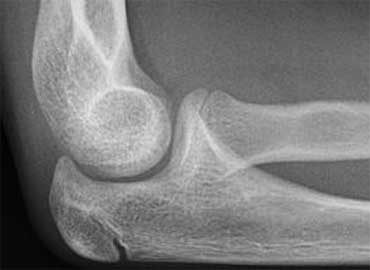 Normal anterior fat pad.Mấu mỡ trước bình thường.
Fat Pad Sign and Joint effusionDấu hiệu Fat Pad và tràn dịch khớp
Normally on a lateral view of the elbow flexed in 90? a fat pad is seen on the anterior aspect of the joint .
This is normal fat located in the joint capsule.
On the posterior side no fat pad is seen since the posterior fat is located within the deep intercondylar fossa.Thông thường, khi gập khuỷu 90 độ, một tấm mỡ được nhìn thấy ở mặt trước của khớp.
Đây là mỡ bình thường nằm trong bao khớp.
Ở phía sau không thấy đệm mỡ vì mỡ phía sau nằm trong hố liên lồi cầu sâu.
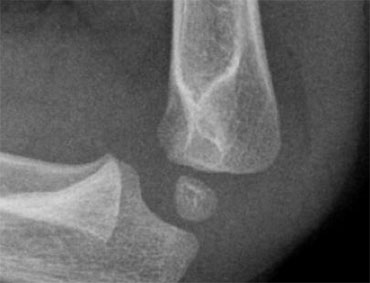 Positive fat pad sign both anteriorly as well as posteriorly.Dấu hiệu mỡ dương tính cả trước và sau.
Positive fat pad sign
Distention of the joint will cause the anterior fat pad to become elevated and the posterior fat pad to become visible.
An elevated anterior lucency or a visible posterior lucency on a true lateral radiograph of an elbow flexed at 90? is described as a positive fat pad sign (figure).Dấu hiệu mỡ dương tính
Sự căng giãn của khớp sẽ làm cho phần mỡ phía trước bị nâng lên và phần mỡ phía sau có thể nhìn thấy được.
Tăng độ sáng phía trước hoặc tăng độ sáng phía sau có thể nhìn thấy trên phim X quang thực sự của khuỷu tay gấp 90 độ? được mô tả là dấu hiệu mỡ dương tính (hình).
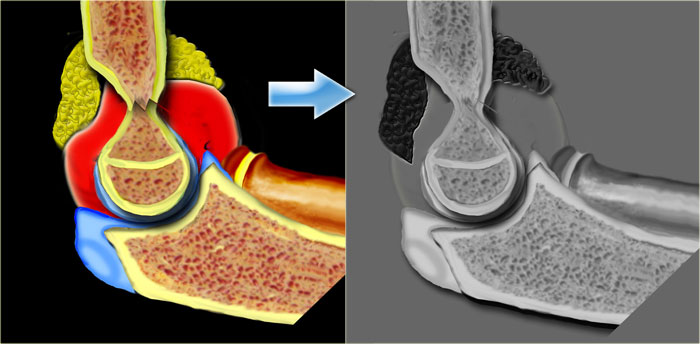
Hemarthros results in an upward displacement of the anterior fat pad and a backward displacement the posterior fat. Hemarthros dẫn đến sự dịch chuyển lên trên của lớp mỡ phía trước và dịch chuyển ra sau lớp mỡ phía sau.
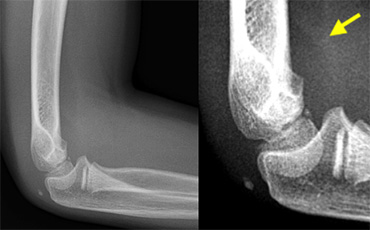 Positive Anterior Fat Pad sign. On digital radiographs you may need to adjust the window width and level to appreciate this. No fracture was visible on the X-rays.Dấu hiệu Pad mỡ phía trước dương tính Trên phim X quang kỹ thuật số, bạn có thể cần phải điều chỉnh độ rộng và mức độ cửa sổ để đánh giá điều này. Không có vết nứt nào có thể nhìn thấy trên phim X-quang.
Positive fat pad sign (2)
Any elbow joint distention either hemorrhagic, inflammatory or traumatic gives rise to a positive fat pad sign.
If a positive fat pad sign is not present in a child, significant intra-articular injury is unlikely.
A visible fat pad sign without the demonstration of a fracture should be regarded as an occult fracture.
These patients are treated as having a nondisplaced fracture with 2 weeks splinting.
Skaggs et al repeated x-rays after three weeks in patients with a positive posterior fat pad sign but no visible fracture.
They found evidence of fracture in 75%.
They concluded that in trauma displacement of the posterior fat pad is virtually pathognomonic of the presence of a fracture.
Displacement of the anterior fat pad alone however can occur due to minimal joint effusion and is less specific for fracture.
Notice that the elbow is not positioned well.
Try to find out what went wrong in the chapter on positioning.Dấu hiệu mỡ dương tính (2)
Bất kỳ sự chướng khớp khuỷu nào xuất huyết, viêm hoặc chấn thương đều làm tăng dấu hiệu dấu mỡ dương tính.
Nếu không có dấu hiệu dấu mỡ dương tính ở trẻ, tổn thương nội khớp đáng kể là không thể.
Một dấu hiệu có thể nhìn thấy được mà không có biểu hiện gãy xương nên được coi là một gãy xương ẩn.
Những bệnh nhân này được điều trị như gãy xương không di lệch với nẹp 2 tuần.
Skaggs và cộng sự. X-quang lặp lại sau ba tuần ở những bệnh nhân có dấu hiệu mỡ phía sau dương tính nhưng không có gãy xương nhìn thấy được.
75% có dấu hiệu gãy xương.
Họ kết luận rằng trong chấn thương, sự di lệch của lớp mỡ phía sau hầu như là đặc trưng của sự hiện diện của gãy xương.
Tuy nhiên, sự dịch chuyển của lớp mỡ phía trước có thể xảy ra do tràn dịch khớp tối thiểu và ít đặc hiệu hơn đối với gãy xương.
Lưu ý rằng khuỷu tay không được đặt đúng vị trí.
Cố gắng tìm hiểu những gì đã sai trong chương về định vị.
AlignmentLiên kết
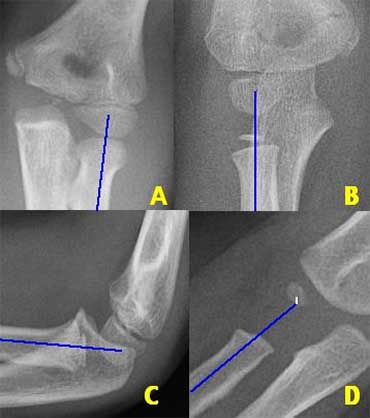
There are two important lines which help in the diagnosis of dislocation and fracture .
These are the Radiocapitellar line and the Anterior humeral line.Có hai đường mổ quan trọng giúp chẩn đoán trật khớp và gãy xương.
Đây là đường Radiocapitellar và đường trước xương cánh tay.
Radiocapitellar line
A line drawn through the centre of the radial neck should pass throught the centre of the capitellum, whatever the positioning of the patient, since the radius articulates with the capitellum (figure).
In dislocation of the radius this line will not pass through the centre of the capitellum.
On the left we see, that the radiocapitellar line goes through centre of the capitellum on every radiogragh even though C and D are not well positioned.
Notice supracondylar fracture in B.
Đường kính quai đầu
Một đường thẳng được vẽ qua trung tâm của cổ quay phải đi qua trung tâm đầu, bất kể vị trí của bệnh nhân, vì xương quay khớp với đầu.
Khi trật khớp xương quay, đường này sẽ không đi qua trung tâm của đầu xương.
Ở bên trái, chúng ta thấy rằng đường cong này đi qua trung tâm của đầu trên mỗi cơ quan mặc dù C và D không được định vị tốt.
Lưu ý gãy trên lồi cầu ở B.
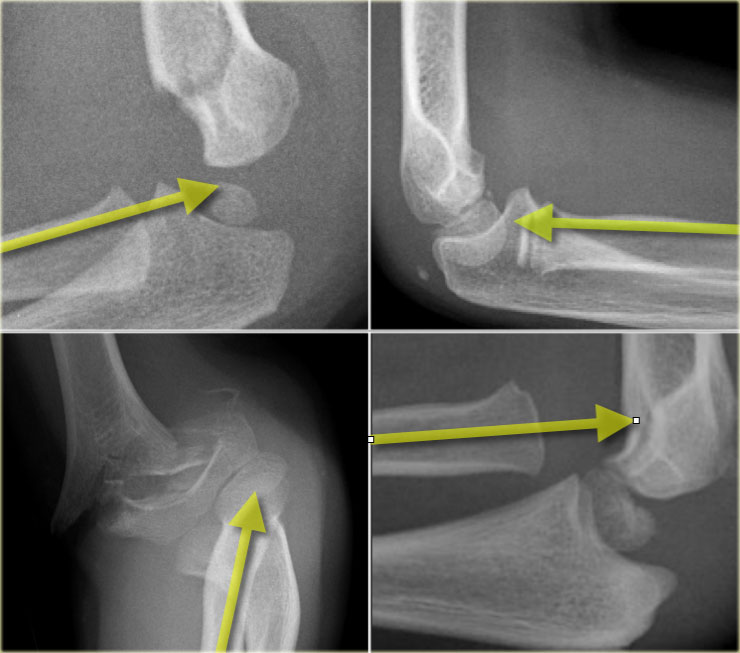
On the left more examples of the radiocapitellar line.
The right lower image shows an obvious dislocation of the radius.Bên trái là thêm các ví dụ về đường cong ống tai ngoài.
Hình ảnh dưới bên phải cho thấy trật khớp rõ ràng của xương quay.
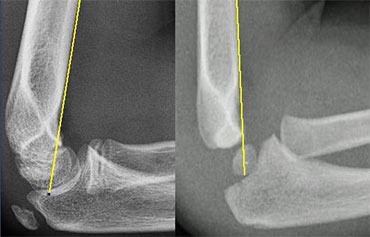 Radiographs of elbows at different ages. The Anterior Humeral line goes through the middle third of the capitellum .Chụp X quang khuỷu tay ở các độ tuổi khác nhau. Đường humeral phía trước đi qua một phần ba giữa của capitellum.
Anterior humeral line.
A line drawn on a lateral view along the anterior surface of the humerus should pass through the middle third of the capitellum..
This line is called the Anterior Humeral line .
In cases of a supracondylar fracture the anterior humeral line usually passes through the anterior third
of the capitellum or in front of the capitellum due to posterior bending of the distal humeral fragment.Đường cánh tay trước. Trên phim nghiêng, đường kẻ dọc theo mặt trước xương cánh tay đi qua một phần ba giữa của chỏm con xương cánh tay. Trong gãy trên lồi cầu, đường này thường đi qua một phần ba trước hoặc nằm trước chỏm con do mảnh đầu xa xương cánh tay gập ra sau.
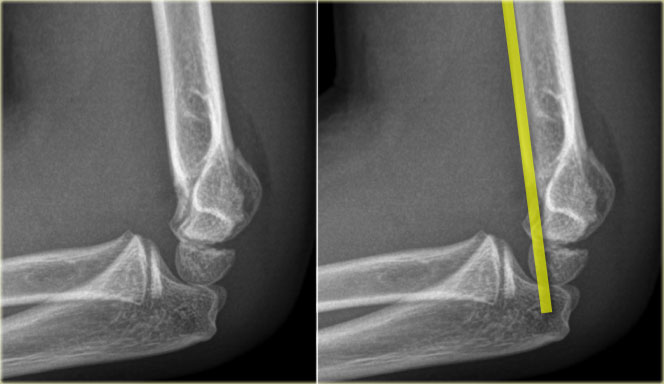
On the left the anterior humeral line passes through the anterior third of the capitellum.
This indicates that the condyles are displaced dorsally (i.e. supracondylar fracture).Ở bên trái, đường trước xương cánh tay đi qua phần trước của đầu.
Điều này chỉ ra rằng các lồi cầu bị di lệch về phía lưng (tức là gãy trên lồi cầu).
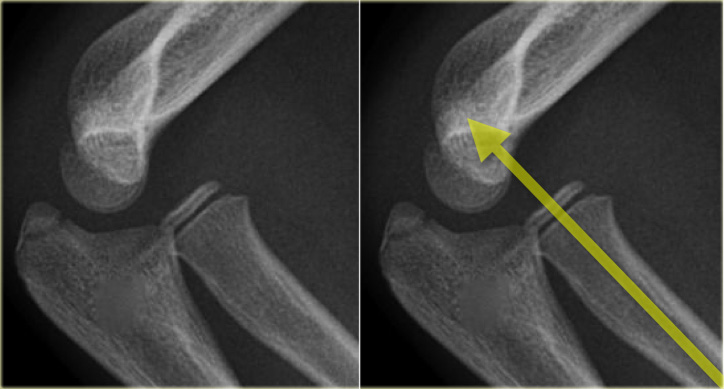
First study the images on the left.
Then continue reading.
The radiocapitellar line ends above the capitellum.
This means that the radius is dislocated.
Did you also notice the olecranon fracture?
Whenever the radius is fractured or dislocated, always study the ulna carefully.Đầu tiên nghiên cứu hình ảnh bên trái.
Sau đó tiếp tục đọc.
Đường chẩm đầu ra ngoài kết thúc phía trên chỏm đầu.
Điều này có nghĩa là xương quay bị trật.
Bạn cũng có nhận thấy gãy xương mỏm khuỷu không?
Bất cứ khi nào xương quay bị gãy hoặc trật khớp, luôn luôn nghiên cứu xương trụ cẩn thận.
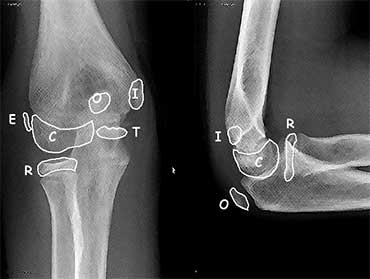
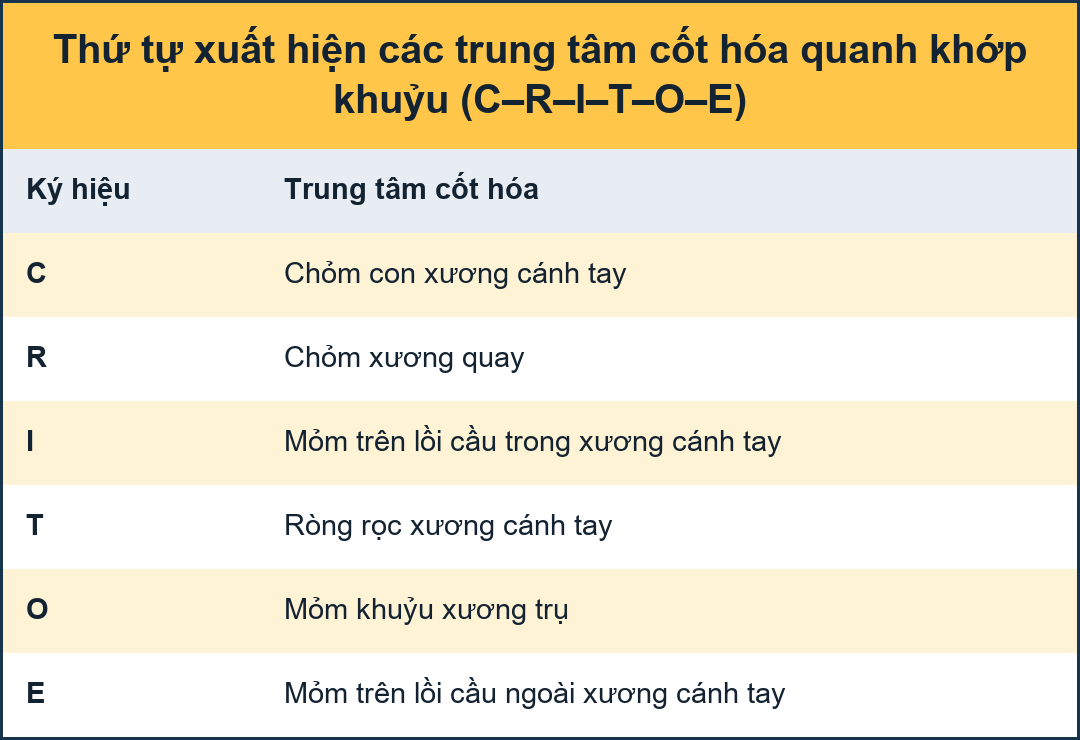 The order of appearance of the ossification centres is specified in the mnemonic C-R-I-T-O-E.Thứ tự xuất hiện của các trung tâm cốt hóa được chỉ định trong C-R-I-T-O-E ghi nhớ.
Ossification centresTrung tâm thẩm thấu
There are 6 ossification centres around the elbow joint.
They appear and fuse to the adjacent bones at different ages.
It is important to know the sequence of appearance since the ossification centers always appear in a strict order.
This order of appearance is specified in the mnemonic C-R-I-T-O-E
(Capitellum - Radius - Internal or medial epicondyle - Trochlea - Olecranon - External or lateral epicondyle).
The ages at which these ossification centres appear are highly variable and differ between individuals.
It is not important to know these ages, but as a general guide you could remember 1-3-5-7-9-11 years.Có 6 trung tâm cốt hóa xung quanh khớp khuỷu.
Chúng xuất hiện và hợp nhất với các xương liền kề ở các độ tuổi khác nhau.
Điều quan trọng là phải biết trình tự xuất hiện vì các trung tâm cốt hóa luôn xuất hiện theo một thứ tự nghiêm ngặt.
Thứ tự xuất hiện này được chỉ định trong C-R-I-T-O-E (Capitellum - Radius - Lồi lồi cầu trong hoặc trong - Trochlea - Olecranon - Lồi cầu ngoài hoặc ngoài).
Độ tuổi xuất hiện các trung tâm cốt hóa rất khác nhau và khác nhau giữa các cá thể.
Biết được những lứa tuổi này không quan trọng, nhưng như một hướng dẫn chung, bạn có thể nhớ 1-3-5-7-9-11 tuổi.
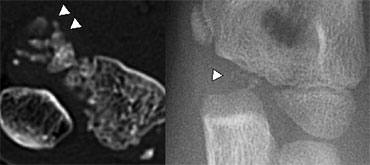 Fragmented appearance of the Trochlea in 2 different children.Hình thái mấu chuyển của mấu chốt ở 2 trẻ khác nhau.
The Trochlea has two or more ossification centres which can give the trochlea a fragmented appearance.Trochlea có hai hoặc nhiều trung tâm cốt hóa có thể tạo ra sự xuất hiện của các mảnh vỡ.
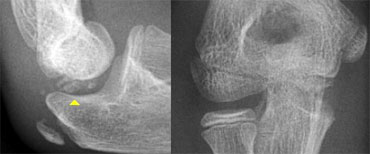 Trochlea ossification-fragments simulate loose bodies in the jointPhẫu thuật cốt hóa mấu chuyển-các mảnh vỡ mô phỏng các thể lỏng lẻo trong khớp
On a lateral view the trochlea ossifications may project into the joint.
They should not be mistaken for loose intra-articular bodies (arrow).Trên phim nghiêng, các mấu chuyển xương có thể lồi vào khớp.
Không nên nhầm lẫn chúng với các thể lỏng lẻo trong khớp (mũi tên).
RadiographyChụp X-quang
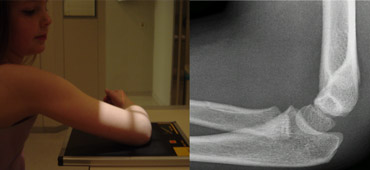 Shoulder higher than elbow. Radius and Capitellum project on to the ulna.Vai cao hơn khuỷu tay, xương quay và xương đòn chĩa về phía xương trụ.
Common errors in positioningCác lỗi thường gặp trong định vị
Error 1: Shoulder higher than elbow
For a true lateral view the shoulder should be at the level of the elbow.
If the shoulder is higher than the elbow, the radius and capitellum will project on the ulna.
Lỗi 1: Vai cao hơn khuỷu tay
Để có góc nhìn bên thực sự, vai phải ngang bằng khuỷu tay.
Nếu vai cao hơn khuỷu tay, xương quay và xương đầu sẽ nằm trên xương trụ.


The solution is either to lift the examination table which will lift the elbow or to lower the shoulder by placing the patient on a smaller chair.Giải pháp là nâng bàn khám để nâng khuỷu tay hoặc hạ thấp vai bằng cách đặt bệnh nhân lên một chiếc ghế nhỏ hơn.
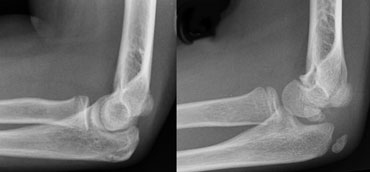 LEFT: Slight endorotation of the humerus due to a low position of the wrist. RIGHT: More endorotation due to malpositioning.Trái: Xương cánh tay xoay trong nhẹ do cổ tay đặt thấp. Phải: Xoay trong nhiều hơn do tư thế đặt sai.
Error 2: Wrist lower than elbow
On the left two examples of a 'low wrist positioning' leading to rotation of the humerus.
The low position of the wrist leads to endorotation of the humerus.
The lateral structures like the capitellum and the radius will move anteriorly, while a medial structure like the medial epicondyle will move posteriorly.Lỗi 2: Cổ tay thấp hơn khuỷu tay
Ở bên trái hai ví dụ về 'vị trí cổ tay thấp' dẫn đến xoay xương cánh tay.
Vị trí thấp của cổ tay dẫn đến sự khép kín của xương cánh tay.
Các cấu trúc bên như đầu và xương quay sẽ di chuyển về phía trước, trong khi cấu trúc trong như lồi cầu trong sẽ di chuyển ra phía sau.


The wrist should be higher than the elbow to compensate for the normal valgus position of the elbow.
The hand should be with the 'thumb up'.
Cổ tay phải cao hơn khuỷu tay để bù cho vị trí valgus bình thường của khuỷu.
Bàn tay nên có 'ngón cái lên'.
Elbow fracturesGãy xương khuỷu

Supracondylar fracturesGãy trên lồi cầu
These fractures account for more than 60% of all elbow fractures in children (see Table).
More than 95% of supracondylar fractures are hyperextension type due to a fall on the outstretched hand.
The elbow becomes locked in hyperextension.
The olecranon is pushed into the olecranon fossa causing the anterior humeral cortex to bend and eventually break.
If the force continues both the anterior and posterior cortex will fracture.Những loại gãy này chiếm hơn 60% tổng số gãy xương khuỷu ở trẻ em (xem Bảng).
Hơn 95% gãy trên lồi cầu là loại quá duỗi do ngã trên bàn tay duỗi ra.
Khuỷu tay bị khóa trong tư thế duỗi quá mức.
Mỏm khuỷu bị đẩy vào hố mỏm khuỳu làm cho vỏ xương cánh tay trước bị uốn cong và cuối cùng bị gãy.
Nếu lực tiếp tục cả vỏ não trước và sau sẽ bị gãy.
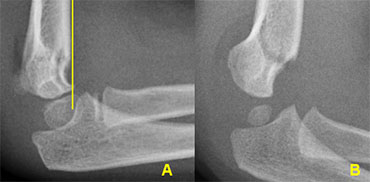 Supracondylar fractures. In A the anterior humeral line passes through the anterior third of the capitellum and in B even more anteriorly. Notice positive posterior fat pad sign in both casesGãy xương siêu tuyến. Trong A, đường humeral phía trước đi qua một phần ba phía trước của capitellum và ở B phía trước thậm chí nhiều hơn. Lưu ý dấu hiệu đệm mỡ phía sau dương tính trong cả hai trường hợp
Supracondylar fractures (2)
If there is only minimal or no displacement these fractures can be occult on radiographs.
The only sign will be a positive fat pad sign.
Usually there is some displacement and the anterior humeral line will not pass through the centre of the capitellum but through the anterior third or even anterior to the capitellum (figure).Gãy trên lồi cầu (2)
Nếu chỉ có ít hoặc không có di lệch, những gãy xương này có thể ẩn trên phim X-quang.
Dấu hiệu duy nhất sẽ là dấu hiệu mỡ dương tính.
Thông thường có một số di lệch và đường trước xương cánh tay sẽ không đi qua trung tâm của đầu mà đi qua phần ba trước hoặc thậm chí trước đầu (hình).
Supracondylar fractures (3)
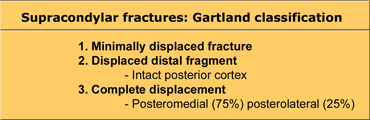
Supracondylar fractures are classified according to Gartland.
Gartland Type I fractures are often difficult to see on X-rays since there is only minimal displacement.
Most of these fractures consist of greenstick or torus fractures.
The only clue to the diagnosis may be a positive fat pad sign.
These patients are treated with casting.Gãy trên lồi cầu (3)
Gãy trên lồi cầu xương cánh tay được phân loại theo Gartland.
Gãy Gartland loại I thường khó nhìn thấy trên X-quang vì chỉ có di lệch tối thiểu.
Hầu hết các loại gãy này đều là gãy sụn viền xanh hoặc gãy torus.
Dấu hiệu duy nhất để chẩn đoán có thể là dấu hiệu mỡ dương tính.
Những bệnh nhân này được điều trị bằng bó bột.
In Gartland type II fractures there is displacement but the posterior cortex is intact.
There may be some rotation. These fractures require closed reduction and some need percutaneous fixation if a long-arm cast does not adequately hold the reduction.Trong gãy Gartland loại II có di lệch nhưng vỏ sau vẫn còn nguyên vẹn.
Có thể có một số trường hợp xoay. Những gãy xương này cần nắn kín và một số cần cố định qua da nếu bó bột cánh tay dài không giữ được nắn chỉnh.
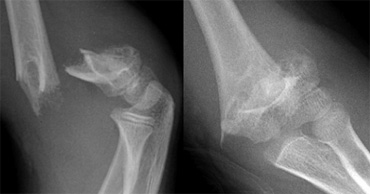 Gartland type III fractureGãy kiểu Gartland III
Gartland type III fractures are completely dislocated and are at risk for malunion and neurovascular complications (figure).
They require reduction by closed or if necessary open means. Stabilisation is maintained with either two lateral pins or medial lateral cross pin technique.Gãy Gartland loại III trật khớp hoàn toàn và có nguy cơ bị biến chứng mạch máu thần kinh và mạch máu thần Kinh (hình).
Chúng cần được nắn chỉnh bằng phương pháp đóng hoặc nếu cần thiết là mở, duy trì sự ổn định bằng hai chân bên hoặc kỹ thuật chốt ngang bên trong.
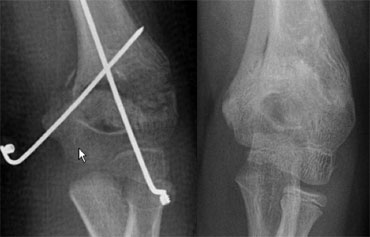 Gartland III fracture with medial-lateral cross pin technique. After reduction there is inadequate correction of medial collaps. After two months there is malunion with cubitus varus deformity.Gãy xương Gartland III với kỹ thuật ghim chéo giữa-bên. Sau khi giảm có sự điều chỉnh không đầy đủ của các vết cắt giữa. Sau hai tháng có sự biến dạng của cubitus varus.
Supracondylar fractures (4)
Malunion will result in the classic 'gunstock' deformity due to rotation or inadequate correction of medial collaps.
Posterolateral displacement of the distal fragment can be associated with injurie to the neurovascular bundle which is displaced over the medial metaphyseal spike.
Nerve injurie almost always results in neuropraxis that resolves in 3-4 months.
Vascular injurie usually results in a pulseless but pink hand.
Conservative management and vascular intervention have the same outcome.
A pulseless and white hand after reduction needs exploration.Gãy trên lồi cầu xương (4)
Sự không liền sẽ dẫn đến biến dạng 'gunstock' cổ điển do xoay hoặc điều chỉnh không đầy đủ các nắp trong.
Sự dịch chuyển sau bên của mảnh xa có thể liên quan đến tổn thương bó mạch thần kinh bị dịch chuyển qua gai xương trong.
Tổn thương thần kinh hầu như luôn dẫn đến các triệu chứng thần kinh tự khỏi trong 3-4 tháng.
Tổn thương mạch máu thường dẫn đến mất mạch nhưng bàn tay hồng.
Điều trị bảo tồn và can thiệp mạch máu có kết quả tương đương nhau.
Bàn tay mất mạch và trắng sau khi nắn chỉnh cần được thăm dò.
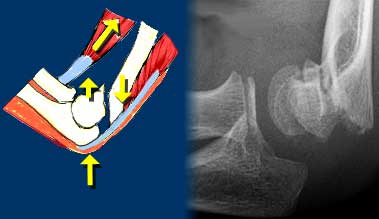 Flexion-type supracondylar fracture caused by direkt impactGãy trên lồi cầu xương ống mềm do va chạm direkt
Supracondylar fractures (5)
Flexion-type fractures are uncommon (5% of all supracondylar fractures).
They are caused by direct impact on the flexed elbow.
Ulnar nerve injury is more common.
Compared to extension types, they are more likely to be unstable, so more likely to require fixation. Gãy trên lồi cầu (5)
Gãy kiểu Flexion không phổ biến (5% trong số tất cả các loại gãy trên lồi cầu).
Chúng được gây ra bởi tác động trực tiếp lên khuỷu tay gấp.
Tổn thương thần kinh trụ thường gặp hơn.
So với các loại mở rộng, chúng có nhiều khả năng không ổn định, do đó có nhiều khả Năng cần phải cố định.

Lateral Condyle fracturesGãy lồi cầu xương bên
This fracture is the second most common distal humerus fracture in children.
They occur between the ages of 4 and 10 years.
These fractures occur when a varus force is applied to the extended elbow.
They tend to be unstable and become displaced because of the pull of the forearm extensors.
Since these fractures are intra-articular they are prone to nonunion because the fracture is bathed in synovial fluid.
Lateral condyle fractures are classified according to Milch. They are Salter-Harris IV epiphysiolysis fractures.
Most are Milch II fractures that travel from the lateral humeral metaphysis above the epiphysis and exit through the lateral crista of the trochlea leading to an unstable humeral ulnar articulation.Đây là loại gãy đầu dưới xương cánh tay phổ biến thứ hai ở trẻ em.
Chúng xảy ra trong độ tuổi từ 4 đến 10 tuổi.
Những gãy xương này xảy ra khi một lực varus được áp vào khuỷu tay.
Chúng có xu hướng không ổn định và bị di lệch do kéo căng các cơ duỗi cẳng tay.
Vì những gãy xương này nằm trong khớp, chúng dễ bị mất kết dính vì gãy xương được ngâm trong dịch khớp.
Gãy lồi cầu xương bên được phân loại theo Milch, đó là gãy đầu dưới xương bàn ngón Salter-Harris IV.
Hầu hết là gãy xương Milch II di chuyển từ xương cánh tay bên trên xương đầu và thóat ra qua màng cứng ngoài của mấu chuyển dẫn đến khớp trụ xương cánh tay không ổn định.

Lateral Condyle fractures (2)
The problem with the Milch-classification is the fact that the fracture fragments are primarily cartilaginous. The fracture line through the cartilage is not visible on radiographs, so the radiographic interpretation concerning classification is difficult.
Treatment strategies are therefore based on the amount of displacement (see Table).
Undisplaced fractures are treated with a long arm cast.
These fractures must be carefully monitored as they have a tendency to displace. At follow up both AP and Oblique views are taken after removal of the cast.
Once displaced fractures consolidate in a malunited position, treatment is difficult and fraught with complications.
For this reason surgical reductions is recommended within the first 48 hours.
Open reduction is indicated for all displaced fractures and those demonstrating joint instability.Gãy lồi cầu xương cánh tay (2)
Vấn đề với phân loại Milch là thực tế là các mảnh gãy chủ yếu là sụn. Đường gãy xuyên qua sụn không nhìn thấy được trên phim X quang, do đó việc giải thích trên phim Xquang liên quan đến phân loại là khó khăn. Do đó, các chiến lược điều trị dựa trên lượng dịch chuyển (xem Bảng).
Gãy xương không di lệch được điều trị bằng bó bột cánh tay dài Những gãy xương này phải được theo dõi cẩn thận vì chúng có xu hướng di lệch Theo dõi cả hai góc nghiêng và góc xiên được thực hiện sau khi tháo bột.
Khi gãy xương di lệch đã đông cứng ở vị trí không có xương gãy, điều trị rất khó khăn và có nhiều biến chứng, vì vậy nên phẫu thuật cắt bỏ trong vòng 48 giờ đầu.
Nắn mở được chỉ định cho tất cả các loại gãy di lệch và những loại gãy không vững khớp.
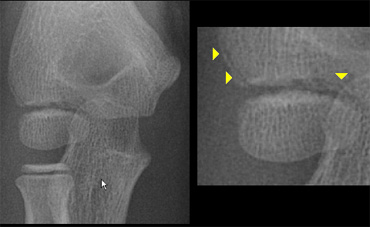
Lateral Condyle fractures (3) .
The diagnosis of a lateral condyle fracture can be challenging.
Fracture lines are sometimes barely visible (figure).
Remembering the fact that the lateral condyle fracture is the second most common elbow-fracture in children and because you know where to look for will help youGãy lồi cầu xương bên (3).
Chẩn đoán gãy lồi cầu ngoài xương cánh tay có thể là một thách thức.
Các đường gãy đôi khi hầu như không nhìn thấy được (hình).
Nhớ rằng gãy lồi cầu ngoài là loại gãy xương khuỷu phổ biến thứ hai ở trẻ em và vì bạn biết nên tìm ở đâu sẽ giúp bạn
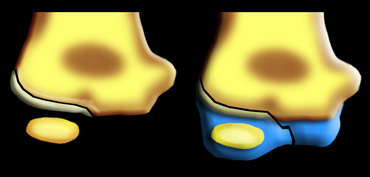 Lateral condyle fracture. On the x-ray only a small metaphyseal fragment is visible. The detatched fragment however is larger than it appears on the radiograph. The fracture extents into the lateral ridge of the trochlea. Elbow is probably unstable.Gãy lồi cầu ngoài Chỉ có thể nhìn thấy trên phim X-quang một mảnh xương nhỏ Mảnh xương lớn hơn so với trên phim X quang Gãy xương lan rộng vào sống sườn của mấu chuyển Khuỷu tay có thể không vững
Lateral Condyle fractures (4) .
Since most of the structures involved are cartilageneous, it is very difficult to know the exact extent of the fracture.
Gãy lồi cầu xương bên (4).
Vì hầu hết các cấu trúc liên quan là sụn, rất khó để biết chính xác mức độ gãy xương.
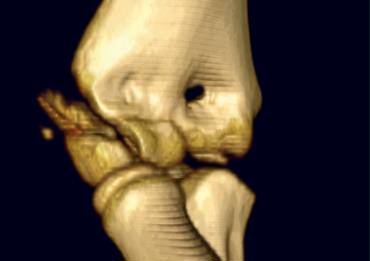 CT reconstruction of displaced lateral condyle fracture. Humeroulnar joint is stable.CT tái tạo lại ổ gãy lồi cầu ngoài xương cánh tay, khớp vai trụ vững.
Sometimes the fracture runs through the ossified part of the capitellum. In those cases it is easy.
The case on the left shows a lateral condyle fracture extending through the ossified part of the capitellum.
This is a Milch I fracture. The elbow is stable.
There is too much displacement so osteosynthesis has to be performed.Đôi khi gãy xương chạy qua phần xương hóa xương của đầu xương ức, trong những trường hợp đó thì dễ dàng.
Trường hợp bên trái cho thấy một vết nứt lồi cầu ngoài kéo dài qua phần xương của đầu.
Đây là gãy Milch I, khuỷu ổn định.
Có quá nhiều dịch chuyển nên phải thực hiện tổng hợp xương.
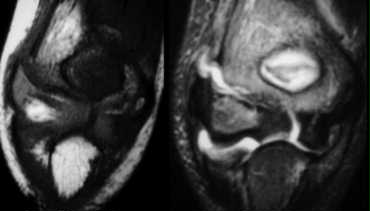 MR of lateral condyle fracture. Milch II and unstable elbow. T2 image with fat saturation on the right shows cartilaginous fracture. Fracture-fragment surrounded by synovial fluid. (Courtesy of Lynne Steinbach, M.D. Univ. of California, San Francisco)Cộng hưởng từ gãy lồi cầu ngoài, khuỷu Milch II và không vững, hình ảnh T2 có độ bão hoà mỡ bên phải cho thấy gãy sụn, mảnh gãy có bao quanh là dịch khớp (Thuyết minh của Lynne Steinbach, bác sĩ y khoa California, San Francisco)
MRI can be helpfull in depicting the full extent of the cartilaginous component of the fracture.
The case on the left shows a fracture extending into the unossified trochlear ridge.
The fracture through the trochlear cartilage is so far medial that the ulna is only supported on the medial side.
This means that the elbowjoint is unstable.MRI có thể hữu ích trong việc mô tả toàn bộ diện tích sụn của gãy xương.
Trường hợp bên trái cho thấy một vết gãy kéo dài vào sống lưng không xương.
Gãy xương qua sụn mấu chuyển nằm ở vị trí xa trong đến mức trụ xương chỉ được hỗ trợ ở phía trong.
Điều này có nghĩa là khớp khuỷu không ổn định.
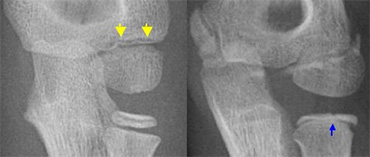 LEFT a subtle lateral condyle fracture. Less than 2 mm displacement and probably stable. RIGHT a different case. Oblique view gives nice impression of fracture. Blue arrow indicates a cleft epiphysis of the radius (normal variant)Trái: Gãy lồi cầu ngoài kín đáo, di lệch dưới 2 mm và có thể ổn định. Phải: Một ca khác. Tư thế chếch cho thấy đường gãy rõ. Mũi tên xanh chỉ khe ở đầu xương quay, một biến thể bình thường.
Lateral Condyle fractures (5)
In lateral condyle fractures the actual fracture line can be very subtle since the metaphyseal flake of bone may be minor.
The fracture fragment is often rotated.
An oblique view can be helpfull, but usually these are not routinely performed (figure).Gãy lồi cầu xương bên (5)
Trong gãy lồi cầu ngoài, đường gãy thực tế có thể rất tinh tế vì mảnh xương có thể nhỏ.
Mảnh vỡ thường được xoay.
Chế độ xem chéo có thể hữu ích, nhưng thường thì những điều này không được thực hiện thường xuyên (hình).
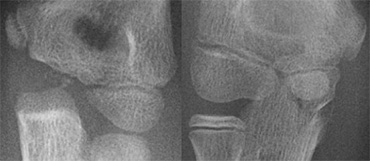 Two cases of overprojection of the capitellum on humeral epiphysis simulating a fracture. Notice olecranon fracture on the rightHai trường hợp lồi đầu trên xương cánh tay mô phỏng gãy xương, gãy mỏm khuỷu bên phải
Lateral Condyle fractures (6) .
Overprojection of the capitellum on the humeral metaphysis may simulate a lateral condyle fracture (figure).Gãy lồi cầu xương bên (6).
Sự chiếu quá mức của đầu trên xương cánh tay có thể mô phỏng một vết gãy lồi cầu ngoài (hình).
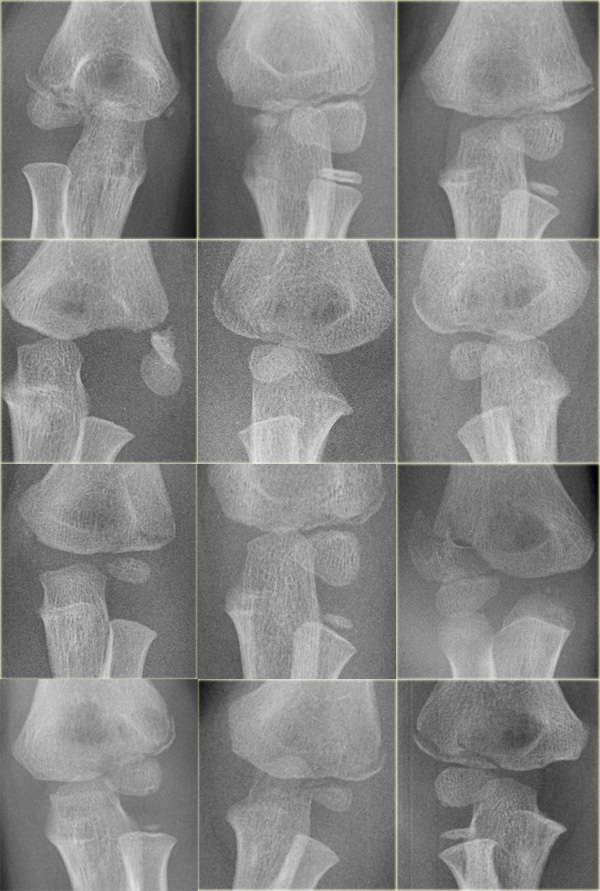
Lateral Condyle fractures (7) .
On the left a couple of examples of lateral condyle fractures.Gãy lồi cầu xương bên (7).
Bên trái là một vài ví dụ về gãy lồi cầu ngoài.
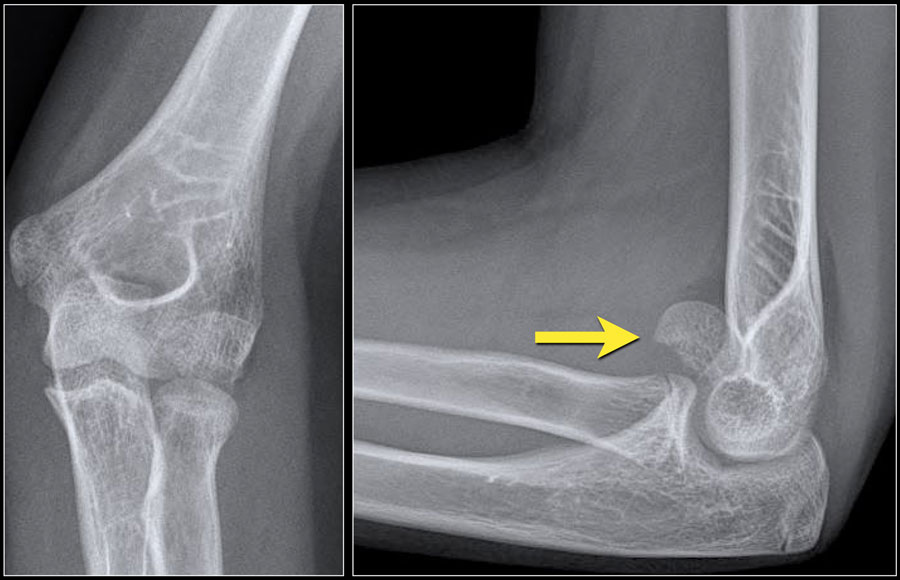
Capitellum fracture
While fractures of the lateral condyle occur in children between the age of 4 -10 years, isolated fractures of the capitellum are seen in children above the age of 12.
Gãy xương đầu đòn
Trong khi gãy lồi cầu ngoài xảy ra ở trẻ em từ 4 -10 tuổi, gãy đơn độc của đầu xương được thấy ở trẻ em trên 12 tuổi.
Capitellum fractures are uncommon.
The rotation of the fracture fragment gives a typical appearance on the X-rays (arrow).Gãy xương đầu não không phổ biến.
Sự quay của mảnh gãy cho hình ảnh điển hình trên tia X (mũi tên).
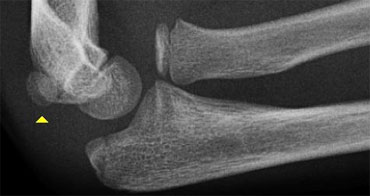 Normal medial epicondyle projecting posteriorly. Notice radial head dislocation and olecranon fractureBiểu mô lồi cầu trong bình thường lồi ra sau Nhận thấy trật khớp chỏm quay và gãy mỏm khuỷu
Medial Epicondyle avulsionVỡ lồi cầu xương cánh tay trong
The medial epicondyle is an apophysis since it does not contribute to the longitudinal growth of the humerus.
It is located on the dorsal side of the elbow.
On a lateral view especially if the arm is endorotated it can project so far posteriorly that one could suggest an avulsion (figure).
However avulsions are located more distally and anteriorly.
Since the medial epicondyle is an extra-articular structure a fracture or avulsion will not automatically produce a positive fat pad sign.Lồi lồi cầu trong là một apophysis vì nó không góp phần vào sự phát triển theo chiều dọc của xương cánh tay.
Nó nằm ở mặt lưng của khuỷu tay.
Trên mặt cắt ngoài, đặc biệt nếu cánh tay được gắn vòng, nó có thể chiếu ra phía sau đến mức người ta có thể gợi ý một sự nhổ (hình).
Tuy nhiên, các chỗ nhổ nằm xa và ở phía trước.
Vì lồi cầu trong là một cấu trúc ngoài khớp nên gãy xương hoặc nhổ sẽ không tự động tạo ra dấu hiệu mỡ dương tính.
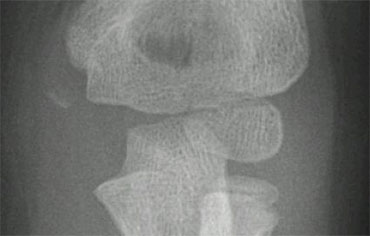 Avulsion of medial epicondyle.Nhổ lồi cầu trong.
Medial Epicondyle avulsion (2).
80% of avulsion fractures occur in boys with a peak age in early adolescence.
The mechanism is an acute valgus stress due to a fall on the outstretched hand or sometimes due to armwrestling.
Chronic injuries do occur in young athletes (little league elbow).
The mechanism that causes these stressfractures on the medial side is the same mechanism that causes a osteochondritis of the capitellum due to impaction on the lateral side.Vỡ lồi cầu xương cánh tay trong (2).
80% gãy xương bong gân xảy ra ở trẻ trai với độ tuổi cao nhất là ở tuổi vị thành niên.
Cơ chế là một căng thẳng valgus cấp tính do ngã trên bàn tay duỗi ra hoặc đôi khi do vật tay.
Chấn thương mạn tính xảy ra ở các vận động viên trẻ tuổi (khuỷu tay nhỏ).
Cơ chế gây ra các vết nứt do căng thẳng ở phía trong cũng là cơ chế gây ra viêm xương sụn của đầu do sự tác động ở phía bên.
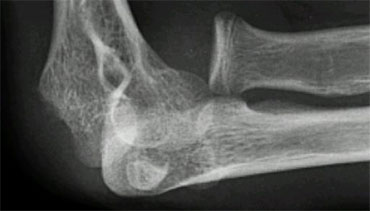 Dislocation of the elbow with interposed medial epicondyle.Trật khớp khuỷu với lồi cầu trong nằm xen kẽ.
Medial Epicondyle avulsion (3).
There is a 50% incidence of associated elbow dislocations.
When the elbow is dislocated and the medial epicondyle is avulsed,
it may become interposed between the articular surface of the humerus and the olecranon (figure).
In every dislocation the first question should be 'where is the medial epicondyle'.Vỡ lồi cầu xương cánh tay trong (3).
Tỷ lệ trật khớp khuỷu liên quan là 50%.
Khi trật khớp khuỷu và lồi cầu trong bị nhổ ra,
nó có thể bị kẹt giữa mặt khớp của xương cánh tay và mỏm khuỷu.
Trong mỗi trật khớp, câu hỏi đầu tiên nên là 'mục lồi cầu trong ở đâu'.
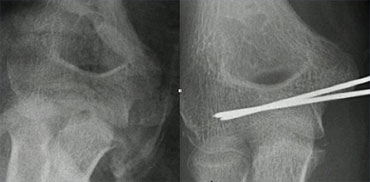 Same case as above. After reduction the epicondyle returned to its normal position (not good visible due to cast) and was fixated with K-wires.Trường hợp tương tự như trên, sau khi nắn chỉnh, lồi cầu trở về vị trí bình thường (không nhìn rõ do bó bột) và được cố định bằng dây K.
On reducing the elbow the fragment may return to it's original position or remain trapped in the joint.
This may severely damage the articular surface.
So post-reduction films should be studied carefully.Khi nắn chỉnh khuỷu tay, mảnh xương có thể trở lại vị trí ban đầu hoặc vẫn bị kẹt trong khớp.
Điều này có thể làm tổn thương nghiêm trọng bề mặt khớp.
Vì vậy, phim sau nắn chỉnh nên được nghiên cứu cẩn thận.
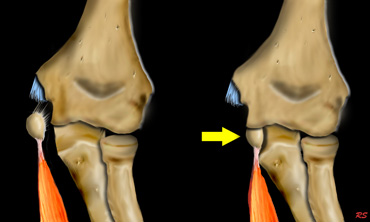
Medial Epicondyle avulsion (4).
Due to the extreme valgus force the joint may temporarily open.
The avulsed fragment may become entrapped in the joint even when there is no dislocation of the elbow.Vỡ lồi cầu xương cánh tay trong (4).
Do lực valgus quá mạnh, khớp có thể tạm thời mở ra.
Mảnh xương bị bật ra có thể bị kẹt trong khớp ngay cả khi không có trật khớp khuỷu.
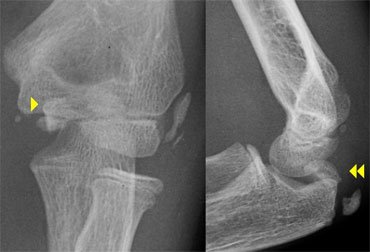 On AP-view the avulsed medial epicondyle projects over the trochlea. Lateral view shows the fragment to be trapped within the joint.Trên chế độ xem AP, lồi cầu trong được nhổ ra phía trên mấu chuyển. Chế độ xem bên cho thấy mảnh bị mắc kẹt trong khớp.
Medial Epicondyle avulsion (5).
An avulsed fragment that is located within the joint can give diagnostic problems.
On an AP-view this fragment may be overlooked (figure).
When the trochlea is not yet ossified the avulsed fragment may simulate a trochlear ossification centre.Vỡ lồi cầu xương cánh tay trong (5).
Một mảnh xương bị bật ra nằm trong khớp có thể gây ra các vấn đề chẩn đoán.
Trên chế độ xem AP, đoạn này có thể bị bỏ qua (hình).
Khi mấu chuyển chưa được cốt hóa, mảnh xương được lấy ra có thể mô phỏng một trung tâm cốt hóa mấu Chuyển.
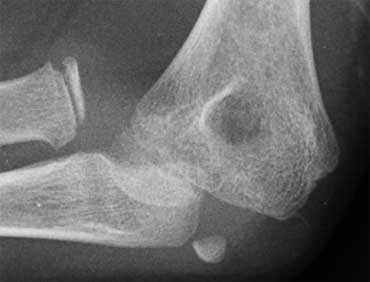 Another example of a dislocated elbow with avulsion of the medial epicondyle. In this case the epicondyle is not retracted into the joint.Một ví dụ khác về trật khớp khuỷu với sự nhổ lồi cầu trong Trong trường hợp này, lồi cầu không được rút vào khớp.
Medial Epicondyle avulsion (6). Vỡ lồi cầu xương cánh tay trong (6).
Treatment
Non-displaced fractures are treated with 1-2 weeks cast or splint.
There is disagreement about the amount of displacement of the medial epicondyle that requires operative fixation.
There is support for both operative aswell as non-operative management of medial epicondyle fractures with 5-15mm displacement.Điều trị
Gãy xương không di lệch được điều trị bằng bó bột hoặc nẹp trong 1-2 tuần.
Có sự bất đồng về số lượng di lệch của lồi cầu trong cần phải cố định bằng phẫu thuật.
Có sự hỗ trợ cho cả phẫu thuật cũng như điều trị bảo tồn gãy lồi cầu trong xương cùng với độ lệch 5-15 mm.
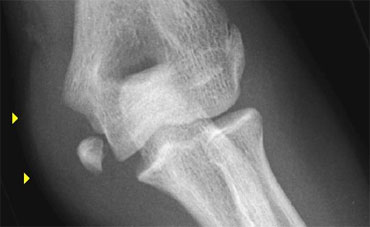 Avulsion of the medial epicondyle. The amount of soft tissue swelling on the medial side suggests that the elbow was dislocated.Trật lồi cầu trong.Số lượng mô mềm sưng ở mặt trong gợi ý trật khớp khuỷu.
Medial Epicondyle avulsion (7).
If the history or the radiographs suggest that the elbow was or is dislocated, greater soft tissue injurie is likely to be present requiring need for early motion.Vỡ lồi cầu xương cánh tay trong (7).
Nếu tiền sử hoặc phim X quang cho thấy khuỷu tay bị trật hoặc bị trật, có thể có tổn thương mô mềm lớn hơn cần phải được chuyển động sớm.
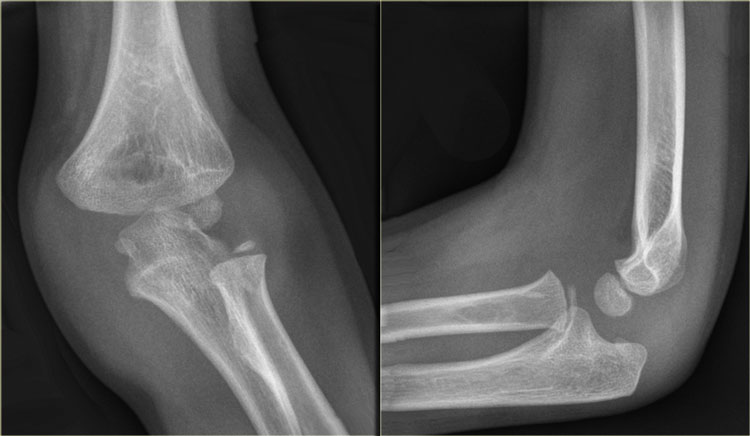 Click on the image to enlargeNhấp vào hình ảnh để phóng to
Medial Epicondyle avulsion (8).
Study the images.
You can click on the image to enlarge.
There are three findings, that you should comment on.Vỡ lồi cầu xương cánh tay trong (8).
Nghiên cứu hình ảnh.
Bạn có thể nhấp vào hình ảnh để phóng to.
Có ba phát hiện, mà bạn nên bình luận.
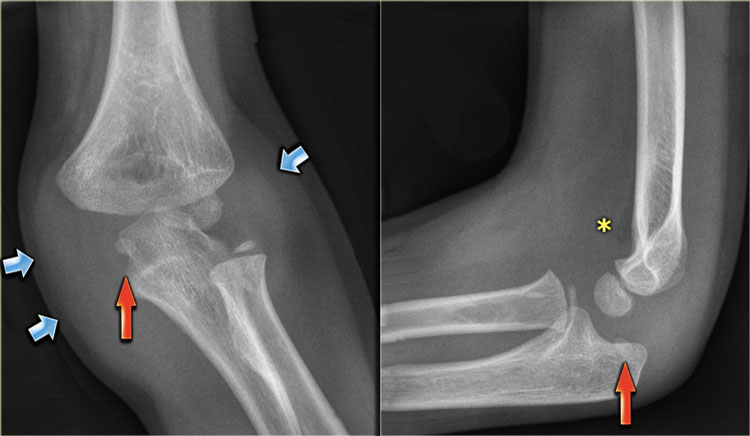 Click on the image to enlargeNhấp vào hình ảnh để phóng to
- There is enormous soft tissue swelling, which indicates that the elbow has been dislocated (blue arrows). So the next question is where is the medial epicondyle? Có sự sưng phù nề mô mềm rất lớn, cho thấy khuỷu tay đã bị trật khớp (các mũi tên màu xanh). Vì vậy, câu hỏi tiếp theo là đâu là lồi cầu trong?
- The medial epicondyle is seen entrapped within the joint (red arrows). Mụn lồi cầu trong được nhìn thấy bị mắc kẹt trong khớp (các mũi tên màu đỏ).
- Notice that there is only minor joint effusion (asterix). The medial epicondyle is an extra-articular structure and avulsion will not produce joint effusion. The small amount of joint effusion is probably the result of the prior dislocation. Lưu ý rằng chỉ có tràn dịch khớp nhẹ (asterix) Mụn lồi cầu trong là một cấu trúc ngoài khớp và nhổ sẽ không tạo ra tràn dịch khớp. Một lượng nhỏ tràn dịch khớp có thể là kết quả của trật khớp trước đó.
Continue with the MRI.Tiếp tục với MRI.
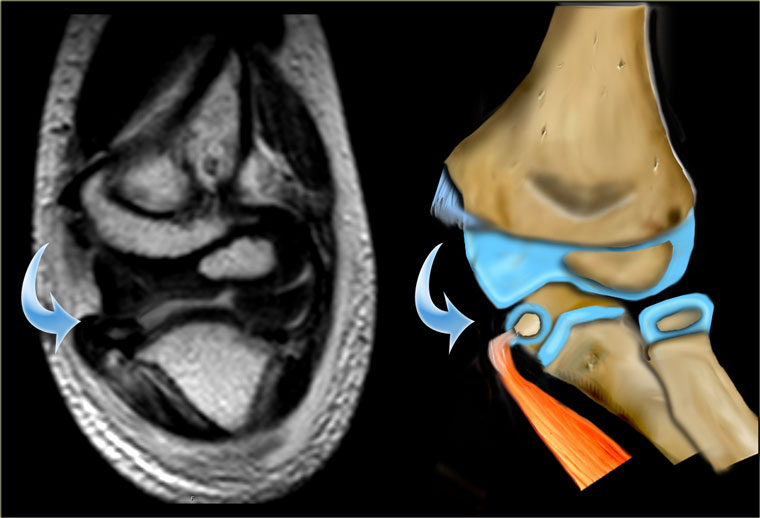 Click on the image to enlargeNhấp vào hình ảnh để phóng to
The MR shows the small medial epicondyle with tendon attachement trapped within the joint.
Chụp cộng hưởng từ cho thấy lồi cầu nhỏ trong với sự gắn kết gân bị mắc kẹt trong khớp.
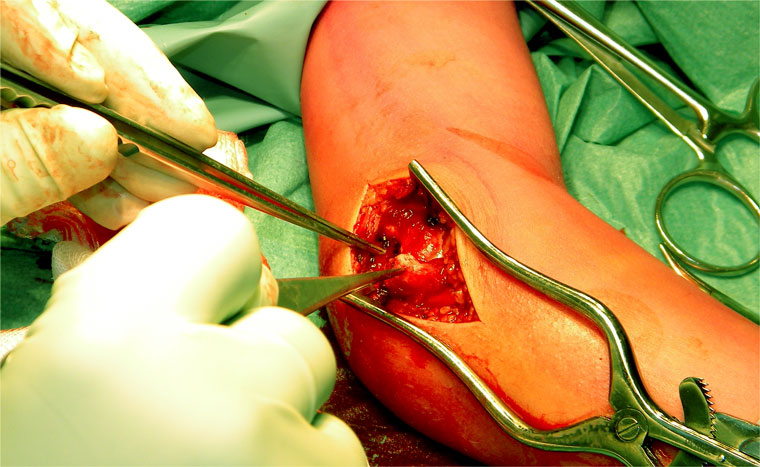
The avulsed medial epicondyl was found within the joint and repositioned and fixated with K-wires.Lồi lồi cầu trong được tìm thấy trong khớp và được định vị lại và cố định bằng dây K.
 Subtle radial neck fracture seen only on AP-view.Gãy cổ xuyên tâm nhẹ chỉ thấy trên phim AP-view.
Proximal fractures of the RadiusGãy xương quay
In adults fractures usually involve the articular surface of the radial head.
In children however it's the radial neck that fractures because the metaphyseal bone is weak due to constant remodelling.
Usually it is a Salter Harris II fracture.
If there is no displacement it can be difficult to make the diagnosis (figure).Ở người lớn, gãy xương thường liên quan đến bề mặt khớp của đầu xương quay.
Tuy nhiên ở trẻ em, cổ quay bị gãy do xương bàn ngón bị yếu do tái tạo liên tục.
Thông thường đó là gãy Salter Harris II.
Nếu không có di lệch thì có thể khó chẩn đoán (hình).
 Radial neck fracture with tilt. Notice trochlear ossifications projecting in between humerus and ulna simulating intra-articular fragments.Gãy cổ quay nghiêng Lưu ý các mảnh xương mấu chuyển mọc giữa xương cánh tay và xương trụ mô phỏng các mảnh xương trong khớp.
If there is less than 30? tilt of the radial head patients are treated with a collar.
It is important to realize that there is normally some angulation of the radial head ( up to 15?).
If there is more than 30? tilt closed reduction is performed.Nếu có độ nghiêng dưới 30? của đầu quay thì bệnh nhân được điều trị bằng vòng cổ.
Điều quan trọng là phải nhận ra rằng bình thường có một số góc của đầu quay (lên đến 15?).
Nếu có hơn 30 thì được thực hiện nắn chỉnh độ nghiêng.
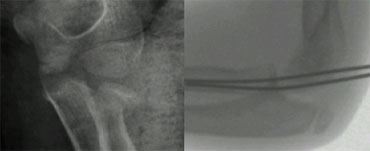 After closed reduction radiograph in cast shows unsuccesfull reduction. K-wire insertion is performedSau khi nắn kín, chụp X quang trong bó bột cho thấy nắn không thành công, thực hiện chèn dây K
Whenever closed reduction is unsuccesfull in restoring tilt or when it is not possible to pronate and supinate up to 60?, a K-wire is inserted to maintain reduction.Bất cứ khi nào nắn kín không thành công trong việc phục hồi độ nghiêng hoặc khi không thể sấp và ngửa lên đến 60?, một dây K được đưa vào để duy trì việc nắn chỉnh.
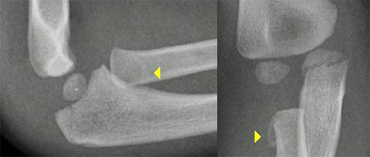 The radial epiphysis is slipped (arrows). The radiocapitellar line does not pass through the capitellum indicating dislocation and there is a fracture of the olecranonĐường mỏm xương quay bị trượt (các mũi tên) Đường mỏMũi chũm không đi qua đầu chỏm cho thấy trật khớp và có gãy xương mỏm khuỷu
Radial neck fractures aswell as radial head dislocations are in 50% of the cases associated with other elbow injuries.
The most common is a fracture of the olecranon.
When the radial epiphysis is yet very small a slipped radial epiphysis may be overlooked (figure).Gãy cổ quay cũng như trật khớp đầu quay xảy ra trong 50% các trường hợp liên quan đến các chấn thương khuỷu khác.
Phổ biến nhất là gãy xương mỏm khuỷu.
Khi biểu mô xương quay còn rất nhỏ, biểu mô xương tròn trượt có thể bị bỏ qua (hình).
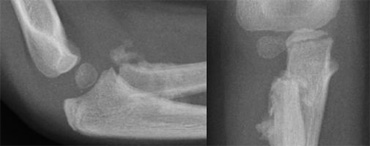 Same patient as above 4 weeks laterCùng một bệnh nhân trên 4 tuần sau đó
If these fractures are not recognized or reduction is unsuccesfull radial head overgrowth can be the result.
A short radius may also be the result since the epiphysis of the radius contributes to the length growth of the radius.Nếu những gãy xương này không được nhận ra hoặc nắn chỉnh không thành công thì có thể dẫn đến tình trạng quá phát của chỏm xương quay.
Bán kính ngắn cũng có thể là kết quả vì sự phát triển của bán kính góp phần vào sự tăng trưởng chiều dài của bán kính.
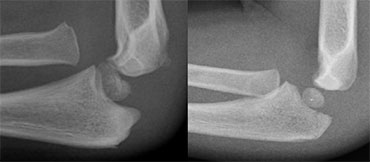 LEFT: an obvious radial dislocation. No fracture of the ulna (Monteggia) was foundRIGHT: a subtle radial head dislocation. Associated olecranonfracture is seen on carefull inspectionTRÁI: trật khớp quay rõ ràng, không tìm thấy xương trụ (Monteggia) QUYỀN: trật khớp đầu quay nhẹ, có thể thấy xương sọ bên trong khớp khi khám kỹ.
Dislocations of the Radial headTrật khớp đầu quay
Dislocations of the radial head can be very obvious.
It is however not uncommon that these dislocations are subtle and easily overlooked.
In all cases one should look for associated injury.
In the original discription of Monteggia there is a radial dislocation in combination with a proximal ulnar shaft fracture.
However fractures anywhere along the ulna have been reported.
Especially associated fractures of the olecranon are very common (figure).Trật khớp đầu quay có thể rất rõ ràng.
Tuy nhiên, không có gì lạ khi những trật khớp này rất khó phát hiện và dễ bị bỏ qua.
Trong mọi trường hợp, cần tìm kiếm tổn thương liên quan.
Trong mô tả ban đầu của Monteggia có trật khớp quay kết hợp với gãy đầu trên xương trụ.
Tuy nhiên gãy xương bất cứ nơi nào dọc theo xương trụ đã được báo cáo.
Đặc biệt gãy liên quan đến mỏm khuỷu rất phổ biến.
Radius Pulled Elbow (Nursemaid's elbow)
In children When the forearm is pulled the radial head moves distally and the ligament slips over the radial head and becomes trapped within the joint. The X-ray is normal.
The condition is cured by supination of the forearm. Sometimes this happens during positioning for a true lateral view (which is with the forearm in supination).Bán kính khuỷu tay bị kéo (khuỷu tay của người hầu gái)
Ở trẻ em Khi cẳng tay bị kéo, đầu quay di chuyển ra xa và dây chằng trượt qua đầu quay và bị mắc kẹt trong khớp X-quang là bình thường.
Tình trạng này được chữa khỏi bằng cách ngửa cẳng tay Đôi khi điều này xảy ra trong quá trình định vị để có góc nhìn bên thực sự (với cẳng chân ngửa).
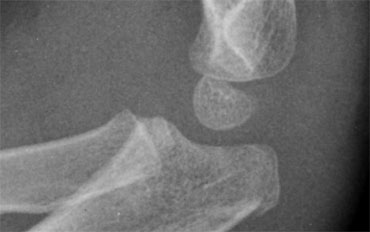 Olecranon fracture indicated by discontinuity of the dorsal cortex. No associated fracture.Gãy sụn đầu trên có biểu hiện mất liên tục vỏ não lưng, không có gãy xương đi kèm.
Olecranon fracturesGãy sụn đầu trên
Olecranon fractures in children are less common than in adults. As discussed above they are associated with radial neck fractures and radial dislocations.Gãy xương mỏm khuỷu ở trẻ em ít gặp hơn ở người lớn, như đã bàn luận ở trên, chúng có liên quan đến gãy cổ xương quay và trật khớp xương quay.
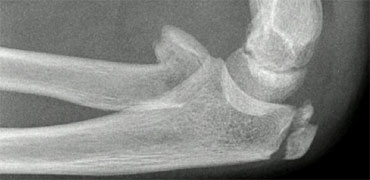 Normal olecranon ossification centres in a patient with a tilted radial neck fracture.Trung tâm cốt hóa mỏm khuỷu bình thường ở bệnh nhân gãy cổ quay nghiêng.
Olecranon fractures (2)
Do not mistake the apophysis or its separate ossification centres for a fracture.
The apophysis has undulating faintly sclerotic margins.
The growth plate usually has a different oblique course compared to a fracture-line.Gãy mỏm khuỷu (2)
Cần tránh nhầm mỏm tiếp hợp hoặc các trung tâm cốt hóa riêng biệt ở đây với đường gãy. Bờ mỏm tiếp hợp lượn sóng và hơi xơ cứng. Sụn tăng trưởng thường chạy chếch theo hướng khác với đường gãy.
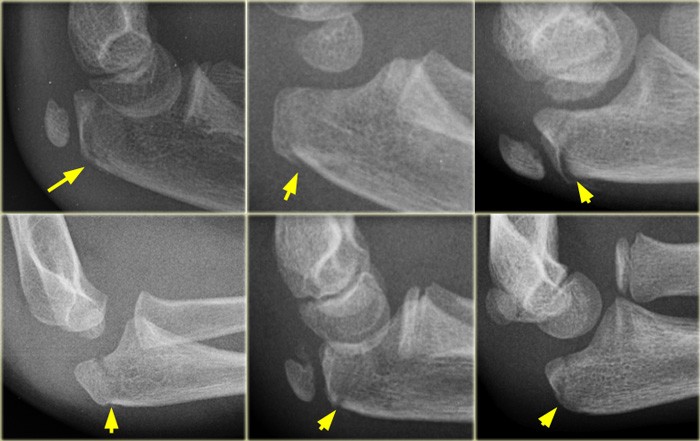
Olecranon fractures (3)
On the left some examples of fractures of the olecranon.
Notice how subtle some of these fractures are.Gãy sụn đầu gối (3)
Bên trái là một số ví dụ về gãy xương mỏm khuỷu.
Chú ý đến sự tinh tế của một số loại gãy xương này.
ConclusionKết luận
Whenever you study a radiograph of the elbow of a child, always look for: Bất cứ khi nào bạn nghiên cứu một phim X-quang khuỷu tay của một đứa trẻ, luôn luôn tìm:
- Supracondylar fracture with minimal displacementGãy trên lồi cầu xương cánh tay di lệch tối thiểu
- Lateral condyle fractureGãy lồi cầu xương bên
- Slipped radial epiphysis Trượt mỏm xương quay
- Radial dislocationTrật khớp quay
- Position of the medial epicondyle. Vị trí lồi cầu trong.
ReferencesTài liệu tham khảo
-
Elbow and forearm injuries in children by T. David Cox, MD, and Andrew Sonin, MD,
in Radiology of Skeletal traumaThird edition Editor Lee F. Rogers MD
Tổn thương khuỷu tay và cẳng tay ở trẻ em của T. David Cox, MD, và Andrew Sonin, MD, -
Elbow injuries in children in www.orthotheers
Tổn thương khuỷu tay ở trẻ em tại www.orthotheers
A site developed for Postgraduate Orthopaedic Trainees preparing for the FRCS Examination in the United Kingdom. Một trang web được phát triển cho các thực tập sinh sau đại học chỉnh hình chuẩn bị cho kỳ thi FRCS tại Vương quốc Anh.
-
Pediatric Elbow fractures in Wheeless on line textbook on Orthopaedics
Gãy xương khuỷu ở trẻ em trong sách giáo khoa chỉnh hình Wheeless on line
A site with detailed information on fractures and therapy. Một trang web có thông tin chi tiết về gãy xương và điều trị.