
Epilepsy - Role of MRIĐộng kinh - Vai trò của MRI
Ngày đăng / cập nhật: 2012-09-01
Bản gốc trên radiologyassistant.nl ↗ · tải về lúc 2026-11-19 20:19 · bản dịch máy có chuẩn hóa thuật ngữ chẩn đoán hình ảnh
In many patients with epilepsy antiepileptic drug treatment is unable to control the seizures.
Using a dedicated MRI-protocol, it is possible to detect an epileptogenic lesion in 80 percent of these patients.
Resection of these lesions can lead to seizure freedom in many patients.
We will discuss the MRI protocol and the typical findings in the most common epilepsy-associated diseases.Ở nhiều bệnh nhân động kinh, điều trị bằng thuốc chống động kinh không thể kiểm soát được cơn co giật.
Sử dụng một quy trình MRI chuyên dụng, có thể phát hiện tổn thương động kinh ở 80% số bệnh nhân này.
Cắt bỏ các tổn thương này có thể dẫn đến tự do động kinh ở nhiều bệnh nhân.
Chúng tôi sẽ thảo luận về quy trình chụp MRI và các dấu hiệu điển hình trong các bệnh liên quan đến động kinh phổ biến nhất.
IntroductionMở đầu
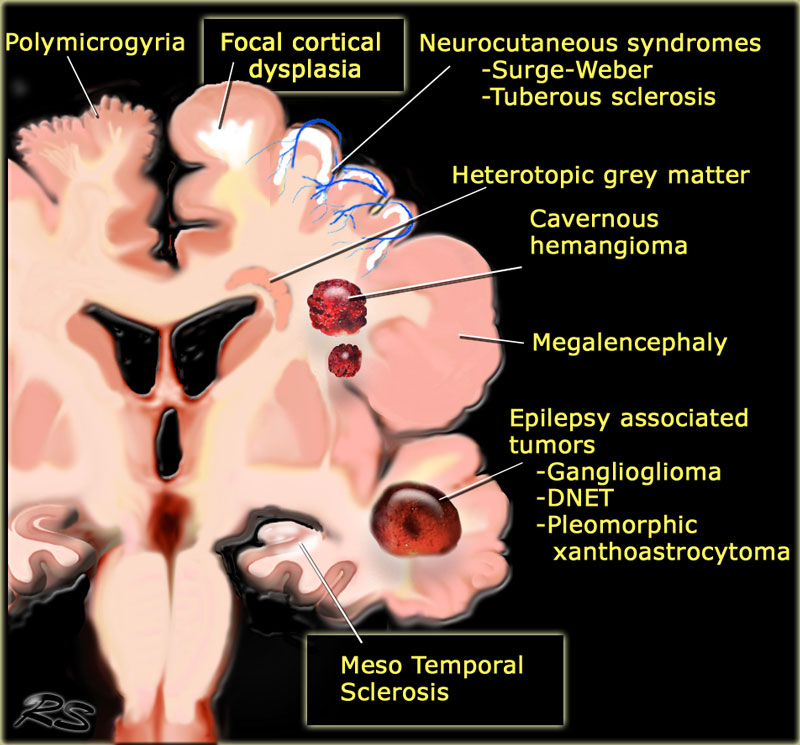

Common causes of EpilepsyNguyên nhân thường gặp của động kinh
The illustration summarizes the most common causes of seizures in patients with medically uncontrollable epilepsy.
Some of these lesions are readily identifiable.
Meso temporal sclerosis and focal cortical dysplasia are the most common causes and can only be depicted with a dedicated protocol.Hình minh hoạ tóm tắt các nguyên nhân phổ biến nhất của cơn động kinh ở bệnh nhân động kinh không kiểm soát được về mặt y tế.
Một số tổn thương này có thể dễ dàng nhận dạng.
Xơ cứng Meso thái dương và loạn sản vỏ não khu trú là những nguyên nhân phổ biến nhất và chỉ có thể được mô tả bằng một phác đồ chuyên dụng.
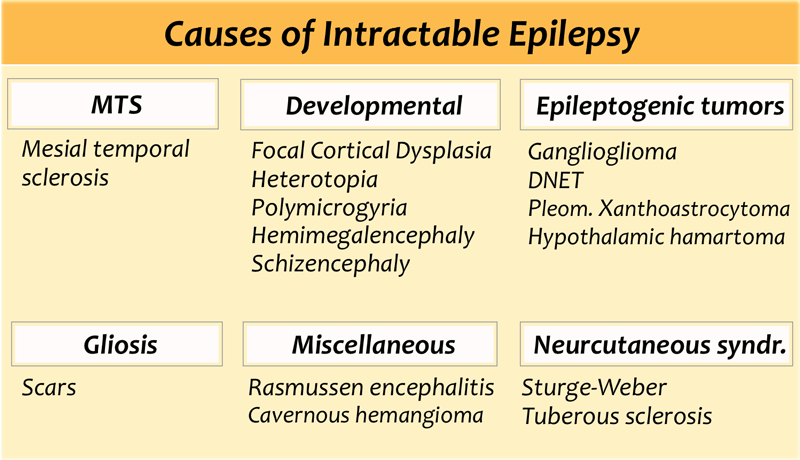
The table also summarizes epileptogenic lesions that are detected in patients with uncontrollable seizures.
Mesial temporal sclerosis is the most common cause of intractable epilepsy.
In medication refractory epilepsia the most common location of the epilectogenic lesion is temporal lobe (60%), frontal lobe (20%) and parietal lobe (10%), periventricular (5%) and occipital (5%).
Bảng này cũng tóm tắt các tổn thương động kinh được phát hiện ở những bệnh nhân co giật không kiểm soát được.
Xơ cứng thái dương là nguyên nhân phổ biến nhất của bệnh động kinh khó chữa.
Trong động kinh kháng thuốc, vị trí thường gặp nhất của tổn thương do cắt bỏ lông là thuỳ thái dương (60%), thuỳ trán (20%) và thuỳ đỉnh (10%), quanh não thất (5%) và chẩm (5%).
Seizures and EpilepsyĐộng kinh và động kinh
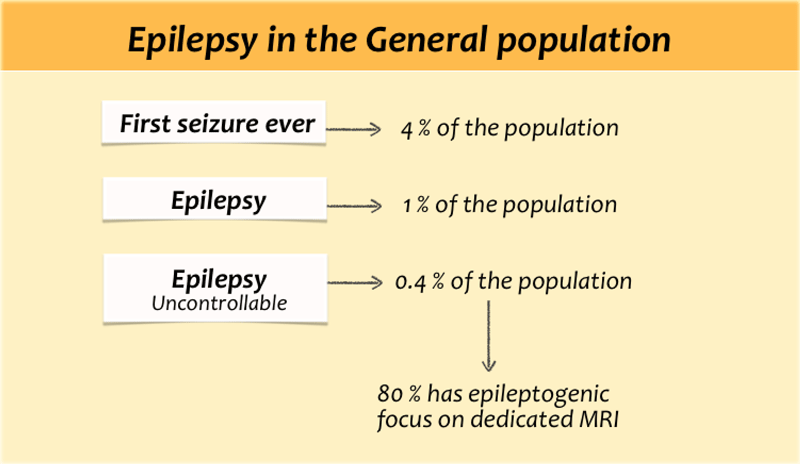
Seizures are common. About 4 percent of all people will have at least one seizure during their lifetime.
In patients with a first ever seizure imaging will mostly show no brain-abnormalities, because the seizure is provoked by fever, drugs, dehydration or sleep deprivation.
The term epilepsy is used, when there are recurrent unprovoked seizures.
About 60 percent of patients with epilepsy can be controlled with antiepileptic drugs.
Most patients with uncontrollable seizures have complex partial seizures.Động kinh là phổ biến Khoảng 4% số người sẽ có ít nhất một cơn động kinh trong suốt cuộc đời của họ.
Ở những bệnh nhân có hình ảnh động kinh đầu tiên sẽ hầu như không có bất thường về não, bởi vì cơn co giật được kích thích bởi sốt, thuốc, mất nước hoặc thiếu ngủ.
Thuật ngữ động kinh được sử dụng, khi có những cơn động kinh không được kích thích tái phát.
Khoảng 60% bệnh nhân động kinh có thể được kiểm soát bằng thuốc chống động kinh.
Hầu hết các bệnh nhân co giật không kiểm soát được đều có cơn co giật cục bộ phức tạp.
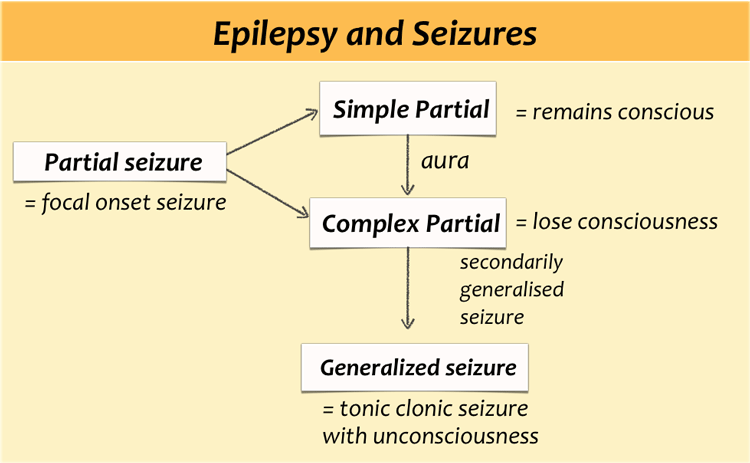
Partial seizures - also called focal seizures - are seizures which affect only a part of the brain at onset. They usually start in the temporal lobe.
In simple partial seizures the person remains conscious.
A simple partial seizure can be a precursor to a larger seizure and then it is called an aura.
A complex partial seizure affects a larger part of the hemisphere and the person may lose consciousness.
If a partial seizure spreads from one hemisphere to the other this will give rise to a secondarily generalised seizure.
The person will become unconscious and may have a tonic clonic seizure.
Động kinh cục bộ - còn được gọi là động kinh cục bộ là những cơn động kinh chỉ ảnh hưởng đến một phần của não khi khởi phát. Chúng thường bắt đầu ở thuỳ thái dương.
Trong các cơn động kinh cục bộ đơn giản, người bệnh vẫn tỉnh táo.
Một cơn động kinh cục bộ đơn giản có thể là tiền thân của cơn động kinh lớn hơn và sau đó nó được gọi là aura.
Một cơn động kinh cục bộ phức tạp ảnh hưởng đến một phần lớn hơn của bán cầu và người bệnh có thể mất ý thức.
Nếu một cơn động kinh cục bộ lan từ bán cầu này sang bán cầu kia, điều này sẽ dẫn đến một cơn động Kinh toàn thể thứ phát.
Người bệnh sẽ bất tỉnh và có thể bị co giật co cứng.
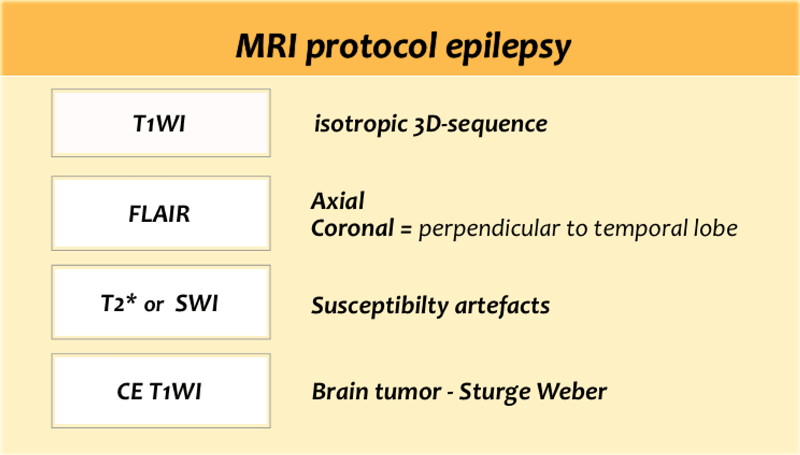
MRI epilepsy protocolQuy trình chụp MRI động kinh
The table shows a dedicated epilepsy protocol.
Some will also use Inversion Recovery and not use contrast on a routine base.Bảng này cho thấy một phác đồ động kinh chuyên dụng.
Một số cũng sẽ sử dụng Inversion Recovery và không sử dụng thuốc cản quang trên cơ sở thông thường.
T1WI
Superior for cortical thickness and the interface between grey and white matter.
On T1WI look for grey matter occuring in an aberrant location as in gray matter heterotopia.
FLAIR
Look very carefully for cortical and subcortical hyperintensities on the FLAIR, which can be very subtle.
Since FLAIR may show false-positive results due to artefacts, the abnormalities should be confirmed on T2WI.
T2* or SWI
Helpful when searching for haemoglobin breakdown products as in posttraumatic changes and cavernomas, or to look for calcifications in tuberous sclerosis, Sturge-Weber, cavernomas and gangliogliomas.T1WI
Cao hơn về độ dày vỏ não và giao diện giữa màu xám và chất trắng.
Trên T1WI tìm kiếm chất xám xảy ra ở một vị trí bất thường như trong dị thể chất xám.
FLAIR
Hãy xem xét rất cẩn thận các cường độ vỏ não và dưới vỏ trên FLAIR, có thể rất tinh tế.
Vì FLAIR có thể cho kết quả dương tính giả do các dị vật, các bất thường nên được xác nhận trên T2WI.
T2 * hoặc SWI
Có ích khi tìm kiếm các sản phẩm phân huỷ hemoglobin như trong các thay đổi sau chấn thương và u thể hang, hoặc tìm kiếm vôi hóa trong xơ cứng củ, Sturge-Weber, u thể hang và u thần kinh đệm.
Mesial temporal sclerosisBệnh xơ cứng thái dương
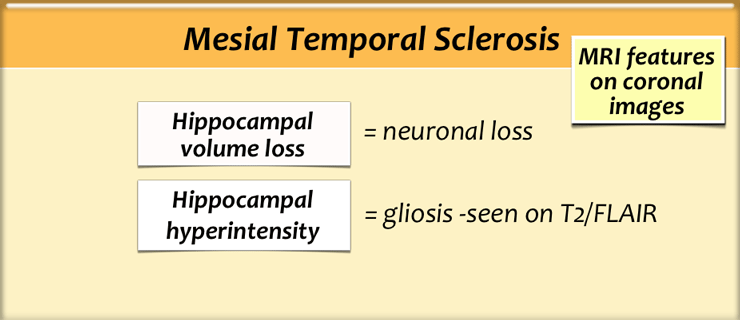
Mesial temporal sclerosis (MTS) is a specific pattern of hippocampal neuronal loss accompanied by gliosis and atrophy.
The etiology is unknown, but there is a relationship between MTS and prolonged febrile seizures earlier in life, complicated delivery and developmental processes.
In 15% of patients another developmetal abnormality can be found, mostly focal cortical dysplasia.
This is called dual pathology.
MTS is the most common cause of partial complex epilepsy in adults and is also the most common etiology in young adult patients undergoing surgery.
Surgical removal of visible MRI changes associated with unilateral mesial temporal sclerosis leads to seizure freedom in up to 80% of cases.Xơ cứng thái dương trung bình (Mesial temporal sclerosis - MTS) là một dạng đặc trưng của mất nơ-ron hồi hải mã kèm theo tổn thương thần kinh đệm và teo thần kinh đệM.
Nguyên nhân chưa rõ, nhưng có mối liên quan giữa MTS và cơn co giật do sốt kéo dài sớm hơn trong cuộc đời, sinh con phức tạp và quá trình phát triển.
Trong 15% bệnh nhân, có thể tìm thấy bất thường phát triển kim loại khác, chủ yếu là loạn sản vỏ não khu trú.
Đây được gọi là bệnh lý kép.
MTS là nguyên nhân phổ biến nhất của động kinh phức tạp một phần ở người lớn và cũng là nguyên nhân thường gặp nhất ở bệnh nhân người lớn trẻ tuổi đang phẫu thuật.
Phẫu thuật cắt bỏ những thay đổi MRI có thể nhìn thấy liên quan đến xơ cứng thái dương gần một bên dẫn đến tự do co giật ở 80% trường hợp.
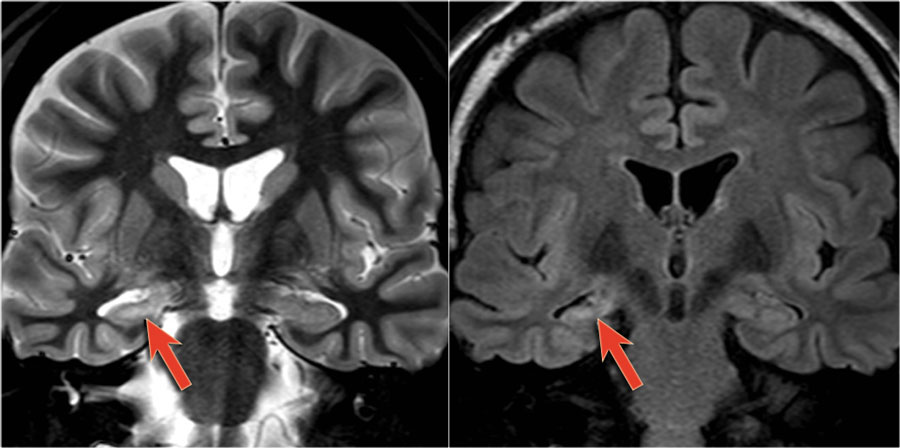 Right-sided mesial temporal sclerosisXơ cứng thái dương gần bên phải
Coronal T2W and FLAIR images are the most sensitive for detecting MTS.
On axial slices mesial temporal sclerosis is commonly overlooked.
Bilateral mesial temporal sclerosis is difficult to detect due to the lack of comparison with the unaffected contralateral hippocampus.
Hình ảnh T2W và FLAIR là nhạy nhất để phát hiện MTS.
Trên các lát cắt dọc trục, xơ hóa thái dương gần thường bị bỏ qua.
Xơ cứng thái dương gần hai bên khó phát hiện do không so sánh được với hồi hải mã đối bên không bị tổn thương.
The coronal T2WI and FLAIR images show right-sided mesial temporal sclerosis.
Notice the volume loss, which indicates atrophy and causes secondary enlargement of the temporal horn of the lateral ventricle.
The high signal in the hippocamous reflects gliosis.
Hình ảnh T2WI và FLAIR của vành đai cho thấy xơ cứng thái dương gần bên phải.
Lưu ý sự mất thể tích, cho thấy teo và gây ra sự phì đại thứ phát của sừng thái dương của tâm thất bên.
Tín hiệu cao trong khớp háng phản ánh sự hẹp thần kinh đệm.
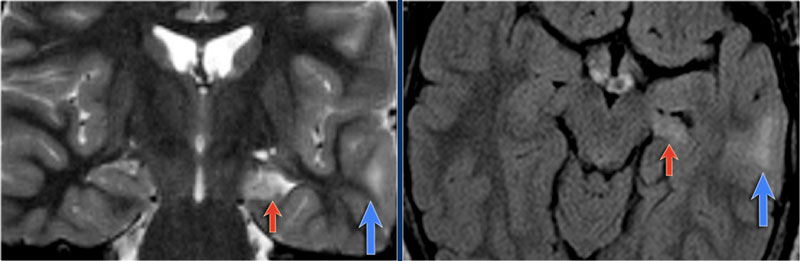 Dual pathology: MTS and focal cortical dysplasiaGiải phẫu bệnh kép: MTS và loạn sản vỏ não khu trú
Mesial temporal sclerosis may occur in association with other pathology, especially focal cortical dysplasia.
This is called dual pathology.
Xơ cứng thái dương có thể xảy ra liên quan đến các bệnh lý khác, đặc biệt là loạn sản vỏ não khu trú.
Đây được gọi là bệnh lý kép.
The images show mesial temporal sclerosis with a hyperintense and shrunken hippocampus (red arrows), and secondary enlargement of the left temporal horn of the left laterale ventricle.
Also notice associated subcortical hyperintensity in the left temporal lobe indicating focal cortical dysplasia.
Hình ảnh cho thấy xơ cứng thái dương gần với tăng tín hiệu và thuỳ hải mã co lại (các mũi tên màu đỏ) và phì đại thứ phát sừng thái dương trái của tâm thất bên trái.
Cũng nhận thấy tăng cường dưới vỏ liên quan ở thuỳ thái dương trái cho thấy loạn sản vỏ não khu trú.
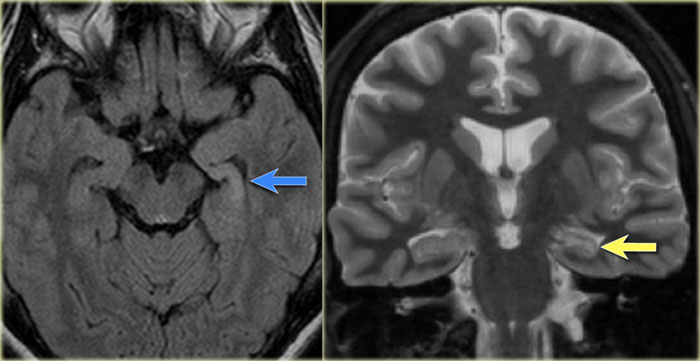 Left mesial temporal sclerosis. Subtle gliosis of left hippocampus (blue arrow) and atrophy (yellow arrow).Xơ cứng thái dương gần trái. Hẹp thần kinh đệm vùng hải mã trái (mũi tên xanh) và teo (mũa tên vàng).
35-year-old patient with refractory temporal lobe epilepsy.
MR shows subtle hyperintensity of the left hippocampus on the axial FLAIR (blue arrow) and atrophy of the left hippocampus on coronal images (yellow arrow). Bệnh nhân 35 tuổi, động kinh thuỳ thái dương kháng trị.
MR cho thấy cường độ tăng nhẹ của hồi hải mã trái trên FLAIR trục (mũi tên màu xanh) và teo hồi hải mã bên trái trên hình ảnh mạch vành (mũa tên màu vàng).
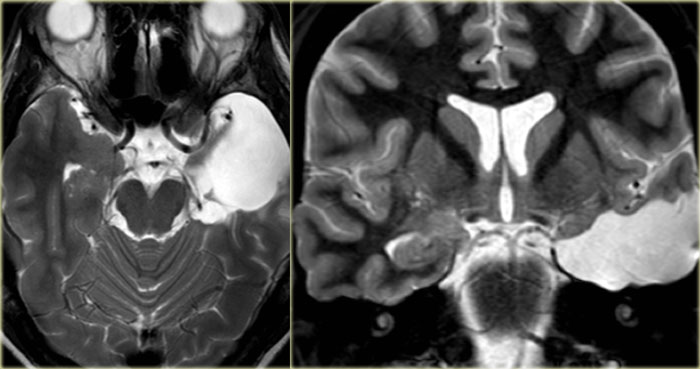 Left mesial temporal sclerosis treated with amygdalo-hippocampectomyXơ hóa thái dương gần bên trái được điều trị bằng phẫu thuật cắt bỏ vùng hạch hạnh nhân
The patient was succesfully treated with amygdalo-hippocampectomy on the left.Bệnh nhân được điều trị thành công bằng phẫu thuật cắt bỏ hạch hạnh nhân bên trái.
Differential of hippocampal hyperintensityChẩn đoán tăng tín hiệu hồi hải mã
Hippocampal hyperintensity on T2WI or FLAIR images with volume loss is diagnostic for mesial temporal sclerosis in the appropriate clinical setting. Tăng cường độ thần kinh hải mã trên hình ảnh T2WI hoặc FLAIR với mất thể tích là chẩn đoán cho xơ cứng thái dương gần trong bối cảnh lâm sàng thích hợp.
Hippocampal hyperintensity without volume loss is seen in: Tăng cường độ vùng hông lưng mà không mất thể tích được thấy trong:
- Status epilepticusTrạng thái động kinh
- Low grade tumors (astrocytoma, DNET) U độ mô học thấp (u sao bào, DNET)
- EncephalitisViêm não
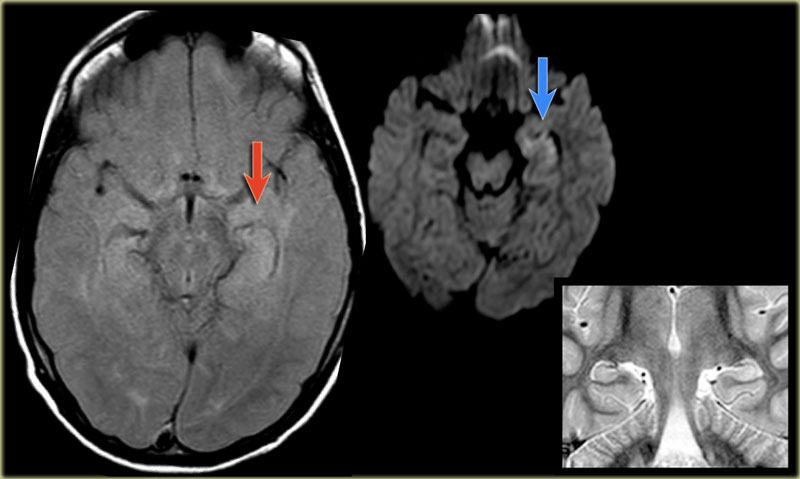 Status epilepticus. Axial FLAIR, axial DWI and coronal T2WI.Tình trạng động kinh. FLAIR trục, DWI trục và T2WI vành.
Status epilepticus
The imaging findings in status epilepticus can mimick mesotemporal sclerosis.
In status epilepticus a hyperintense hippocampus can be seen, but there is swelling and no atrophy.
Axial FLAIR, axial DWI and coronal T2WI demonstrate a hyperintense hippocampus with a slightly compressed temporal horn of the lateral ventricle consistent with hippocampal edema.
DWI shows diffusion restriction due to cytotoxic edema in the acute stage of the status epilepticus.Trạng thái động kinh
Các dấu hiệu hình ảnh trong trạng thái động kinh có thể giống với xơ cứng trung thái dương.
Trong trạng thái động kinh, có thể thấy một hồi hải mã tăng tín hiệu, nhưng có sưng và không có teo.
FLAIR trục, DWI trục và T2WI vành cho thấy một hồi hải mã tăng tín hiệu với sừng thái dương hơi chèn ép của tâm thất bên phù hợp với phù hồi hải mã.
DWI cho thấy hạn chế khuếch tán do phù độc tế bào ở giai đoạn cấp của trạng thái động kinh.
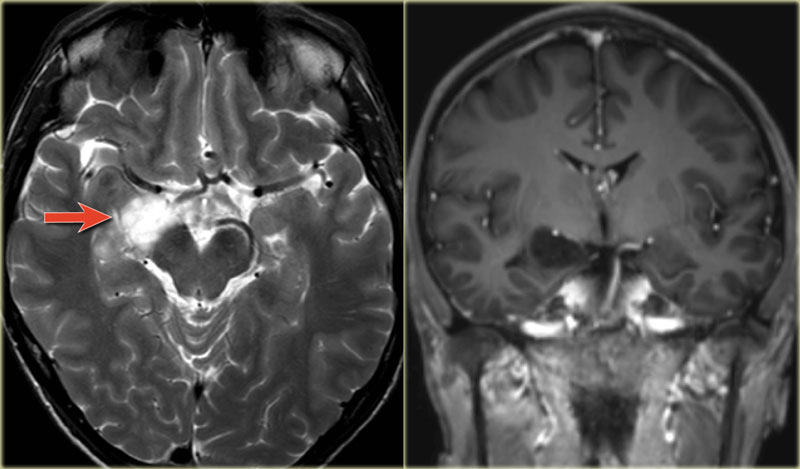 Hyperintense hippocampus due to a DNETHồi hải mã tăng tín hiệu do DNET
DNET mimicking mesial temporal sclerosis
Axial T2WI shows hyperintense, but enlarged hippocampus with a bubbly appearance.
This is typical for a DNET or dysembryoplastic neuroepithelial tumor, which we will discuss in a moment.
The coronal contrast-enhanced T1WI shows an enlarged hippocampus without uptake of contrast medium.DNET bắt chước xơ cứng thái dương gần
Trục T2WI cho thấy tăng tín hiệu, nhưng hồi hải mã to với hình dạng sủi bọt.
Đây là điển hình cho một khối u thần kinh DNET hoặc u biểu mô thần kinh loạn sản phôi, điều mà chúng ta sẽ thảo luận trong một thời điểm.
T1WI tăng cường thuốc cản quang cho thấy vùng hải mã bị to ra mà không hấp thu chất cản quang.
Focal Cortical DysplasiaLoạn sản vỏ não khu trú
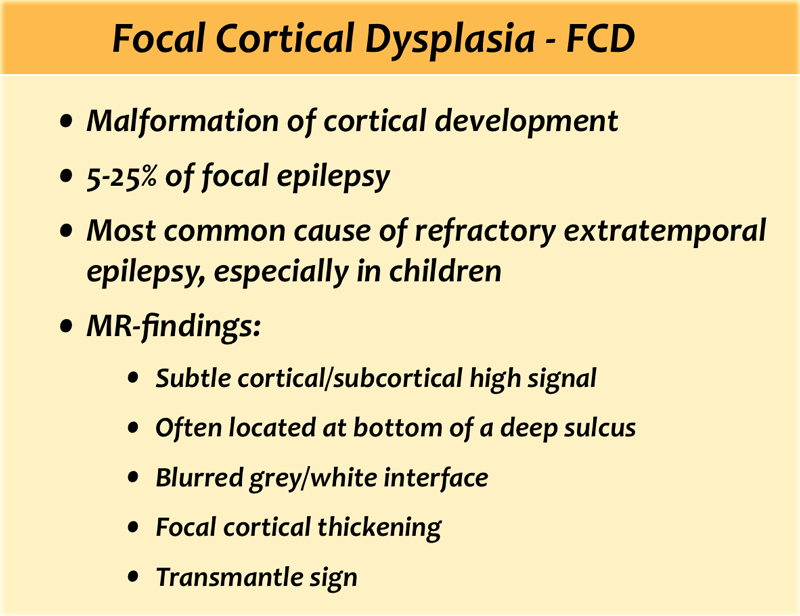
key findings những phát hiện chính
- Subcortical white matter hyperintensities Các vùng tăng tín hiệu chất trắng dưới vỏ
- Blurred grey-white matter interfaceGiao diện mờ xám-chất trắng
Focal cortical dysplasia is a congenital abnormality where the neurons fail to migrate in the proper formation in utero.
Loạn sản vỏ não khu trú là một bất thường bẩm sinh khi các tế bào thần kinh không di chuyển theo hình dạng thích hợp trong tử cung.
MRI findings may be very subtle or may even be negative, therefore a high index of suspicion is mandatory!
The most common findings are cortical or subcortical hyperintensities especially seen on FLAIR-images.
These are often found at the bottom of a deep sulcus.
Another finding is a blurred interface between grey and white matter, because the white matter looks a little bit like gray matter because it contains neurons that did not reach the cortex.Các dấu hiệu trên MRI có thể rất khó nhận biết hoặc thậm chí có thể âm tính, do đó chỉ số nghi ngờ cao là bắt buộc!
Các dấu hiệu phổ biến nhất là tăng cường vỏ não hoặc dưới vỏ não, đặc biệt là nhìn thấy trên hình ảnh FLAIR.
Chúng thường được tìm thấy ở đáy của một rãnh sâu.
Một phát hiện khác là giao diện mờ giữa màu xám và chất trắng, bởi vì chất trắng trông hơi giống chất xám vì nó chứa các tế bào thần kinh không đến được vỏ não.
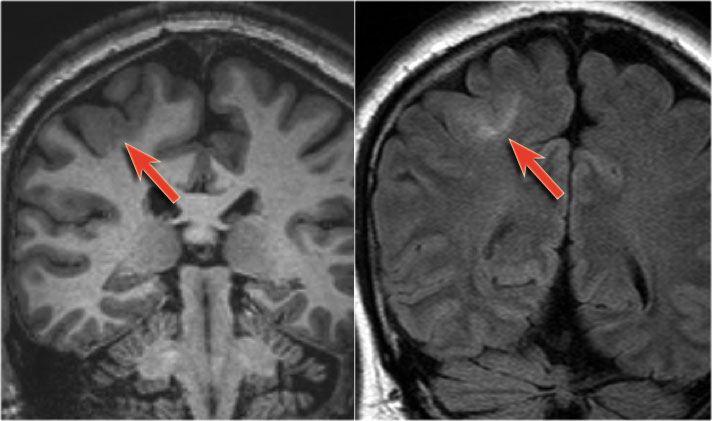 Focal cortical dysplasia - coronal T1WI and FLAIRLoạn sản vỏ não khu trú - T1WI và FLAIR
The images show typical focal cortical dysplasia.
There is cortical thickening and blurring of the grey/white matter junction on T1WI (left).
The FLAIR image on the right shows the subcortical hyperintensity.Hình ảnh cho thấy loạn sản vỏ não khu trú điển hình.
Có sự dày lên và mờ đi của vỏ não ở chỗ nối màu xám / chất trắng trên T1WI (trái).
Hình ảnh FLAIR bên phải cho thấy cường độ dưới vỏ.
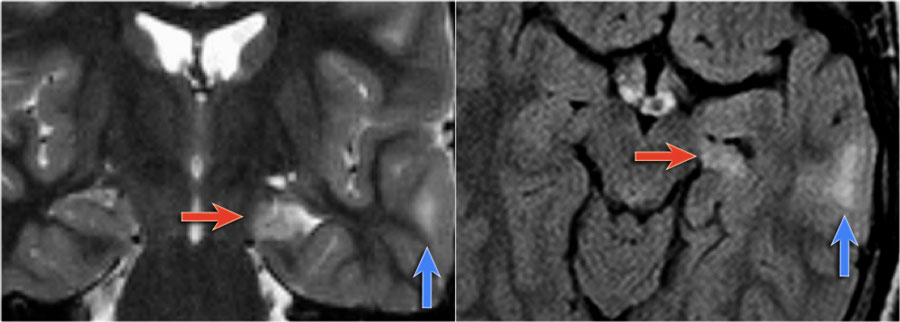 Dual pathology: MTS and focal cortical dysplasiaGiải phẫu bệnh kép: MTS và loạn sản vỏ não khu trú
The images demonstrate cortical and subcortical signal abnormalities on T2WI and FLAIR in the left temporal lobe indicating focal cortical dysplasia.
Notice associated T2/FLAIR hyperintense and shrunken hippocampus as a result of mesial temporal sclerosis, i.e. dual pathology. Hình ảnh cho thấy bất thường tín hiệu vỏ não và tín hiệu dưới vỏ trên T2WI và FLAIR ở thuỳ thái dương trái cho thấy loạn sản vỏ não khu trú.
Lưu ý T 2 / FLAIR tăng tín hiệu liên quan và thu nhỏ hồi hải mã do xơ cứng thái dương gần, tức là bệnh lý kép.
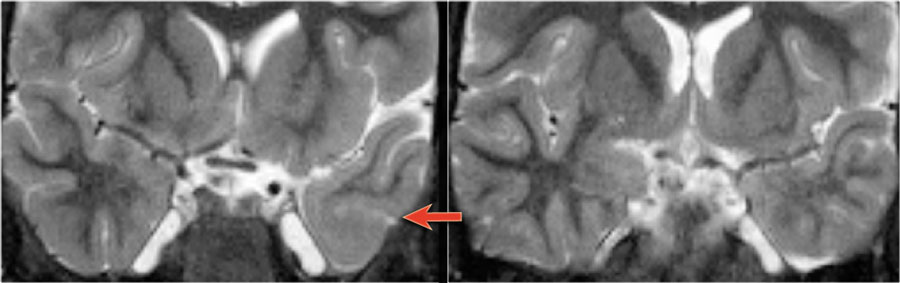 Focal cortical dysplasia. Coronal T2WILoạn sản vỏ não khu trú.T2WI vùng vành
Another case of focal cortical dysplasia.
Notice the hypoplastic left temporal lobe with cortical thickening (arrow) and atrophy of the white matter.Một trường hợp loạn sản vỏ não khu trú khác.
Lưu ý thuỳ thái dương trái giảm sản với vỏ dày lên (mũi tên) và teo thuỳ chất trắng.
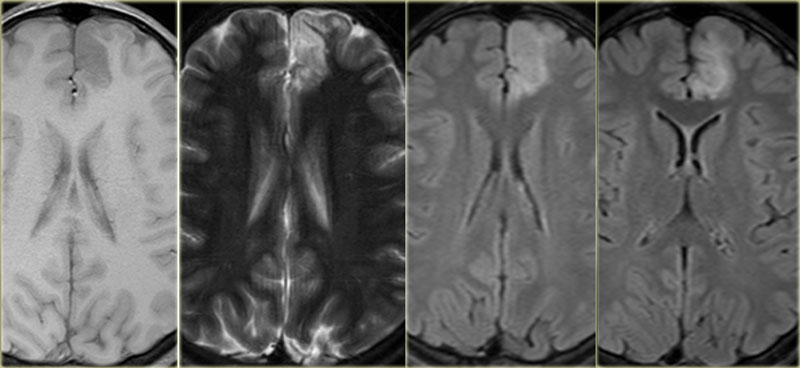 Focal cortical dysplasia. T1WI, T2WI and FLAIR.Loạn sản vỏ não khu trú, T1WI, T2WI và FLAIR.
Axial T1WI, T2WI and FLAIR-images of a 15 year old boy with epilepsy.
Notice thickening and hyperintensity of the cortex of the left superior frontal gyrus.
The FLAIR-images also show high signal in the subcortical white matter.
These findings are typical for focal cortical dysplasia.Hình ảnh T1WI, T2WI và FLAIR trục của một cậu bé 15 tuổi bị động kinh.
Lưu ý sự dày lên và tăng cường của vỏ não của thuỳ trán trên bên trái.
Hình ảnh FLAIR cũng cho thấy tín hiệu cao trong vỏ não chất trắng.
Những dấu hiệu này là điển hình cho loạn sản vỏ não khu trú.
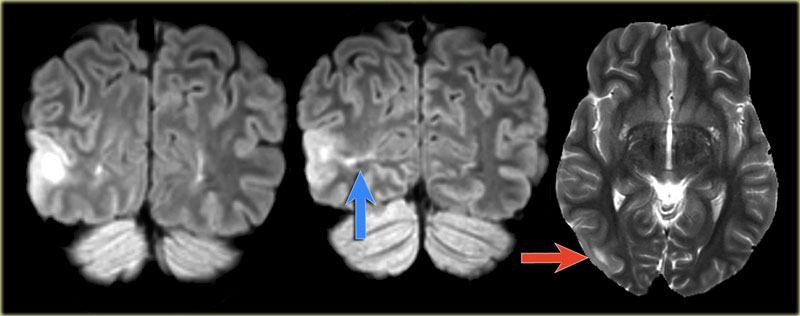 Focal cortical dysplasia in the right occipital lobe with transmantle signLoạn sản vỏ não khu trú ở thuỳ chẩm phải có dấu hiệu chuyển dạng
Transmantle signDấu hiệu chuyển dạng
Sometimes the hyperintensity is seen extending from the subcortical area to the margin of the ventricle.
This is called the transmantle sign.
This finding represents the arrested neuronal migration.Đôi khi cường độ tăng được nhìn thấy kéo dài từ vùng dưới vỏ não đến rìa tâm thất.
Đây được gọi là dấu hiệu chuyển từ.
Phát hiện này thể hiện sự di chuyển của tế bào thần kinh bị bắt giữ.
Images of a 27-year-old male with refractory occipital lobe epilepsy.
Coronal FLAIR and axial T2WI show T2-hyperintense cortical thickening and high signal in cortex and subcortical region.
Notice subcortical hyperintensity extending to the right ventricle indicating transmantle sign (blue arrow).Hình ảnh một bệnh nhân nam 27 tuổi bị động kinh thuỳ chẩm kháng trị.
FLAIR và T2WI trục cho thấy dày vỏ não T 2 - tăng tín hiệu và tín hiệu cao ở vỏ não và vùng dưới vỏ.
Lưu ý cường độ dưới vỏ não kéo dài đến tâm thất phải cho thấy dấu hiệu chuyển từ (mũi tên màu xanh).
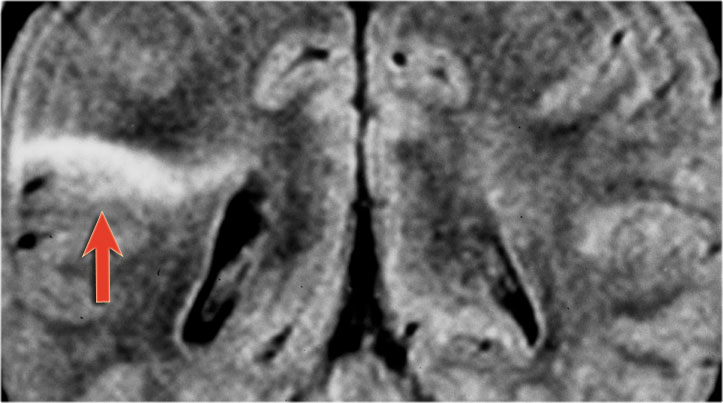 Focal cortical dysplasia - Transmantle sign.Loạn sản vỏ não khu trú - Dấu hiệu transmantle.
Transmantle sign seen in another patient with focal cortical dysplasia.Dấu hiệu transmantle thấy ở một bệnh nhân khác bị loạn sản vỏ não khu trú.
Cortical and glial scars - UlegyriaSẹo vỏ não và sẹo thần kinh đệm - Ulegyria
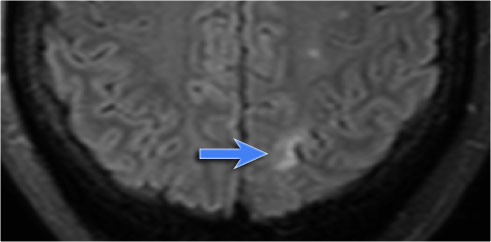
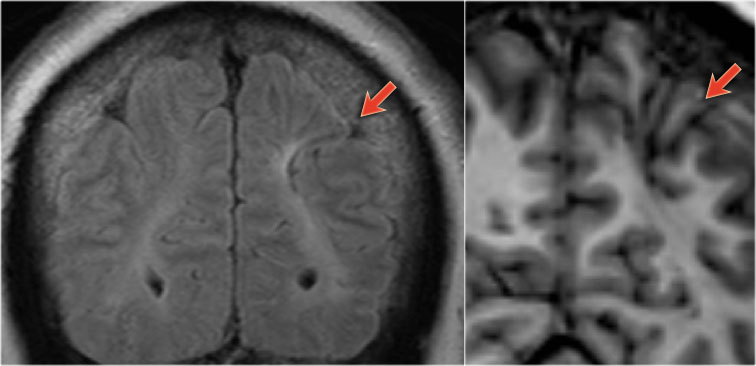 54-year-old patient with a history of perinatal asphyxia and longstanding refractory partial epilepsia. Left parietal scar in the parasagittal watershed area resulting in a shrunken cortex.Bệnh nhân 54 tuổi, có tiền sử ngạt chu sinh và động kinh bán phần kháng trị kéo dài, sẹo đỉnh bên trái vùng đầu nguồn cạnh dọc, kết quả là vỏ não co rút.
Cortical and glial scars usually result from meningitis or birth injury.
Ulegyria is a specific type of scar.
It is defined as cerebral cortex scarring due to perinatal ischemia.
Ulegyria typically affects full term infants.
In these infants there is greater perfusion to the apex of the gyri than to the cortex at the depth of the sulci.
The resulting pattern is that of a shrunken cortex in which the deep portions of the gyri are more shrunken than the superficial portions, leaving pedunculated gyri on long stalks with a mushroom appearance.
Ulegyria must be differentiated from microgyria.Sẹo vỏ não và sẹo thần kinh đệm thường là kết quả của viêm màng não hoặc chấn thương khi sinh.
Loét miệng là một loại sẹo đặc trưng.
Nó được định nghĩa là sẹo vỏ não do thiếu máu cục bộ chu sinh.
Loét miệng thường ảnh hưởng đến trẻ đủ tháng.
Ở những trẻ sơ sinh này, có sự tưới máu đến đỉnh của hồi não nhiều hơn đến vỏ não ở độ sâu của rãnh.
Kết quả là một vỏ não bị co lại, trong đó các phần sâu của hồi hải mã bị co lại nhiều hơn các phần bề mặt, để lại hồi hải mã có cuống trên các cuống dài với hình dạng giống như nấm.
Loét miệng phải được phân biệt với chứng dị ứng miệng.
 UlegyriaE-shop
MR will shows tissue loss and gliosis underneath a shrunken cortex.
The shrunken cortex is best appreciated on a 3D-T1WI because of its high resolution and the superior delineation of the cortex, while FLAIR will show the hyperintensity associated with the gliosis.
Therefore always use the FLAIR-sequence to search for hyperintensities in an epileptic patient and subsequently correlate these findings with the cerebral cortex in the affected area on high resolution T1WI.
Chụp cộng hưởng từ sẽ cho thấy mất mô và bệnh lý thần kinh đệm bên dưới vỏ não bị co lại.
Vỏ não bị co rút được đánh giá tốt nhất trên 3 D-T 1 WI vì độ phân giải cao và sự phân định vượt trội của vỏ não, trong khi FLAIR sẽ cho thấy cường độ tăng liên quan đến bệnh thần kinh đệm.
Do đó, luôn sử dụng trình tự FLAIR để tìm kiếm cường độ tăng trên bệnh nhân động kinh và sau đó tương quan những phát hiện này với vỏ não ở vùng bị ảnh hưởng trên T1WI độ phân giải cao.
Cavernoma
Cavernoma is also known as cavernous malformation or cavernous angioma.
It is a benign low flow vascular malformation with a tendency to bleed.
75 percent occur as solitary sporadic lesions and 10-30 percent occur as multiple lesions.
Cavernomas consist of locules of variable size that contain blood products in different stages of evolution which produces a popcorn appearance.
A complete hemosiderin rim surrounds the lesion, but not when there is a recent bleeding.
Unenhanced CT may show a hyperdense nodule or calcification, but in 50% of cases cavernomas will be occult on CT. U mạch hang còn được gọi là dị dạng hang hoặc u mạch hang.
Đây là một dị dạng mạch máu dòng chảy thấp lành tính có xu hướng chảy máu.
75% là tổn thương đơn độc lẻ tẻ và 10-30 phần trăm là tổn thương đa ổ.
Cavernomas bao gồm các ô có kích thước thay đổi có chứa các sản phẩm máu trong các giai đoạn tiến hóa khác nhau tạo ra hình dạng bỏng ngô.
Một vành hemosiderin hoàn chỉnh bao quanh tổn thương, nhưng không phải khi có chảy máu gần đây.
CT không tiêm thuốc cản quang có thể cho thấy nốt tăng tỷ trọng hoặc vôi hóa, nhưng trong 50% trường hợp, u thể hang sẽ bị che khuất trên CT.
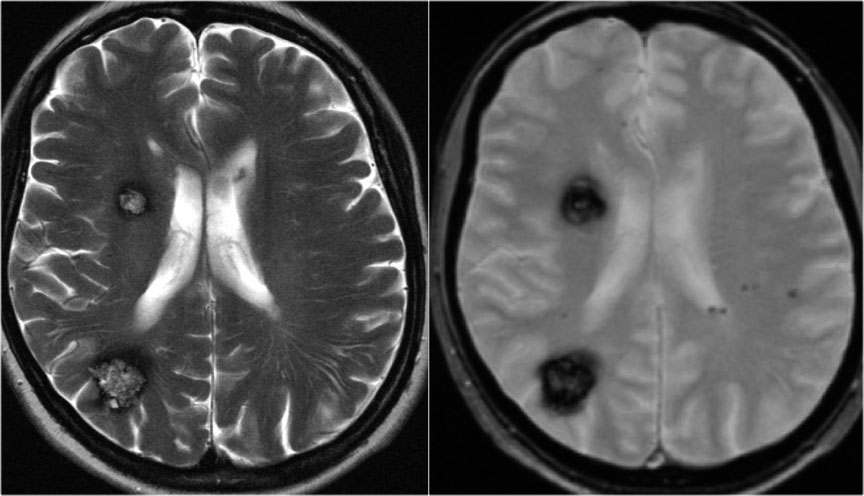
T2WI and T2* gradient echo show multiple cavernomas.
Notice the popcorn appearance with peripheral rim of hemosiderin on the T2WI.
The lesions are almost completely black on the gradient echo due to blooming artefacts.
T2* and susceptibility weighted imaging (SWI) markedly increase the sensitivity of MRI to detect small cavernomas.
The five black dots in the left cerebral hemisphere on the T2* are also cavernomas and are not visible on the T2WI.T2WI và T2 * gradient echo thấy nhiều u hang.
Nhận thấy có hình ảnh bỏng ngô với vành ngoại vi của hemosiderin trên T2WI.
Các tổn thương gần như hoàn toàn màu đen trên gradient echo do các đồ tạo tác nở.
T2 * và SWI làm tăng đáng kể độ nhạy của MRI để phát hiện các u thể hang nhỏ.
Năm chấm đen ở bán cầu não trái trên T2 * cũng là các khối u hang và không nhìn thấy được trên T2WI.
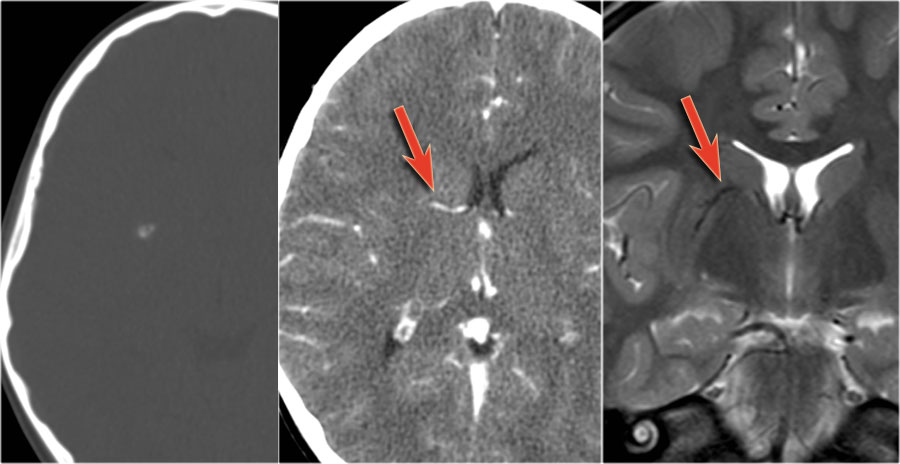 Cavernoma with associated DVA (arrow).U máu thể hang có liên quan DVA (mũi tên).
Cavernomas are associated with developmental venous anomalies (DVA's).
The unenhanced CT shows a small calcification in the right lentiform nucleus.
Enhanced CT shows a venous anomaly draining the cavernoma into the right internal cerebral vein.
Coronal T2WI shows the venous anomaly as a curvilinear flow void. U hang có liên quan đến bất thường tĩnh mạch phát triển (DVA).
CT không tiêm thuốc cản quang cho thấy một vôi hóa nhỏ ở bên phải nhân thấu kính.
CT tăng cường cho thấy một dị tật tĩnh mạch dẫn lưu u vào tĩnh mạch não trong bên phải.
T2WI vành cho thấy dị tật tĩnh mạch như một mất tín hiệu dòng chảy cong.
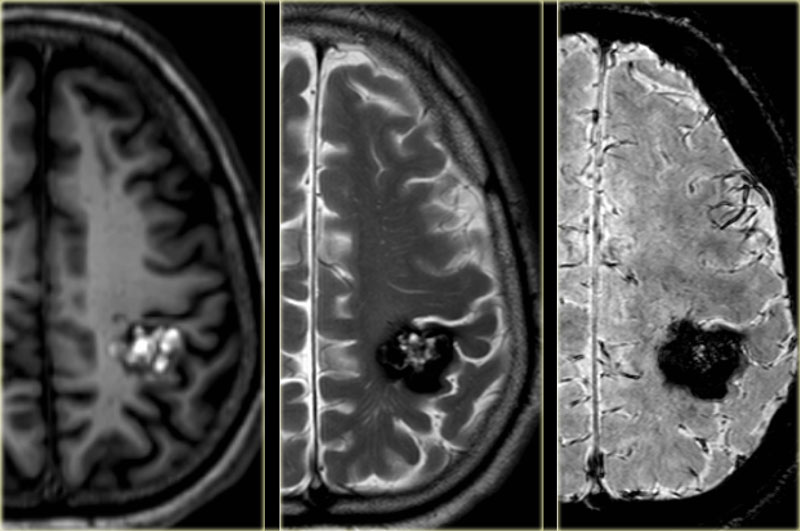
Cavernoma in the postcentral gyrus on T1WI, T2WI and SWI.
Notice popcorn appeance and blooming artefact.U hang sau hồi chuyển trung tâm trên T1WI, T2WI và SWI.
Chú ý đến sự xuất hiện của bỏng ngô và sự nở hoa.
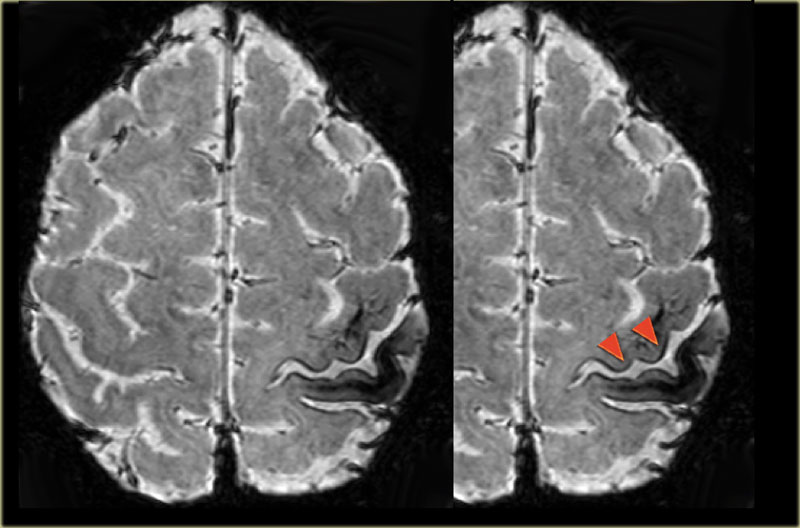
Same patient.
Notice the hemosiderin coating of the precentral gyrus consistent with superficial siderosis due to prior hemorrhage of the cavernoma (red arrowheads). Cùng một bệnh nhân.
Lưu ý lớp hemosiderin của hồi trước trung tâm phù hợp với tình trạng nhiễm sắt nông do xuất huyết trước đó của khối u (các đầu mũi tên màu đỏ).
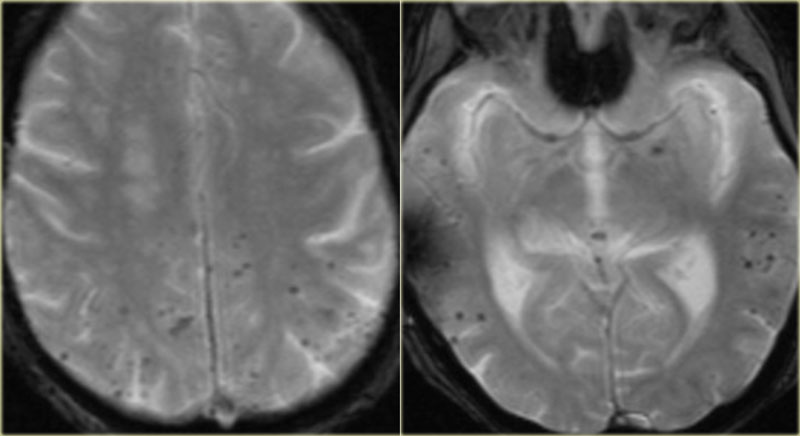 CAA - Multifocal subcortical black dots in a older patient.CAA - Chấm đen dưới vỏ não đa ổ ở bệnh nhân cao tuổi.
Differential diagnosis of microbleedsChẩn đoán phân biệt của vi chảy máu
In patients with multiple small black dots the differential diagnosis is: Ở những bệnh nhân có nhiều chấm đen nhỏ, chẩn đoán phân biệt là:
- Cavernomas U hang
- Cerebral amyloid angiopathy (CAA)
Asymmetric microbleeds in peripheral location seen in normotensive older person with lobar hemorrhage. CAA is commonly seen in demented patients.Bệnh mạch máu não dạng tinh bột (CAA)
Chảy máu vi thể không đối xứng ở vị trí ngoại vi thấy ở người cao tuổi bình thường có xuất huyết thuỳ não.CAA thường thấy ở bệnh nhân loạn thần. - Hypertensive microhemorrhages
Microbleeds in hypertensive patients younger than patients with CAA Vi xuất huyết tăng huyết áp
Chảy máu vi thể ở bệnh nhân tăng huyết áp trẻ hơn bệnh nhân có CAA - Diffuse axonal injury (DAI)
Posttraumatic hemorrhages in corpus callosum, subcortical white matter and brainstem. Tổn thương sợi trục lan toả (DAI)
Chảy máu sau chấn thương ở thể chai, dưới vỏ chất trắng và thân não.
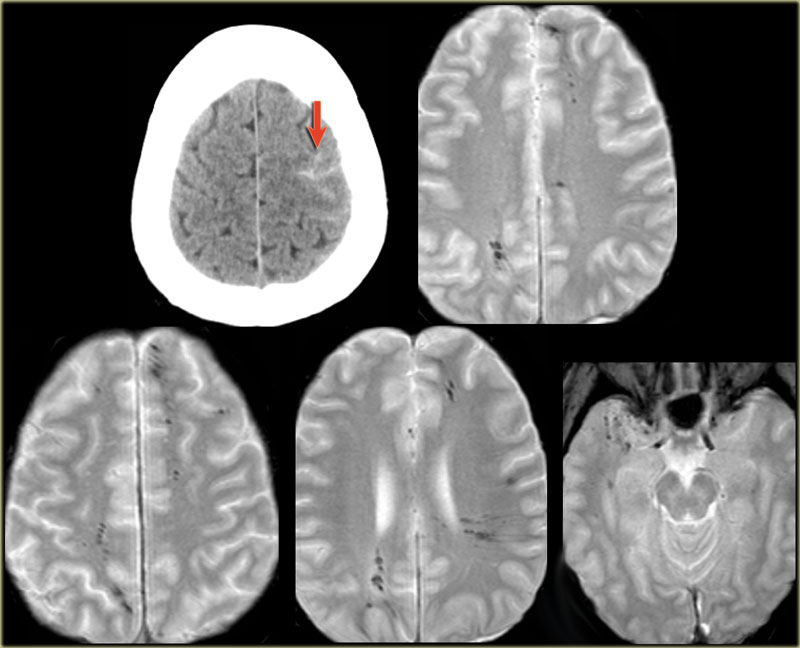 Diffuse axonal injuryTổn thương sợi trục lan toả
Diffuse axonal injury (DAI)
A 46 year old biker presented with seizures after being hit by a car.
CT-image shows only minimal subarachnoidal hemorrhage (arrow).
MRI was performed several weeks after the injury because of a change in personality.
T2*-images show multiple hemosiderin depositions at the interface between grey and white matter, consistent with diffuse axonal injury (DAI).
Notice that the location of the microbleeds is different from the peripheral located CAA-bleeds.Tổn thương sợi trục lan toả (DAI)
Một người đi xe đạp 46 tuổi bị co giật sau khi bị xe đâm.
Hình ảnh CT-scan chỉ cho thấy xuất huyết dưới nhện tối thiểu (mũi tên).
MRI được thực hiện vài tuần sau chấn thương do sự thay đổi về nhân cách.
Hình ảnh T2 * cho thấy nhiều lắng đọng hemosiderin ở giao diện giữa grey và chất trắng, phù hợp với tổn thương sợi trục lan toả (DAI).
Lưu ý rằng vị trí của các vi chảy máu khác với các CAA-chảy máu ngoại vi.
Epilepsy associated tumoursKhối u liên quan đến động kinh
All brain tumors may present with epilepsy, but there are some typically epilepsy associated tumors.
Tất cả các khối u não có thể xuất hiện với bệnh động kinh, nhưng có một số khối u điển hình liên quan đến động kinh.
These tumours share the following characteristics: Những khối u này có chung các đặc điểm sau:
- They arise in a cortical location.Chúng phát sinh ở một vị trí vỏ não.
- Often located in the temporal lobe. Thường nằm ở thuỳ thái dương.
- Closely related to developmental malformations.Liên quan chặt chẽ với dị tật phát triển.
- Typically seen in adolescents and young adults. Thường gặp ở thanh thiếu niên và thanh niên.
- Characterized by a benign behaviour, a slow growth, a sharp delineation and usually show absence of edema. Đặc trưng bởi một hành vi lành tính, tăng trưởng chậm, một đường nét rõ và thường không có phù nề.
- Show signs of chronicity, such as bone remodeling and scalloping of the adjacent skull.Có dấu hiệu mạn tính, chẳng hạn như tái cấu trúc xương và sụp đổ của hộp sọ lân cận.
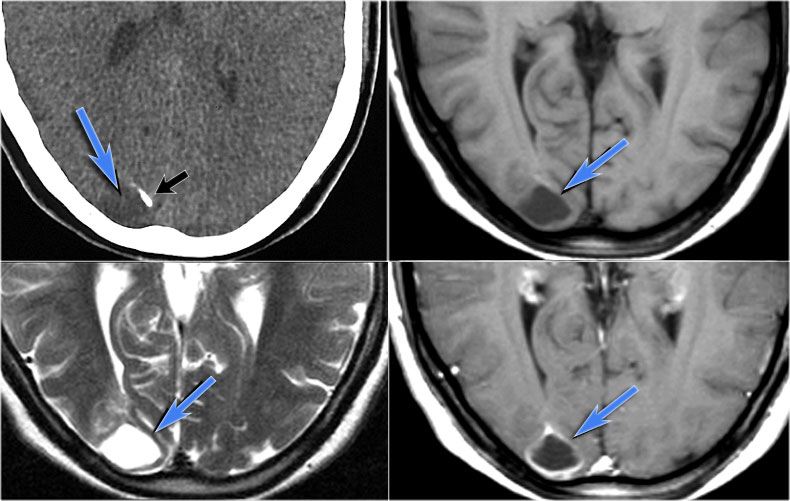 Ganglioglioma in the right occipital lobe presenting as a cystic mass with rim enhancement. Notice calcification on CT.U thần kinh đệm ở thuỳ chẩm phải biểu hiện dưới dạng khối dạng nang với ngấm thuốc dạng viền. Lưu ý vôi hóa trên CT.
GangliogliomaU hạch thần kinh đệm
key findings những phát hiện chính
- Typically presents as cyst with enhancing mural nodule, but may be entirely solid Thông thường biểu hiện dưới dạng nang với nốt thành tăng cường, nhưng có thể hoàn toàn đặc.
- Calcification in up to 50%Vôi hóa lên đến 50%
Ganglioglioma is the most common tumor associated with temporal lobe epilepsy.
Calcification is common in ganglioglioma and is an important distinguishing factor from DNET and pleomorphic xanthoastrocytoma.Ganglioglioma là khối u phổ biến nhất liên quan đến động kinh thuỳ thái dương.
vôi hóa là phổ biến trong u thần kinh đệm và là một yếu tố phân biệt quan trọng với DNET và u tế bào hình thoi đa hình.
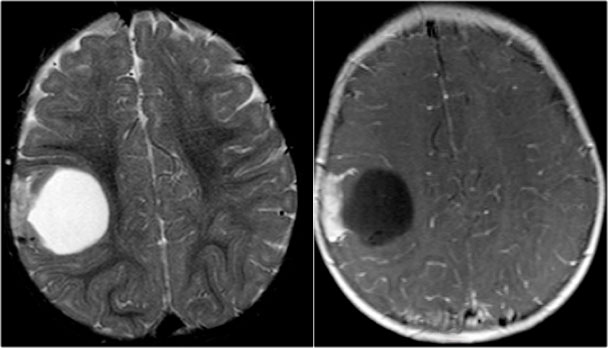 Ganglioglioma. T2WI and CE-T1WIU thần kinh đệm (Ganglioglioma) T2WI và CE-T 1WI
Ganglioglioma in a young child. Note large cyst with enhancement of mural solid tissue. U tế bào thần kinh đệm ở trẻ nhỏ. Lưu ý nang lớn với sự tăng cường của mô rắn ở thành.
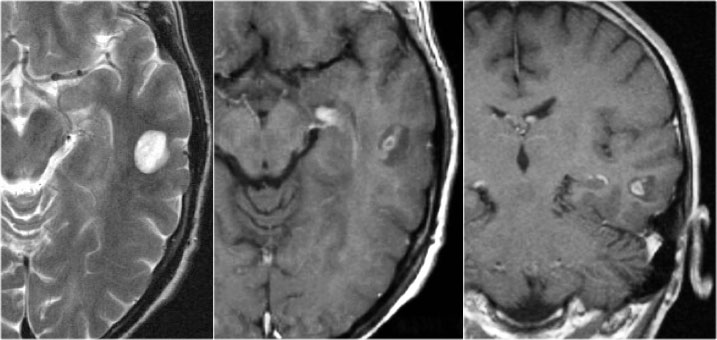 Ganglioglioma. T2WI and CE-T1WIU thần kinh đệm (Ganglioglioma) T2WI và CE-T 1WI
Small cystic ganglioglioma with a small enhancing nodule.U tế bào thần kinh đệm ống tuỷ nhỏ dạng nang với một nốt ngấm thuốc nhỏ.
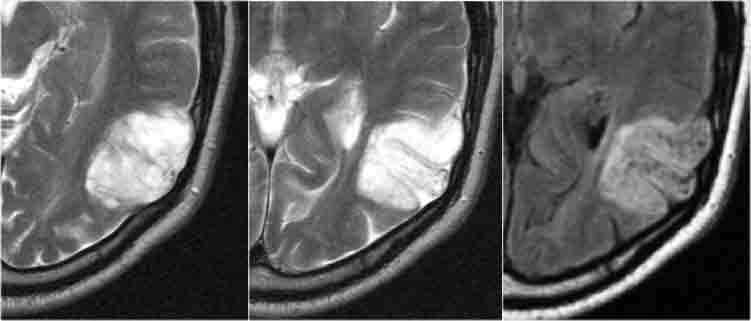 DNET: T2WI and FLAIR show characteristic bubbly appearance and swelling of affected gyri. Notice scalopping of the skull due to slow growth of the lesion.DNET: T2WI và FLAIR cho thấy hình dạng bong bóng đặc trưng và sưng nề của hồi não bị ảnh hưởng, chú ý đến sự sụp đổ của hộp sọ do sự phát triển chậm của tổn thương.
DNETDNETComment
key findings những phát hiện chính
- Swollen gyrus Con quay hồi chuyển
- Bubbly cystic appearance Xuất hiện nang bọt
- May be wedge shaped and point towards the ventricle Có thể có hình nêm và hướng về tâm thất
- Usually no or only little enhancement Thường không hoặc chỉ tăng cường ít
- Associated with focal cortical dysplasiaLiên quan với loạn sản vỏ não khu trú
DNET in typical cases present as a bubbly mass which expands the affected gyri.
The bubbly cystic appearance is seen as small cyst-like intratumoral structures that are very hyperintense on T2WI. DNET trong các trường hợp điển hình biểu hiện dưới dạng một khối sủi bọt làm giãn nở vùng hồi tràng bị ảnh hưởng.
Hình dạng nang sủi bọt được xem là các cấu trúc trong u nhầy nhỏ giống như nang, có kích thước rất tăng tín hiệu trên T2WI.
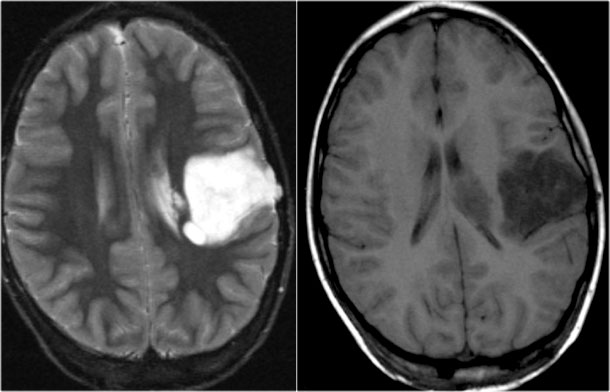 DNET. T2WI and T1WIDNET. T2WI và T1WI
DNET in an 11-year old boy presenting with refractory partial seizures.
The tumor shows a characteristic bubby appearance and there is subtle scalopping of the skull.DNET ở một cậu bé 11 tuổi bị co giật cục bộ kháng trị.
Khối u có hình dạng mũm mĩm đặc trưng và có vẩy da đầu của hộp sọ.
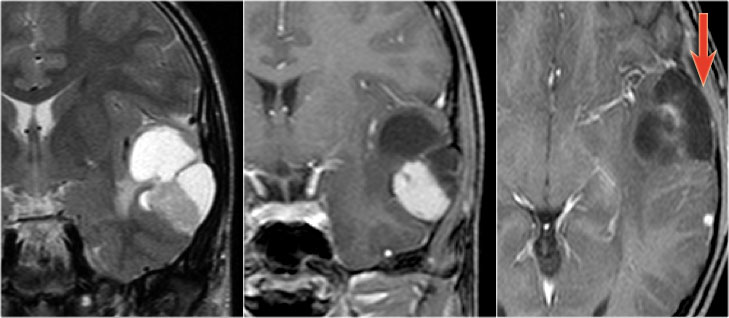 Pleomorphic xanthoastrocytoma on coronal T2WI and a coronal and axial CE-T1WI.Notice characteristic meningocerebral enhancement (arrow)U tế bào xanthoastrocytoma đa hình trên T2WI và CE-T 1WI và trục. Lưu ý đặc điểm tăng cường não màng não (mũi tên)
Pleomorphic xanthoastrocytomaU tế bào xanthoastrocytoma đa hình
key findings những phát hiện chính
- Supratentorial cyst with enhancing mural nodule which abuts the peripheral meningesNang trên lều với nốt thành tăng cường tiếp giáp với màng não ngoại vi
- Meningeal contrast enhancement Xương chày ngấm thuốc cản quang
- Peritumoral edema Phù quanh động mạch đùi
Pleomorphic xanthoastrocytoma (PXA) is a rare cause of temporal lobe epilepsy.
Peritumoral edema may be seen in PXA, while it is not a feature of either ganglioglioma or DNET.
Thickening and enhancement of the adjacent leptomeninges is highly characteristic but is not always present.
When meningeal involvement is not present, than a pleiomorphic xanthoastrocytoma is indistinguishable from a ganglioglioma. U tế bào xanthoastrocytoma đa hình (PXA) là một nguyên nhân hiếm gặp của động kinh thuỳ thái dương.
Phù quanh động mạch chủ có thể được nhìn thấy trong PXA, trong khi nó không phải là một đặc điểm của u thần kinh đệm hoặc DNET.
Dày và ngấm thuốc của màng não mềm liền kề là đặc trưng cao nhưng không phải lúc nào cũng có.
Khi không có tổn thương màng não, u tế bào xanthoastrocytoma đa hình không thể phân biệt được với u tế bào thần kinh đệm.
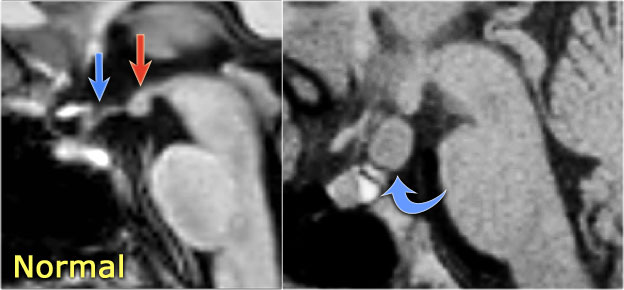 LEFT: Normal infundibular recess of the third ventricle (blue arrow) , mamillary bodies (red arrow)RIGHT: Tuber cinereum hamartoma (curved arrow)Bên trái: lõm bình thường của tâm thất thứ ba (mũi tên màu xanh), cơ thể tuyến vú (mũi tên màu đỏ) phải: củ cinereum hamartoma (mũi tên cong)
Hypothalamic hamartomaHamartoma vùng dưới đồi
key findings những phát hiện chính
- Non-enhancing enlargement of the tuber cinereum of the hypothalamusSự mở rộng không tăng cường của củ cinereum vùng dưới đồi
Hypothalamic hamartoma is also known as diencephalic or tuber cinereum hamartoma.
It represents nonneoplastic congenital grey matter heterotopia in the region of tuber cinereum of the hypothalamus.
It is seen in infants presenting with seizures and precocious puberty.Hamartoma vùng dưới đồi còn được gọi là diencephalic hoặc tuber cinereum hamartoma.
Nó đại diện cho dị tật bẩm sinh chất xám không tân sinh ở vùng củ cinereum của vùng dưới đồi.
Nó được thấy ở trẻ sơ sinh có biểu hiện động kinh và dậy thì sớm.
HemimegalencephalyĐau đầu bán phần
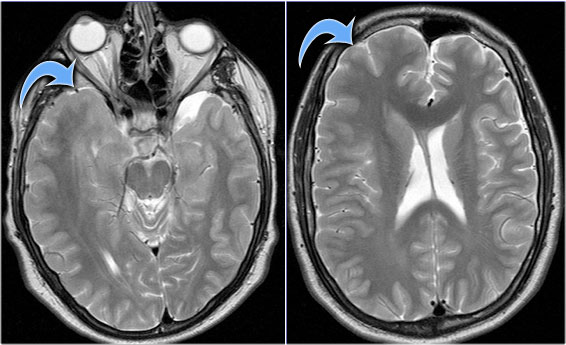 Hemimegalencephaly. (Courtesy of Alessandra D'Amico)Hemimegalencephaly. (Lịch sự của Alessandra D 'Amico)
key findings những phát hiện chính
- Enlarged hemisphere with ipsilateral ventriculomegalyBán cầu não to kèm theo bệnh não to thất cùng bên
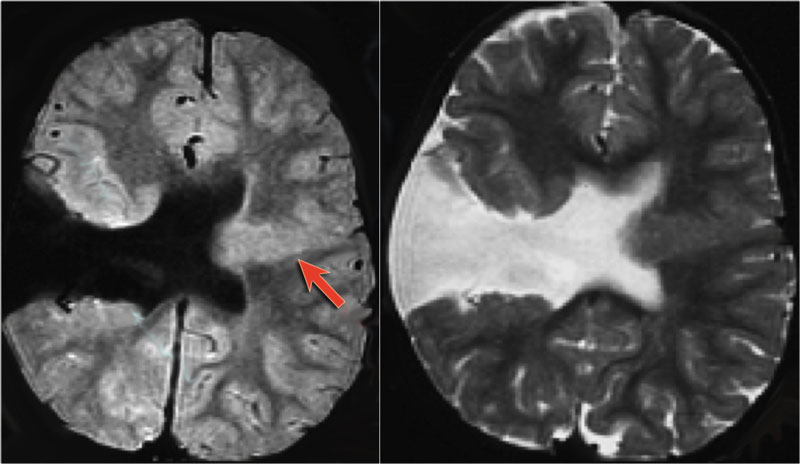
T2WI shows right hemimegalencephaly.
Notice the asymmetric skull and slightly enlarged lateral ventricle.
Hemimegalencephaly is the only condition in which an increase in parenchymal volume is associated with an increase in ipsilateral ventricular volume.T2WI cho thấy não phải.
Lưu ý hộp sọ không đối xứng và tâm thất bên hơi to.
Chứng não bán đồng nhất là tình trạng duy nhất trong đó sự gia tăng thể tích nhu mô có liên quan đến sự gia tăng khối lượng thất cùng bên.
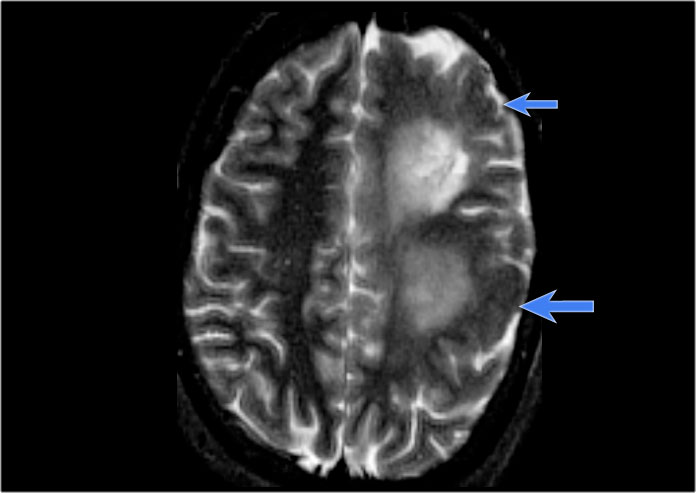 Left hemimegalencephaly with diffuse cortical dysplasia involving fronto-parietal regions (blue arrows) and diffuse white matter T2 hyperintensityĐầu não trái bán phần với loạn sản vỏ não lan toả vùng trán-phổi (các mũi tên xanh dương) và tăng cường chất trắng T2 lan toả
Hemimegalencephaly is a rare disease characterized by hamartomatous growth of one cerebral hemisphere or part of it.
Patients present with early seizures, macrocrania and severe developmental delay with contralateral hemiparesis.
The thickened cortex may show a wide spectrum of abnormalities, such as lissencephaly, pachygyria or polymicrogyria.
In the late stage, the involved hemisphere may atrophy due to constant seizure acitivity.
Most of the affected children die in the first years of life because of status epilepticus. Não bán cầu là một bệnh hiếm gặp, đặc trưng bởi sự phát triển của một bán cầu não hoặc một phần bán cầu não.
Bệnh nhân có biểu hiện động kinh sớm, đau đầu to và chậm phát triển nặng với liệt nửa người bên đối diện.
Vỏ não dày có thể cho thấy một loạt các bất thường, chẳng hạn như lissencephaly, pachygyria hoặc polymicrogyria.
Ở giai đoạn cuối, bán cầu liên quan có thể bị teo do co giật liên tục.
Hầu hết trẻ em bị ảnh hưởng tử vong trong những năm đầu đời vì tình trạng động kinh.
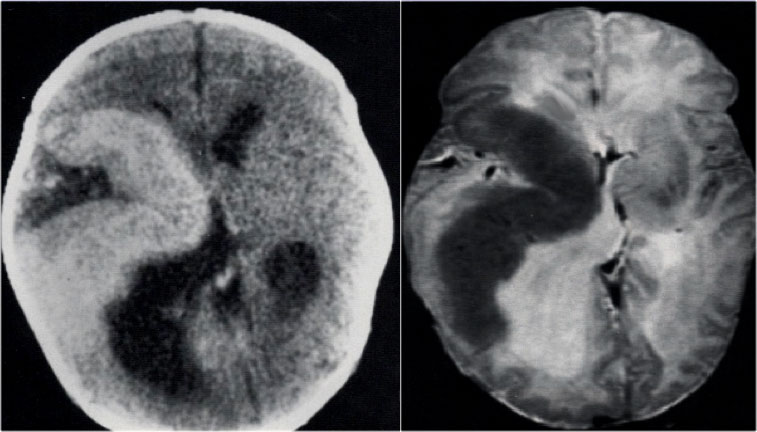 Hemimegalencephaly. Courtesy of Alessandra D'AmicoHemimegalencephaly. Nhờ Alessandra D'Amico
CT and T2WI in a patient with a right hemimegalencephaly.
There is dysplastic thick cortex and ventricular dilatation on the affected side.CT và T2WI ở bệnh nhân não phải.
Có loạn sản vỏ não dày và giãn não thất ở bên bị ảnh hưởng.
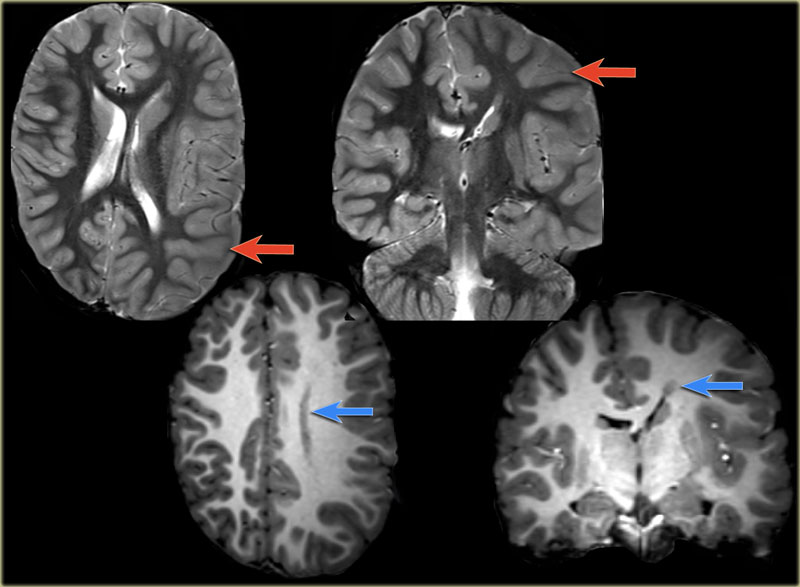
9-y-old girl with refractory nocturnal epilepsy.
MRI shows overgrowth of the left cerebral hemisphere.
T1WI shows heterotopic gray matter lining the left lateral ventricle (blue arrow).
In hemimegalencephaly it is important to exclude contralateral abnormalities, as these form a contraindication to hemispherectomy.Bé gái 9 tuổi, động kinh kịch phát về đêm.
MRI cho thấy sự phát triển quá mức của bán cầu não trái.
T1WI cho thấy dị vật chất xám nằm ở tâm thất trái (mũi tên màu xanh).
Trong bệnh não bán cầu, điều quan trọng là phải loại trừ các bất thường đối bên, vì những bất thường này tạo thành một chống chỉ định đối với phẫu thuật cắt bán cầu.
Rasmussen's EncephalitisViêm não Rasmussen
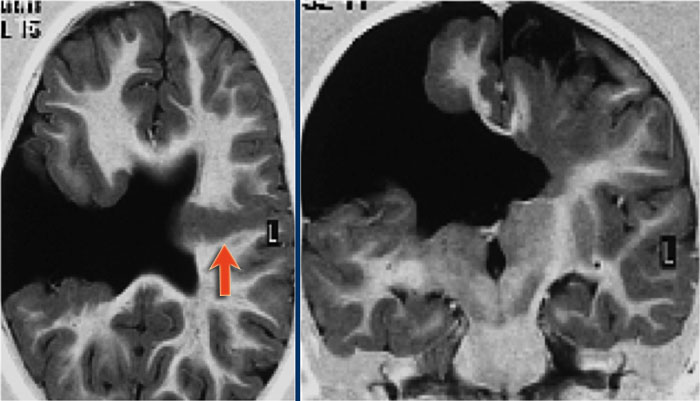
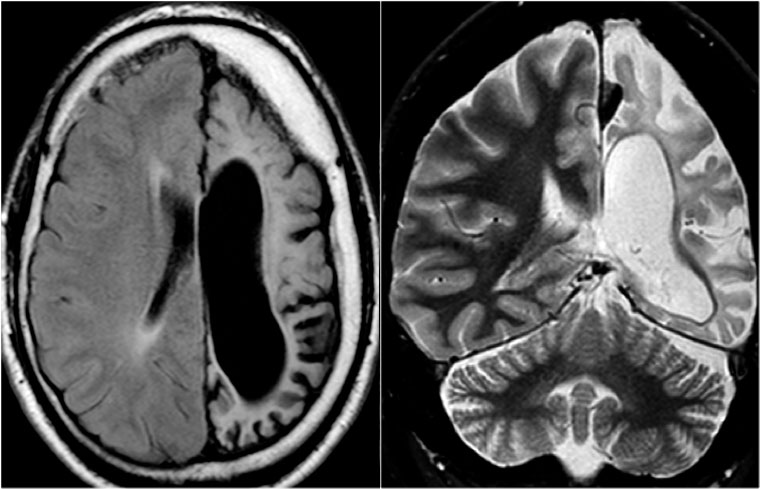 Rasmussen's encephalitis. Axial FLAIR and coronal T2WI show atrophy of the left cerebral hemisphere with enlargement of the lateral ventricle.Viêm não Rasmussen FLAIR trục và T2WI mạch vành cho thấy teo bán cầu não trái kèm theo phì đại thất ngoài.
key findings những phát hiện chính
- Intractable seizure activity in children Hoạt động co giật khó chữa ở trẻ em
- Progressive atrophy of the involved hemispere Teo tiến triển của khớp cắn
- Small hemisphere with large ventricle Bán cầu nhỏ với tâm thất lớn
Rasmussen's encephalitis is a progressive hemispheric atrophy of unknown origin.
Patient develop an increasing frequency of seizures and progressive hemiplegia.
Viêm não Rasmussen là một bệnh teo não bán cầu tiến triển không rõ nguyên nhân.
Bệnh nhân có tần suất co giật và liệt nửa người tiến triển.
Notice that, opposed to hemimegalencephaly, the smaller hemisphere is the site of abnormality, and the lateral ventricle is larger in the smaller hemisphere.Lưu ý rằng, trái ngược với chứng não bán cầu, bán cầu nhỏ hơn là vị trí bất thường và tâm thất bên lớn hơn ở bán cầu nhỏ.
Tuberous SclerosisXơ cứng củ
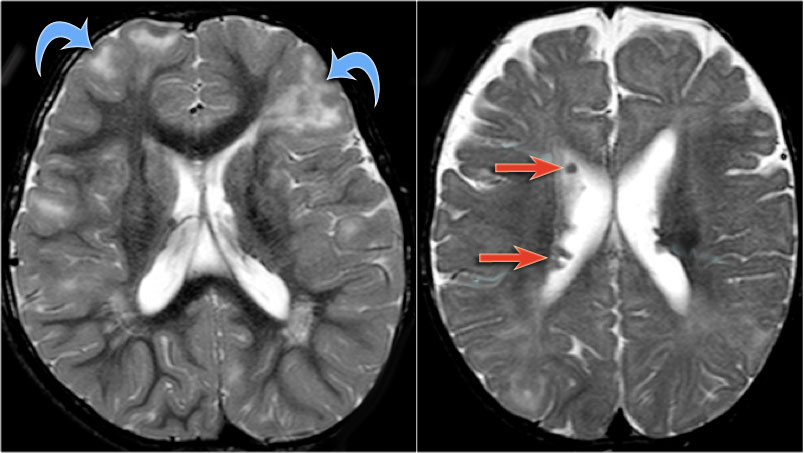 Axial T2w shows multiple tubers and white matter abnormalities (fig. a: arrows) and subependymal nodulesTrục T2w cho thấy nhiều củ và bất thường chất trắng (hình a: các mũi tên) và các nốt dưới hạch
key findings in the brain những dấu hiệu chính trong não
- Cortical hamartomas Hamartomas vỏ não
- Subependymal tubers Củ dưới thân mình
- Subependymal giant cell astrocytomaU sao bào tế bào khổng lồ dưới bao quy đầu
- White matter abnormalities Bất thường chất trắng
Tuberous sclerosis or Bourneville's disease is an inherited condition characterized by the presence of hamartomas in many organs including angiomyolipoma of the kidney, cardiac rhabdomyoma and cortical and subependymal tubers in the brain.
Some patients have lymphangioleiomatosis, a cystic lung disease seen in women.
The classic clinical triad is focal epilepsy, adenoma sebaceum and mental retardation (mnemonic: fits, zits and nitwits).
The cortical hamartomas are called tubers and are similar to cortical dysplasia.
Subependymal nodules are small lesions protruding into the lateral ventricles. Sometimes they are calcified.
Xơ cứng củ hay bệnh Bourneville là một bệnh di truyền đặc trưng bởi sự hiện diện của hamartomas ở nhiều cơ quan bao gồm u cơ mỡ mạch thận, u cơ vân tim và các ống vỏ não và dưới tuỷ ở não.
Một số bệnh nhân có u lympho mạch, một bệnh phổi nang thường gặp ở phụ nữ.
Bộ ba lâm sàng kinh điển là động kinh cục bộ, bã nhờn u tuyến và chậm phát triển tâm thần (mất trí nhớ: phù hợp, mụn và đần độn).
Hamartomas vỏ não được gọi là củ và tương tự như loạn sản vỏ não.
Nốt dưới thuỳ là những tổn thương nhỏ nhô ra não thất bên, đôi khi chúng bị vôi hóa.
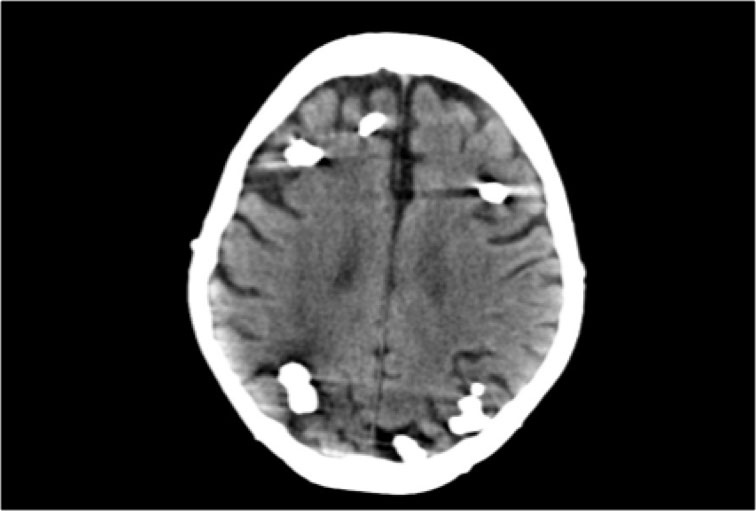
Seizure surgery in TSC is contemplated if a particular tuber can be implicated in seizure activity, or if a subependymal giant cell astrocytomas obstructs the foramen of Monro causing hydrocephalus. Phẫu thuật động kinh trong TSC được dự tính nếu một củ cụ thể có thể liên quan đến hoạt động động kinh, hoặc nếu một tế bào khổng lồ tế bào khổNG lồ dưới màng cứng làm tắc nghẽn lỗ Monro gây ra não úng thủy.
CT of a patient with Tuberous Sclerosis shows multiple cortical and subcortical calcifications.CT của một bệnh nhân bị xơ cứng củ cho thấy nhiều vôi hóa vỏ não và dưới vỏ.
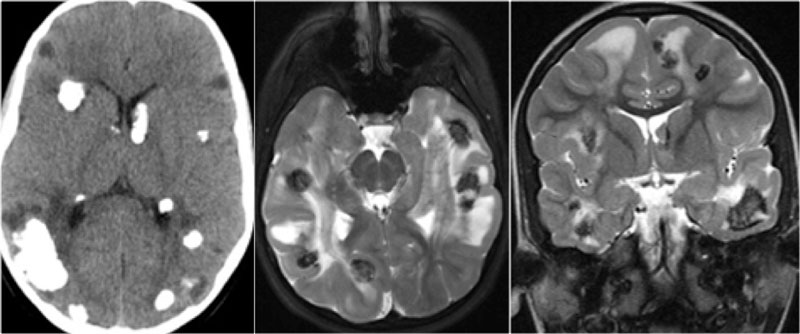 Tuberous Sclerosis - courtesy of the American Journal of Neuroradiology.Xơ cứng củ - do tạp chí American Journal of Neuroradiology.
CT and MRI in a patient with Tuberous Sclerosis.
There are multiple cortcal and subependymal nodules.
The CT shows that most of the lesions are calcified.CT và MRI ở bệnh nhân xơ cứng củ.
Có nhiều nốt ở hạch và dưới hạch.
CT cho thấy hầu hết các tổn thương đều bị vôi hóa.
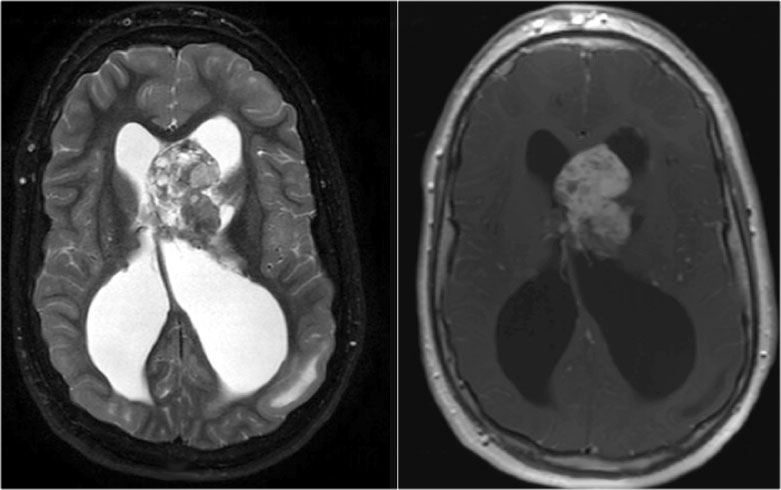
Subependymal giant cell astrocytoma (SEGA)
This is a tumor that develops from a subependymal nodule near the foramen of Monro.
They have a poor prognosis because they lead to obstruction of CSF flow.
They are characterized by marked enhancement and their typical location.U sao bào khổng lồ tế bào khổng lổ dưới mỏm yên (SEGA)
Đây là khối u phát triển từ nốt dưới mỏm yên gần lỗ Monro.
Chúng có tiên lượng xấu vì chúng dẫn đến tắc nghẽn dòng chảy của dịch não tuỷ.
Chúng được đặc trưng bởi sự tăng cường rõ rệt và vị trí điển hình của chúng.
Axial T2WI and T1WI-CE show a giant cell astrocytoma at the level of the left foramen of Monro causing obstructive hydrocephalus.
Also notice tuber on the left.T2WI và T1WI-CE cho thấy u sao bào khổng lồ ở mức lỗ Monro bên trái gây ra não úng thủy do tắc nghẽn.
Cũng chú ý củ bên trái.
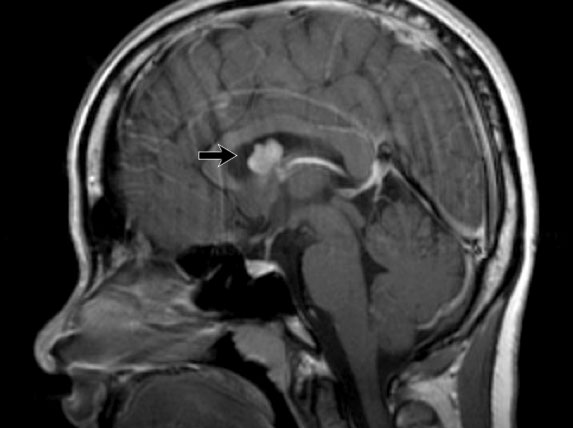
Sagittal T1WI post contrast shows a giant cell astrocytoma in the right foramen of Monro. T1WI sau khi tiêm thuốc cản quang cho thấy một u sao bào tế bào khổng lồ ở lỗ Monro bên phải.
Sturge-Weber SyndromeHội chứng Sturge-Weber
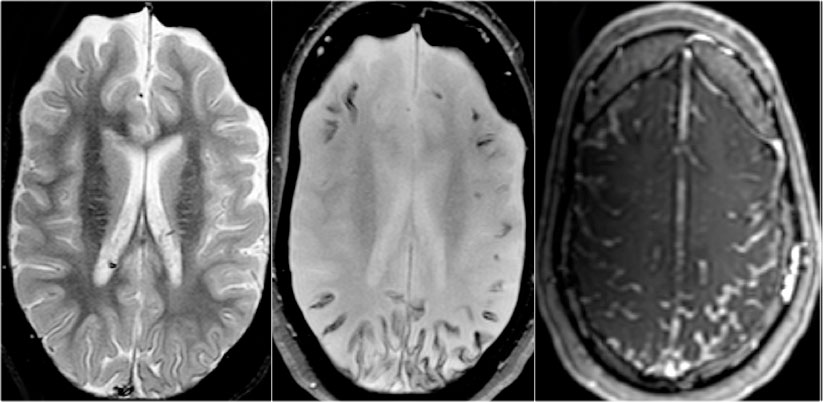 Sturge-Weber. T2WI, SWI and CE-T1WISturge-Weber. T2WI, SWI và CE-T 1WI
key findings những phát hiện chính
- Leptomeningeal enhancementTăng cường màng não màng lợn
- Cortical tram-track calcifications Đường ray điện vôi hóa
- Atrophy mainly posteriorly Teo chủ yếu là sau
Sturge-Weber is also called encephalotrigeminal angiomatosis.
It is a vascular malformation with capillary venous angiomas in the face (port-wine stain), choroid of the eye and leptomeninges.
Venous occlusion and ischemia lead to angiomatosis with cortical calcium deposition and atrophy
Clinical features are seizures, hemiparesis, anopsia, mental retardation and port-wine stain.Sturge-Weber còn được gọi là u mạch não.
Đây là một dị dạng mạch máu với các khối u tĩnh mạch mao mạch ở mặt (nhuộm rượu vang), màng đệm của mắt và màng não mềm.
Tắc tĩnh mạch và thiếu máu cục bộ dẫn đến u mạch với sự lắng đọng canxi vỏ não và teo mạch.
Đặc điểm lâm sàng là co giật, liệt nửa người, mất trương lực cơ, chậm phát triển tâm thần và nhuộm rượu vang.
The MR-images show leptomeningeal angiomatosis which is mainly localized in the occipital lobes.
Venous stasis and calcifications are best seen on the SWI. Hình ảnh cộng hưởng từ cho thấy u mạch màng não mềm, chủ yếu khu trú ở thuỳ chẩm.
Ứ máu tĩnh mạch và vôi hóa được nhìn thấy rõ nhất trên SWI.
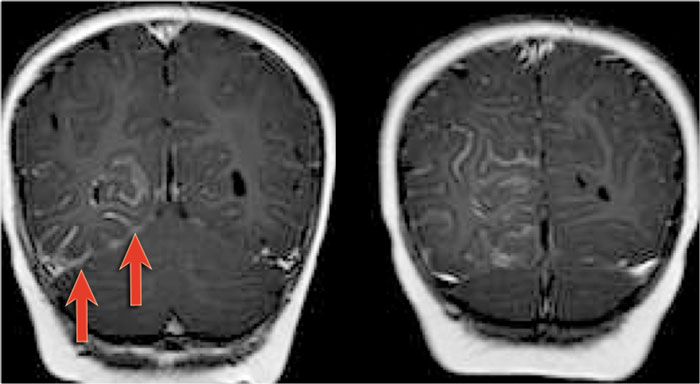 Sturge-Weber angiomatosis. CE-T1WI. Courtesy of Alessandra D' AmicoU mạch Sturge-Weber. CE-T 1 W. Nhờ Alessandra D ’ Amico
MRI in patients with Sturge-Weber can show: MRI ở bệnh nhân Sturge-Weber có thể cho thấy:
- Atrophy Teo
- High signal on T2WI due to gliosis Tín hiệu cao trên T2WI do bệnh gliosis
- Low signal in areas with calcifications. Tín hiệu thấp ở các khu vực có vôi hóa.
- Leptomeningeal enhancement Tăng cường màng não màng lợn
Coronal MR-images of a patient with Sturge-Weber show leptomeningeal enhancement in the right posterior hemispere. Hình ảnh MR của một bệnh nhân bị Sturge-Weber cho thấy sự tăng cường màng não mềm ở nửa sau bên phải.
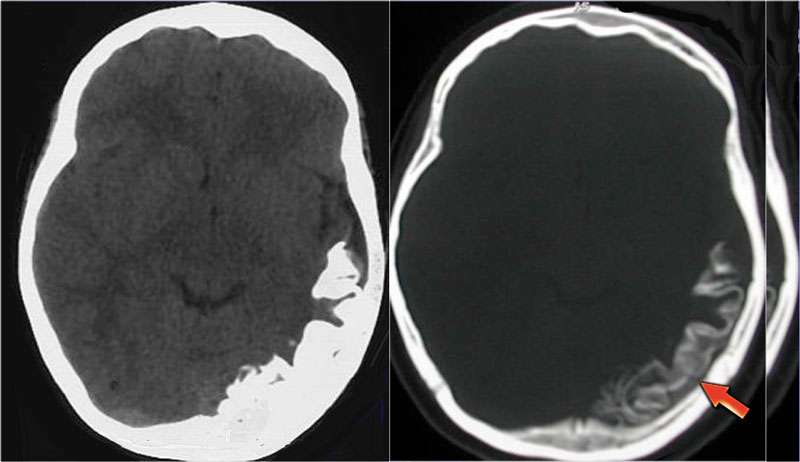 Sturge-Weber angiomatosis. Courtesy of Alessandra D' AmicoU mạch Sturge-Weber, tác giả Alessandra D ’ Amico
CT in a patient with Sturge-Weber shows huge cortical and subcortical tram-track calcifications involving the left posterior hemispere.CT ở bệnh nhân Sturge-Weber cho thấy đường ray vôi hóa lớn ở vỏ não và dưới vỏ liên quan đến nửa sau bên trái.
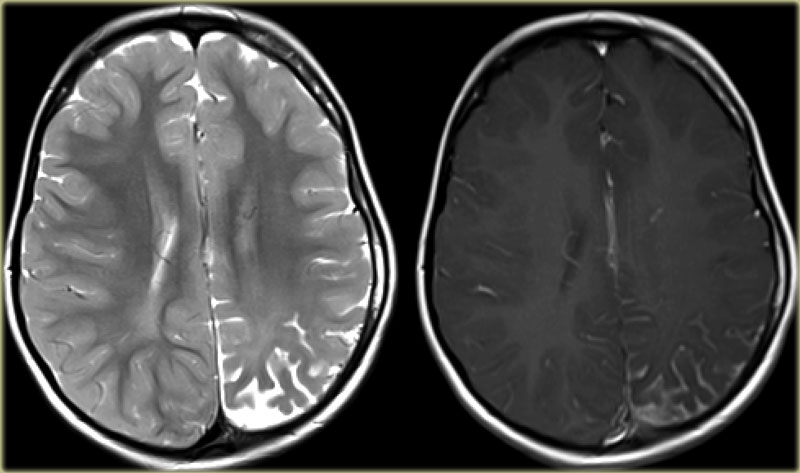 Sturge-Weber. T2WI and CE-T1WISturge-Weber. T2WI và CE-T 1WI
4-year-old boy with Sturge-Weber syndrome.
Notice atrophy of the left posterior cerebral hemisphere with leptomeningeal enhancement and thickening. Bé trai 4 tuổi mắc hội chứng Sturge-Weber.
Nhận thấy teo bán cầu não trái sau với màng mềm tăng cường và dày lên.
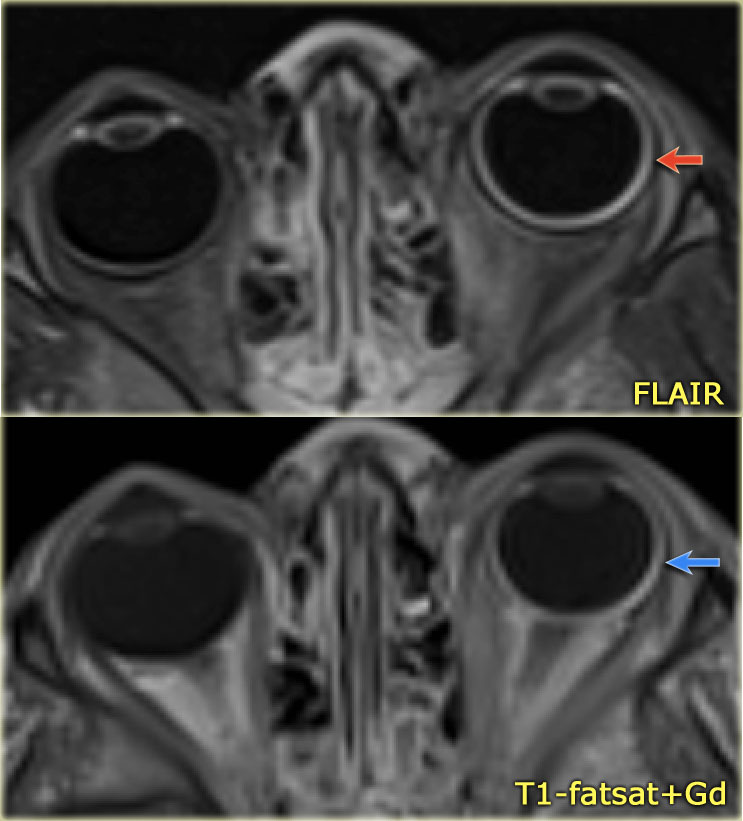 Sturge-Weber. Axial FLAIR and CE-T1WI with fatsat. Diffuse choroidal hemangiomaSturge-Weber. FLAIR trục và CE-T1WI với fatsat. Khuếch tán choroidal u máu
Diffuse choroidal hemangiomaKhuếch tán choroidal u máu
In Sturge-Weber a vascular malformation of the choroid of the eye is seen.
These patients present with buphthalmos (enlarged eye) due to increased intraocular pressure and hemianopsia.Trong Sturge-Weber, có thể thấy dị dạng mạch máu của màng đệm của mắt.
Những bệnh nhân này có thể có lồi mắt (mắt to) do tăng nhãn áp và chứng báng to.
Eye abnormalities in a 4-year-old boy with Sturge-Weber syndrome.
Notice FLAIR-hyperintensity (red arrow) and excessive enhancement of the wall of the left globe (blue arrow) consistent with a diffuse choroidal hemangioma.Những bất thường về mắt ở một cậu bé 4 tuổi mắc hội chứng Sturge-Weber.
Lưu ý sự tinh tế-tăng cường (mũi tên màu đỏ) và sự tăng cường quá mức của thành quả cầu bên trái (mũi tên màu xanh) phù hợp với u máu màng mạch khuếch tán.
PolymicrogyriaĐa hồi não nhỏ
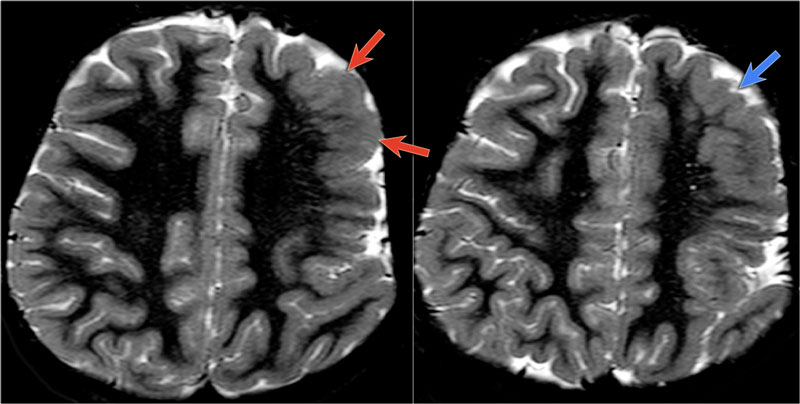
key findings những phát hiện chính
- Numerous small gyri Nhiều gyri nhỏ
- Predilection for Sylvian fissure Dự đoán khe nứt Sylvian
- Atrophy mainly posteriorly Teo chủ yếu là sau
- Anomalous venous drainage in areas of polymicrogyria Dẫn lưu tĩnh mạch bất thường ở các vùng đa vi sinh vật
Polymicrogyria is a malformation due to an alteration of the cortical development in the late stage of neuronal migration.
The deeper layers of the cortex form multiple small gyri with derangement of the normal lamination and sulcation. Đa vi sinh là một dị tật do sự thay đổi của sự phát triển vỏ não ở giai đoạn cuối của sự di chuyển thần kinh.
Các lớp sâu hơn của vỏ não tạo thành nhiều gyri nhỏ với sự rối loạn của lớp cán và rãnh bình thường.
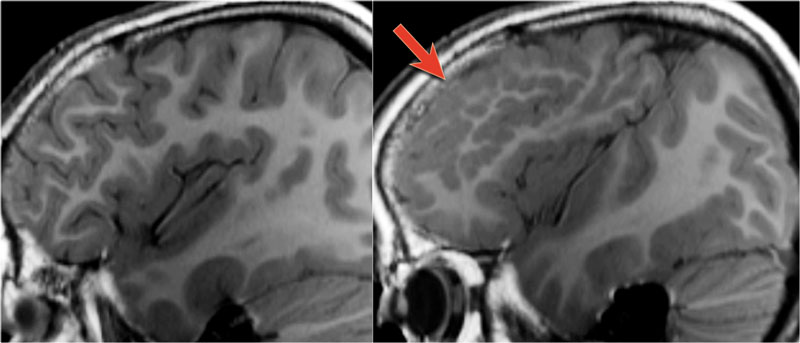 LEFT: normal RIGHT: polymicrogyria (arrow)Trái: Bình thường phải: Polymicrogyria (mũi tên)
The T1W-images show a comparison between normal lamination and sulcation on the left and polymicrogyria on the right (arrow).Hình ảnh T1W cho thấy sự so sánh giữa cán màng và rãnh màng bình thường ở bên trái và đa vi sinh vật ở bên phải (mũi tên).
HeterotopiaDị tật
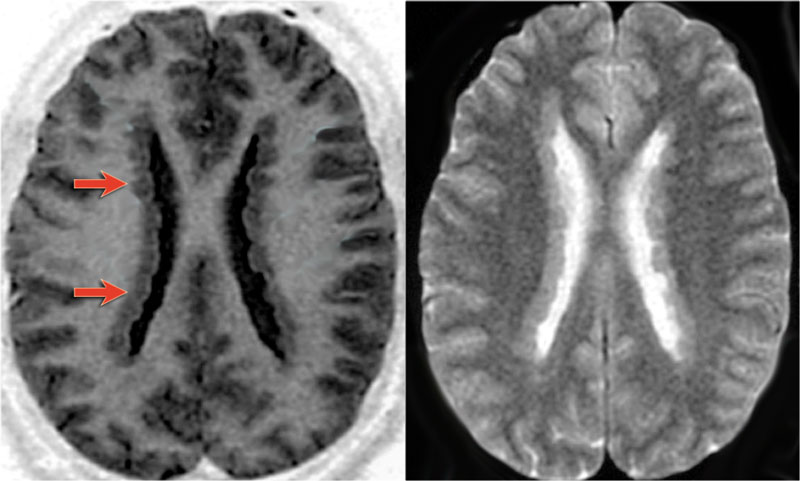 Heterotopia: subependymal nodules (arrows).Heterotopia: nốt dưới mỏm yên (các mũi tên).
Heterotopic Grey Matter results from an arrested migration of normal neurons along the radial path between the ventricular walls (ependyma) and the subcortical regions.
There are two types of heterotopia: subependymal and subcortical.
The most common clinical presentation is intractable seizures.
Heterotopia present as nodular foci of grey matter intensity on all sequences. They do not enhance. Chất xám dị hướng là kết quả của sự di chuyển bị chặn của các tế bào thần kinh bình thường dọc theo đường xuyên tâm giữa các thành tâm thất (u mủ) và các vùng dưới vỏ.
Có hai loại dị tật: dưới màng cứng và dưới vỏ.
Biểu hiện lâm sàng phổ biến nhất là co giật khó chữa.
Dị tật có dạng nốt với cường độ chất xám trên tất cả các chuỗi, không tăng cường.
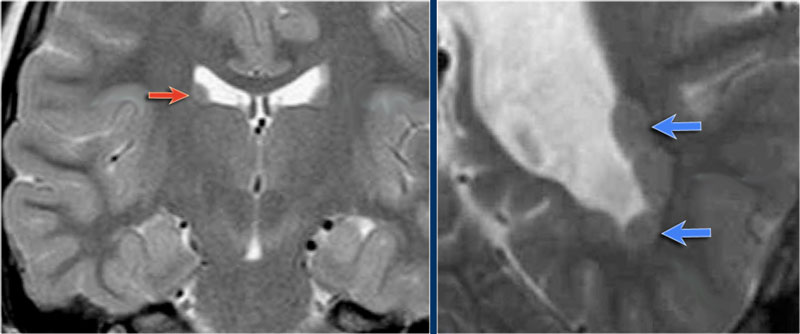 HeterotopiaDị tật
Images of a typical subependymal heterotopia.Hình ảnh của một dị tật dưới màng cứng điển hình.
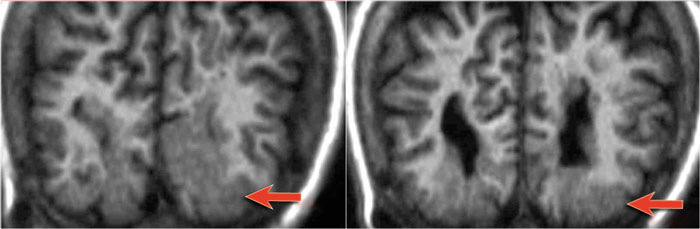 Courtesy of Alessandra D' AmicoĐược phép của Alessandra d 'Amico
Another case of heterotopia with typical subcortical nodules (arrows). Một trường hợp dị thể khác với nốt dưới vỏ điển hình (các mũi tên).
SchizencephalyKhe não bẩm sinh
 SchizencephalyKhe não bẩm sinh
Schizencephaly is a cleft in the brain that connects the lateral ventricle to the subarachnoid space.
The cleft is lined by polymicrogyric gray matter.
Open-lip schizencephaly is characterized by separation of the cleft walls.
Closed-lip schizencephaly is characterized by cleft walls in apposition to each other.
Patients have seizures and hemiparesis, which is proportional to the size of the cleft and are more common in the open-lip type. Đầu kẽ là một khe hở trong não kết nối não thất bên với khoang dưới nhện.
Khe hở được lót bởi polymicrogyric chất xám.
Bệnh tâm thần phân liệt thể hở môi được đặc trưng bởi sự tách biệt của các thành khe hở.
Bệnh tâm thần phân liệt môi kín được đặc trưng bởi các khe hở thành tạo thành từ các khe hỡ.
Bệnh nhân có co giật và liệt nửa người, tỷ lệ thuận với kích thước của khe hở và phổ biến hơn ở loại mở môi.
 Schizencephaly. Courtesy of Alessandra D' AmicoBệnh sọ não. Tác giả: Alessandra D ’ Amico
First study the images and then continue reading.Đầu tiên nghiên cứu hình ảnh và sau đó tiếp tục đọc.
This patient has a bilateral schizencephaly.
There is an open-lip type on the right and a closed-lip type on the left (red arrow).
Notice the track of grey matter in the left hemisphere on the axial image.
Bệnh nhân này có một chứng tâm thần phân liệt hai bên.
Có một loại môi hở ở bên phải và một loại môi kín ở bên trái (mũi tên màu đỏ).
Chú ý đường đi của chất xám ở bán cầu trái trên hình ảnh trục.
The differential diagnosis of schizencaphaly is porencephaly, which is also a cleft, but it is not lined by grey matter.Chẩn đoán phân biệt của schizencaphaly là porencephaly, cũng là một khe hở, nhưng nó không được lót bởi chất xám.

Charity
Hoạt động từ thiện
All the profits of the Radiology Assistant go to Medical Action Myanmar which is run by Dr. Nini Tun and Dr. Frank Smithuis sr, who is a professor at Oxford university and happens to be the brother of Robin Smithuis.Toàn bộ lợi nhuận của Radiology Assistant được chuyển cho Medical Action Myanmar, do bác sĩ Nini Tun và bác sĩ Frank Smithuis Sr. điều hành. Frank Smithuis Sr. là giáo sư tại Đại học Oxford và là anh em ruột của Robin Smithuis.
Click here to watch the video of Medical Action Myanmar and if you like the Radiology Assistant, please support Medical Action Myanmar with a small giftNhấp vào đây để xem video về Medical Action Myanmar và nếu bạn thích Trợ lý X quang, vui lòng hỗ trợ Medical Action Myanmar bằng một món quà nhỏ
ReferencesTài liệu tham khảo
-
by Abdel Razek AA et al.
AJNR. 2009 Jan;30(1):4-11
bởi Abdel Razek AA và cộng sự. -
by Barkovich J et al.
Amirsys 2007
bởi Barkovich J và cộng sự. -
by Barkovich AJ.
Neuroradiology 2010 52:479-487
bởi Barkovich AJ. -
by Bien CG, et al
Brain 2002; 125:1751-1759.
bởi Bien CG và cộng sự -
by Bien CG et al
Brain 128(pt 3):454-71,2005
bởi Bien CG và cộng sự -
by Chiapparini L, et al
Neuroradiology 2003; 45:171-183.
bởi Chiapparini L và cộng sự -
by Chinchure S et al
Neurol India 2010 May-Jun,58(3):361-70
Chinchure S và cộng sự -
by Demaerel P
JBR-BTR 2008 Nov-Dec;91(6):254-7
bởi Demaerel P. -
by Flores-Sarnat L
J Child Neurol 2002; 17:373-384
bởi Flores-Sarnat L -
by Hanefeld F, Kruse B, Holzbach U, Christen HJ, Merboldt KD, Hanicke W, Frahm J.
J Magn Reson Imaging 2008 aug,28(2):300-7
của Hanefeld F, Kruse B, Holzbach U, Christen HJ, Merboldt KD, Hanicke W, Frahm j. -
by Kim SJ et al.
Pediatr Neurol 27(4):282-8,2002
Kim SJ và cộng sự. -
by Maria BL, et al
J Child Neurol 1998; 13:606-618.
bởi Maria BL và cộng sự -
by Martin N, et al
Neuroradiology 1990; 31:492-497
bởi Martin N và cộng sự -
by Montenegro MA et al
Arch Neurol 2002; 59:1147-1153
bởi Montenegro MA và cộng sự -
by Radhakrishnqn R et al
Journ Clin Imag Sci 2011; 1(2):1-11
bởi Radhakrishnqn R và cộng sự -
by Urbach H et al
JNR 2004 Jun-Jul;25(6):916-26
bởi Urbach H và cộng sự -
by Tortori-Donati P, Rossi A
Springer 2005
bởi Tortori-Donati P, Rossi A. -
by Woermann FG, Vollmar C
Epilepsy Behav 2009 May;15(1):40-9
Tác giả: Vollmar C., Woermann FG