
Practical approach to Acute AbdomenTiếp cận thực hành trong bụng cấp
Radiology department of the Rijnland Hospital, Leiderdorp, the NetherlandsKhoa X quang Bệnh viện Rijnland, Leiderdorp, Hà Lan
Ngày đăng / cập nhật: 2005-10-20
Bản gốc trên radiologyassistant.nl ↗ · tải về lúc 2026-11-19 20:19 · bản dịch máy có chuẩn hóa thuật ngữ chẩn đoán hình ảnh
The 'acute abdomen' is a clinical condition characterized by severe abdominal pain, requiring the clinician to make an urgent therapeutic decision.
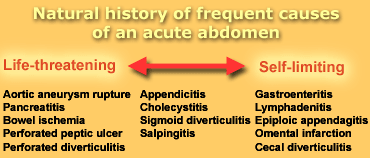
This may be challenging, because the differential diagnosis of an acute abdomen includes a wide spectrum of disorders, ranging from life-threatening diseases to benign self-limiting conditions (Table 1).
Indicated management may vary from emergency surgery to reassurance of the patient and misdiagnosis may easily result in delayed necessary treatment or unnecessary surgery.
Sonography and CT enable an accurate and rapid triage of patients with an acute abdomen.
We present practical guidelines on the radiological approach of these patients.
Interactive cases are presented in the menubar to test your knowledge.
Bụng cấp là một tình trạng lâm sàng đặc trưng bởi đau bụng dữ dội, đòi hỏi bác sĩ lâm sàng phải đưa ra quyết định điều trị khẩn cấp.
Điều này có thể là một thách thức, bởi vì chẩn đoán phân biệt của bụng cấp tính bao gồm một loạt các rối loạn, từ các bệnh đe doạ tính mạng đến các tình trạng tự giới hạn lành tính (Bảng 1).
Điều trị theo chỉ định có thể thay đổi từ phẫu thuật cấp cứu đến trấn an bệnh nhân và chẩn đoán sai có thể dễ dàng dẫn đến việc điều trị cần thiết bị trì hoãn hoặc phẫu thuật không cần thiết.
Siêu âm và CT cho phép phân loại chính xác và nhanh chóng các bệnh nhân bị bụng cấp.
Chúng tôi trình bày các hướng dẫn thực hành về phương pháp tiếp cận X quang của những bệnh nhân này.
Các trường hợp tương tác được trình bày trong thanh thực đơn để kiểm tra kiến thức của bạn.
Radiological strategyChiến lược X quang
 Xem hình gốc (EN)
Table 1. Common causes of acute abdomen from life-threatening to self-limiting.Bảng 1. Các nguyên nhân thường gặp của bụng cấp từ nguy hiểm đến tự hạn chế.
Before you perform an examination, obtain relevant information from the referring clinician.
Don't let the clinician simply 'order' a sonogram or CT, but discuss the patient's age and posture, laboratory results and the number one clinical diagnosis and differential diagnosis.
Based on that information and your own degree of confidence with the modalities decide for yourself whether to perform sonography or CT.
Sonography has the advantage of close patient contact, enabling assesment of the spot of maximum tenderness and the severity of illness without ionizing radiation.
In general the diagnostic accuracy of CT is higher than sonography.
In patients with inconclusive US-results, CT can serve as an adjunct to sonography, and vice versa.
We advocate the following two-step radiological approach of an acute abdomen.
1. Confirm or exclude the most common disease
2. Screen for general signs of pathology
You have to be familiar with all the diagnoses listed in Table 1 to be able to recognize them.
Trước khi bạn thực hiện một cuộc kiểm tra, hãy lấy thông tin liên quan từ bác sĩ lâm sàng giới thiệu.
Đừng để bác sĩ lâm sàng chỉ đơn giản là 'ra lệnh' siêu âm hoặc CT, nhưng hãy thảo luận về tuổi và tư thế của bệnh nhân, kết quả xét nghiệm và chẩn đoán lâm sàng số một và chẩn đoán phân biệt.
Dựa trên thông tin đó và mức độ tự tin của bạn với các phương thức quyết định cho chính mình có nên thực hiện siêu âm hoặc CT hay không.
Siêu âm có ưu điểm là tiếp xúc gần gũi với bệnh nhân, cho phép đánh giá điểm đau tối đa và mức độ nghiêm trọng của bệnh mà không cần bức xạ ion hóa.
Nhìn chung, độ chính xác chẩn đoán của CT cao hơn so với siêu âm.
Ở những bệnh nhân có kết quả siêu âm không kết luận, CT có thể được sử dụng như một phương pháp bổ trợ cho siêu âm, và ngược lại.
Chúng tôi ủng hộ phương pháp tiếp cận X quang hai bước sau đây trong một trường hợp bụng cấp.
1. Xác nhận hoặc loại trừ bệnh phổ biến nhất
2. Sàng lọc các dấu hiệu chung của bệnh lý
Bạn phải quen thuộc với tất cả các chẩn đoán được liệt kê trong Bảng 1 để có thể nhận ra chúng.
Clinics, laboratory, and plain abdominal filmPhòng khám, phòng thí nghiệm, và phim chụp bụng

The clinical presentation of patients with an acute abdomen is often nonspecific.
Both surgical and nonsurgical diseases may present with a similar clinical history and symptoms.
Laboratory findings (leucocyte count, erythrocyte sedimentation rate, CRP) are equally nonconclusive.
Findings may be normal in patients who need emergency surgery (such as appendicitis) and may be abnormal in patients without a surgical disease (like salpingitis).
A plain abdominal film has a limited value in the evaluation of abdominal pain.
A normal film does not exclude an ileus or other pathology and may falsely reassure the clinician. Biểu hiện lâm sàng của bệnh nhân bụng cấp thường không đặc hiệu.
Cả hai bệnh phẫu thuật và không phẫu thuật có thể có tiền sử lâm sàng và triệu chứng tương tự nhau.
Các kết quả xét nghiệm (số lượng bạch cầu, tốc độ máu lắng, CRP) không có giá trị kết luận.
Các dấu hiệu có thể bình thường ở những bệnh nhân cần phẫu thuật khẩn cấp (như viêm ruột thừa) và có thể bất thường ở những người không có bệnh phẫu thuật (như viêm vòi trứng).
Phim chụp bụng không có giá trị trong đánh giá đau bụng.
Phim bình thường không loại trừ tắc ruột hoặc các bệnh lý khác và có thể làm bác sĩ lâm sàng yên tâm sai.
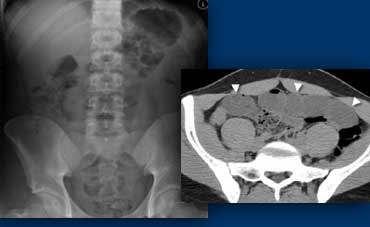 LEFT: Plain abdominal film in a patient with an acute abdomen, showing no abnormalities. RIGHT: Subsequent CT shows distended small bowel loops (arrowheads) that are not seen on plain abdominal film because they are filled with fluid only and do not contain intraluminal air.Trái: phim bụng trơn ở bệnh nhân có bụng cấp, không có biểu hiện bất thường. Bên phải: CT tiếp theo cho thấy các quai ruột non (các đầu mũi tên) bị phồng không thấy trên màng bụng đơn giản vì chúng chỉ chứa đầy chất lỏng và không chứa không khí bên trong.
An ileus may not be appreciated on a plain abdominal film if bowel loops are filled with fluid only without intraluminal air (figure).
Alternatively if a plain abdominal film does indicate an ileus than sonography or CT are usually needed to identify its cause.
Thus, a plain abdominal film is seldomly useful, with the exception of detection of kidney stones or a pneumoperitoneum.
For all other indications use sonography or CT.Có thể không đánh giá được hồi tràng trên phim chụp bụng nếu các quai ruột chỉ chứa đầy dịch mà không có không khí trong lòng ổ bụng (hình).
Ngoài ra, nếu một phim chụp bụng đơn giản cho thấy tắc ruột thì siêu âm hoặc CT thường cần thiết để xác định nguyên nhân của nó.
Do đó, phim chụp bụng thường ít khi hữu ích, ngoại trừ phát hiện sỏi thận hoặc tràn khí ổ bụng.
Đối với tất cả các chỉ định khác, sử dụng siêu âm hoặc CT.
Confirm or exclude the most common diseaseXác nhận hoặc loại trừ bệnh phổ biến nhất

Many disorders may cause an acute abdomen, but fortunately only a few of these are common and clinically important.
Focus on confirming or excluding these frequent disorders:Nhiều rối loạn có thể gây ra bụng cấp tính, nhưng may mắn thay chỉ có một vài trong số này là phổ biến và quan trọng về mặt lâm sàng.
Tập trung vào việc xác nhận hoặc loại trừ các rối loạn thường gặp này:
RLQ : AppendicitisRLQ: viêm ruột thừa
Pain in the RLQ, regardless of any other symptom or laboratory results, should be considered to be appendicitis until proven otherwise.
If you are unable to find the appendix you cannot rule out the diagnosis of appendicitis unless a good alternative diagnosis is found.
If you do not find the appendix and there is no altermative diagnosis call the results of the examination indeterminate. Do not call it:' no appendicitis'.Đau ở RLQ, bất kể bất kỳ triệu chứng hoặc kết quả xét nghiệm nào khác, nên được coi là viêm ruột thừa cho đến khi được chứng minh khác.
Nếu bạn không thể tìm thấy ruột thừa, bạn không thể loại trừ chẩn đoán viêm ruột thừa trừ khi tìm thấy một chẩn định thay thế tốt.
Nếu bạn không tìm thấy ruột thừa và không có chẩn đoán thay đổi, hãy gọi kết quả kiểm tra là không xác định. Đừng gọi nó: 'không viêm ruột thừa'.
 Normal appendix : Longitudinal (A) sonogram depicts a blind-ending tubular structure (arrowheads) with 'gut-signature', with a maximum outer diameter of 6 mm, with noninflamed surrounding fat. On an axial view (B) the appendix can be compressed crossing the iliac vessels.Siêu âm ruột thừa bình thường: Siêu âm dọc (A) mô tả cấu trúc ống mù (các đầu mũi tên) có “chữ ký ruột ”, đường kính ngoài tối đa 6 mm, có mỡ xung quanh không bị viêm. Trên mặt cắt dọc (B), ruột thừa có thể được nén qua các mạch máu chậu.
Normal Appendix.
Your first task is to identify the appendix.
At sonography and CT the appendix is seen as a blind-ending nonperistaltic tubular structure arising from the base of the cecum.
Do not mistake a small bowel loop for the appendix.
Secondly determine if the appendix is normal or inflamed.
The outer-to-outer diameter of the appendix is the most important imaging criterium.
Although an overlap of appendiceal diameters in normal and inflamed appendices can incidentally be found, a threshold value of 6-7 mm is generally used. Ruột thừa bình thường.
Nhiệm vụ đầu tiên của bạn là xác định ruột thừa.
Trên siêu âm và CT, ruột thừa được xem như một cấu trúc ống không nhu động có đầu mù phát sinh từ đáy manh tràng.
Đừng nhầm lẫn một vòng lặp ruột non với ruột thừa.
Thứ hai, xác định xem ruột thừa là bình thường hay bị viêm.
Đường kính ngoài-bên ngoài của ruột thừa là tiêu chuẩn chẩn đoán hình ảnh quan trọng nhất.
Mặc dù có thể tình cờ tìm thấy sự chồng chéo của đường kính ruột thừa ở ruột thừa bình thường và ruột thừa bị viêm, giá trị ngưỡng 6-7 mm thường được sử dụng.
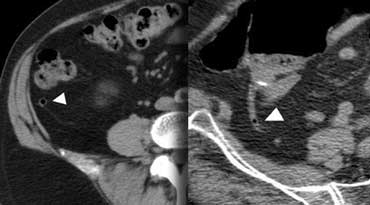 Normal appendix: CT shows an air-containing non-distended appendix (arrowheads), with homogeneous low-density periappendiceal fat.Bình thường ruột thừa: CT cho thấy một ruột thừa không giãn chứa không khí (các đầu mũi tên), với mỡ quanh ruột thừa mật độ thấp đồng nhất.
A normal appendix has a maximum diameter of 6 mm, is surrounded by homogeneous non-inflamed fat, is compressible and often contains intraluminal gas. Ruột thừa bình thường có đường kính tối đa 6 mm, được bao quanh bởi mỡ không viêm đồng nhất, có thể nén và thường chứa khí trong lòng.
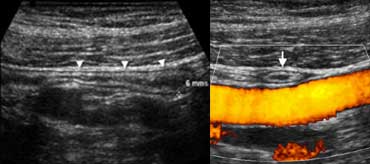
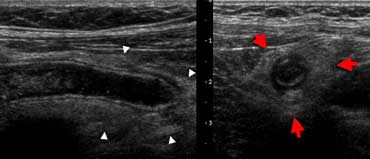 Inflamed appendix at sonography. Longitudinal (A) and transverse (B) cross-section show a distended noncompressible appendix, surrounded bij hyperechoic inflamed fat (arrowheads).Ruột thừa viêm trên siêu âm. Mặt cắt ngang dọc (A) và ngang (B) cho thấy ruột thừa giãn không nén được, bao quanh là mỡ bị viêm tăng âm (đầu mũi tên).
Inflamed Appendix
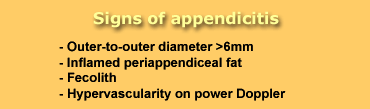
An inflamed appendix has a diameter larger than 6 mm, and is usually surrounded by inflamed fat. The presence of a fecolith or hypervascularity on power Doppler strongly supports inflammation. Viêm ruột thừa
ruột thừa bị viêm có đường kính lớn hơn 6 mm, và thường được bao quanh bởi mỡ bị viêm Sự hiện diện của một fecolith hoặc tăng mạch trên Doppler điện hỗ trợ mạnh mẽ cho tình trạng viêm.
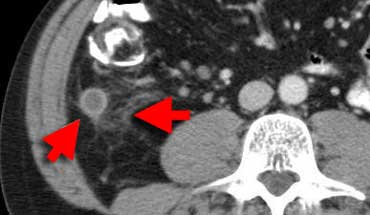 Inflamed appendix at CT. The appendix (arrows) is fluid-filled and distended with periappendiceal fat-stranding.Ruột thừa bị viêm trên CT.ruột thừa (các mũi tên) chứa đầy dịch và phồng lên với thâm nhiễm mỡ quanh ruột thừa.
CT depicts an inflamed appendix as a fluid-filled blind-ending tubular structure surrounded by fat-stranding.
In the case on the left a hyper-attenuating wall is seen on the enhanced CT.
In patients who lack intra-abdominal fat the use of iv. contrast can be helpfull in depicting the inflamed appendix.
CT mô tả một ruột thừa bị viêm như một cấu trúc ống mù chứa đầy dịch bao quanh bởi thâm nhiễm mỡ.
Trong trường hợp ở bên trái, một bức tường tăng cường được nhìn thấy trên CT tăng cường.
Ở những bệnh nhân thiếu mỡ trong ổ bụng, việc sử dụng thuốc cản quang có thể hữu ích trong việc mô tả ruột thừa bị viêm.
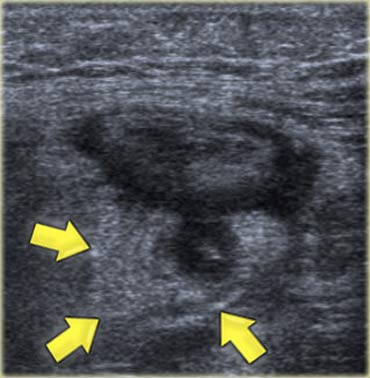 Sigmoid diverticulitis at sonography. A hypoechoic thickened diverticulum is surrounded by hyperechoic inflamed fat (arrows).X quang viêm túi thừa, túi thừa dày giảm âm, bao quanh là mô mỡ viêm tăng âm (các mũi tên).
LLQ : DiverticulitisLLQ: viêm túi thừa
If the pain is located in the LLQ your main concern is sigmoid diverticulitis.
In diverticulitis sonography and CT show diverticulosis with segmental colonic wall thickening and inflammatory changes in the
fat surrounding a diverticulum.Nếu đau ở LLQ, mối quan tâm chính của bạn là sigma viêm túi thừa.
Trên siêu âm và CT viêm túi thừa cho thấy túi thừa với dày thành đại tràng phân đoạn và thay đổi viêm trong mỡ xung quanh túi thừa.
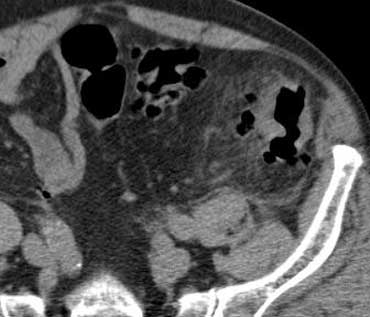 Uncomplicated sigmoid diverticulitis. Fat stranding and focal thickening of the colonic wall in an area with diverticula. No abscess formation.Không có biến chứng viêm túi thừa, thâm nhiễm mỡ và dày thành đại tràng khu trú ở vùng có túi thừa, không có áp xe.
Complications of diverticulitis such as abscess formation or perforation, can best be excluded with CT.
Các biến chứng của viêm túi thừa như hình thành áp xe hoặc thủng, tốt nhất có thể được loại trừ bằng CT.
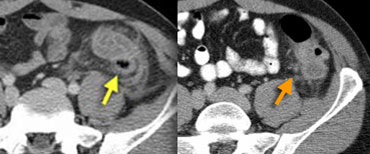 LEFT: Sigmoid diverticulitis. Diverticulum (arrow) is surrounded by hyperattenuating fat. The sigmoid wall is thickened. RIGHT: Sigmoid carcinoma with limited fat stranding.Bên trái: Sigmoid viêm túi thừa. Diverticulum (mũi tên) được bao quanh bởi tăng tỷ trọng FAT. Tường sigmoid được dày lên. Phải: Ung thư biểu mô Sigmoid với thâm nhiễm mỡ hạn chế.
An important pitfall is colon cancer, which may present with similar imaging features, especially when the colon cancer is surrounded by fat stranding due to invasive groth, desmoplastic reaction or inflammation.
Frequently it is not possible to reliably distinguish diverticulitis from colon cancer and therefore we routinely include colon cancer in the differential diagnosis of sigmoid diverticulitis. Một cạm bẫy quan trọng là ung thư đại tràng, có thể có các đặc điểm hình ảnh tương tự, đặc biệt là khi ung thư đại trực tràng được bao quanh bởi thâm nhiễm mỡ do xâm lấn, phản ứng khử mỡ hoặc viêm.
Thường không thể phân biệt được viêm túi thừa với ung thư đại tràng và do đó chúng tôi thường đưa ung thư đại trực tràng vào chẩn đoán phân biệt của viêm túi thừa.

RUQ : CholecystitisRUQ: viêm túi mật
Cholecystitis occurs when a calculus obstructs the cystic duct. The trapped bile causes inflammation of the gallbladder wall.
As gallstones are often occult on CT, sonography is the preferred imaging method for the evaluation of cholecystitis, also allowing assesment of the compressiblity of the gallbladder.
The diagnosis of a hydropic galbladder is solely made on the non-compressability of the galbladder. Do not rely on measurements. Some galbladders happen to be small and others are large. Viêm túi mật xảy ra khi sỏi làm tắc nghẽn ống túi mật Mật bị mắc kẹt gây viêm thành túi mật.
Vì sỏi mật thường ẩn trên CT, siêu âm là phương pháp hình ảnh được ưu tiên để đánh giá viêm túi mật, cũng cho phép đánh giá độ chèn ép của túi mật.
Chẩn đoán túi mật thủy tinh chỉ dựa vào tính không nén của túi mật, không dựa vào số đo, một số túi mật nhỏ và một số khác lớn.
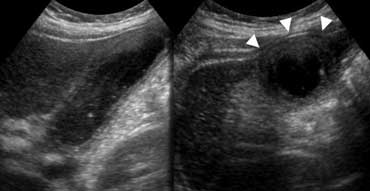 Longitudinal and transverse US show thickened gallbladder wall. The gallbladder is noncompressible ('hydropic') and causes an impression in the anterior abdominal wall (arrowheads).Siêu âm dọc và ngang cho thấy thành túi mật dày lên, túi mật không thể nén được ('nhiệt') và gây ấn tượng ở thành bụng trước (các đầu mũi tên).
The imaging appearance of cholecystis consists of an enlarged hydropic (meaning non-compressible) gallbladder with a thickened wall in the region of maximum tenderness (the so-called 'Murphy sign')Hình ảnh của cholecystis bao gồm một túi mật to (có nghĩa là không nén được) với một thành dày ở vùng đau tối đa (cái gọi là 'dấu hiệu Murphy')
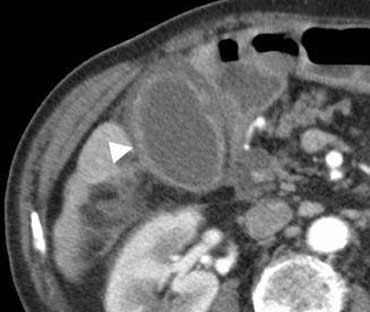 Cholecystitis at CT. The gallbladder is enlarged with edematous thickening of its wall (arrowhead), and some regional fat-stranding can be found.Viêm túi mật trên CT. Túi mật to ra kèm theo phù nề dày thành túi mật (đầu mũi tên), và có thể tìm thấy một số thâm nhiễm mỡ khu vực.
The inflamed gallbladder usually contains stones or sludge, whereas the obstructing calculus itself may or may not be identified because it is located deep within the galbladder neck or cystic duct.
The gallbladder may be surrounded by inflamed fat, but on sonography this frequently is not seen, while CT sometimes does show fat-stranding.
Potential pitfalls are pancreatitis, hepatitis or right-sided heart failure, which all may lead to thickening of the gallbladder wall without cholecystitis.
Therefore be certain that hydropic obstruction of the gallbladder is present before assigning the diagnosis of cholecystitis.
Túi mật bị viêm thường chứa sỏi hoặc bùn, trong khi sỏi gây tắc nghẽn có thể hoặc không thể được xác định vì nó nằm sâu trong cổ túi mật hoặc ống dẫn nang.
Túi mật có thể được bao quanh bởi mỡ bị viêm, nhưng trên siêu âm thường không thấy điều này, trong khi CT đôi khi cho thấy thâm nhiễm mỡ.
Những cạm bẫy tiềm ẩn là viêm tụy, viêm gan hoặc suy tim bên phải, tất cả đều có thể dẫn đến dày thành túi mật mà không có viêm túi mật.
Do đó, cần chắc chắn rằng có tắc nghẽn túi mật trước khi chỉ định chẩn đoán viêm túi mật.
Pain in LUQ
An acute abdomen with LUQ pain is rare.
Its most common cause is gastric pathology in which radiological imaging plays a minor role.
Đau ở LUQ
Bụng cấp tính kèm đau LUQ hiếm gặp.
Nguyên nhân phổ biến nhất là bệnh lý dạ dày, trong đó hình ảnh X quang đóng một vai trò nhỏ.
Screen for general signs of pathologySàng lọc các dấu hiệu chung của bệnh lý

After excluding these frequent disorders, search for signs of any other pathology, by systematically screening the whole abdomen.
Look for inflamed fat, bowel wall thickening, ileus, ascites and free air.Sau khi loại trừ các rối loạn thường xuyên này, hãy tìm kiếm các dấu hiệu của bất kỳ bệnh lý nào khác, bằng cách sàng lọc một cách có hệ thống toàn bộ vùng bụng.
Tìm mỡ bị viêm, dày thành ruột, hồi tràng, cổ trướng và hơi tự do.
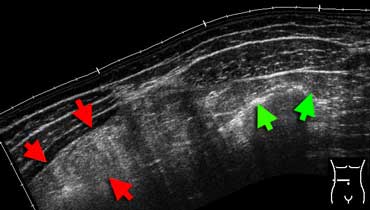 Inflamed fat at sonography. Extended-view of the ventral abdomen depicting an area of hyperechoic noncompressible inflamed fat in the omentum (red arrows). Compare this to the echogenicity of normal abdominal or subcutaneous fat (green arrows). This patient had an omental infarction.Mỡ viêm trên siêu âm. Ảnh toàn cảnh vùng bụng trước cho thấy một vùng mỡ mạc nối tăng âm, không xẹp khi ấn (mũi tên đỏ). So sánh với độ hồi âm của mỡ bụng hoặc mỡ dưới da bình thường (mũi tên xanh). Bệnh nhân này bị nhồi máu mạc nối.
Inflamed fatMỡ viêm
Inflamed fat is hyperechoic, space occupying and noncompressible at sonography.Mỡ viêm là tăng âm, chiếm không gian và không nén được trên siêu âm.
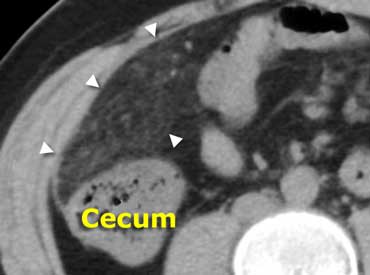
 Same patient as above. Unenhanced CT depicts an area of fatty tissue with slightly increased density (arrowheads), in the right-upper quadrant. Compare this to normal low-density subcutaneous fat. Diagnosis: omental infarction.Cùng một bệnh nhân như trên. CT không tiêm thuốc cản quang mô tả một vùng mô mỡ có mật độ tăng nhẹ (các đầu mũi tên), ở góc phần tư phía trên bên phải, so sánh với mô mỡ dưới da có mật độ thấp bình thường. Chẩn đoán: nhồi máu mạc nối.
Inflamed fat is shown as fat-stranding at CT. Inflamed fat usefully points out where and what the problem is.
As a rule, the organ or structure in the centre or nearest to the inflamed fat is the cause of the inflammation.Mỡ viêm được hiển thị dưới dạng thâm nhiễm mỡ trên CT. Mỡ viêm hữu ích chỉ ra nơi nào và vấn đề là gì.
Theo quy định, cơ quan hoặc cấu trúc ở trung tâm hoặc gần nhất với mỡ bị viêm là nguyên nhân gây viêm.
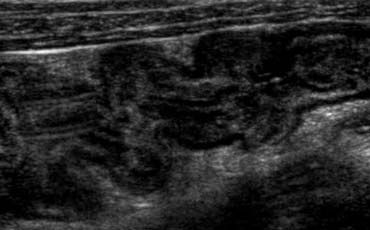 Diffuse thickening of bowel wall in a patient with colitis.Dày lan toả thành ruột ở bệnh nhân viêm đại tràng.
Bowel wall thickeningDày thành ruột
Thickening of bowel wall indicates inflammation or tumor, and has an extensive differential diagnosis.
Thickening of small bowel loops usually indicates regional inflammation, as small bowel tumors (carcinoid, lymphoma, GIST) are relatively infrequent.
In patients with local colonic wall thickening a carcinoma is a prime concern.Dày thành ruột cho thấy tình trạng viêm hoặc khối u, và có chẩn đoán phân biệt lan rộng.
Dày các quai ruột non thường cho thấy tình trạng viêm khu vực, vì các khối u ruột non (u carcinoid, u lympho, GIST) tương đối ít gặp.
Ở những bệnh nhân có dày thành đại tràng tại chỗ, ung thư biểu mô là mối quan tâm hàng đầu.
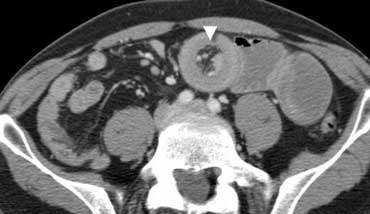 Obstructive ileus. CT depicts distended small bowel loops, but part of the small bowel and the whole colon is nondistended. Therefore this must be an obstructive small bowel ileus, and in this case its cause can easily be identified: intussusception (arrowhead).Tắc ruột do tắc ruột. CT cho thấy các quai ruột non giãn rộng, nhưng một phần ruột non và toàn bộ đại tràng là không giãn, do đó đây phải là tắc ruột do ruột non, và trong trường hợp này có thể dễ dàng xác định nguyên nhân: lồng ruột (đầu mũi tên).
IleusE-shop
Pathologic distention of bowel loops may be caused by obstruction or paralysis.
Firstly determine which parts of the gut are affected: small bowel, large bowel, or both.
Look for normal nondistended bowel loops, which, if present, strongly suggest an obstructive cause for the ileus. Chướng bụng do bệnh lý của các quai ruột có thể do tắc nghẽn hoặc liệt.
Đầu tiên xác định những phần nào của ruột bị ảnh hưởng: ruột non, ruột già, hoặc cả hai.
Tìm không giãn các quai ruột bình thường, nếu có, gợi ý mạnh mẽ nguyên nhân tắc nghẽn của tắc ruột.
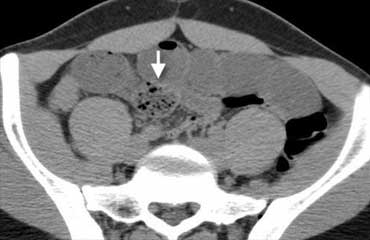
Small bowel obstruction (SBO) accounts for approximately 4% of all patients presenting with an acute abdomen.
The diagnosis of SBO is made when you see dilated small bowel and collapsed small bowel loops.
If obstruction is present, try to identify its cause and location (adhesion, tumor, volvulus, intussusception, inguinal hernia).
Adhesions account for 60-80% of all cases and are the likely cause when a smooth transition from dilated to collapsed small-bowel loops is noted.
Tắc ruột non (SBO) chiếm khoảng 4% tổng số bệnh nhân có biểu hiện bụng cấp.
Chẩn đoán SBO được thực hiện khi bạn thấy ruột non giãn và các quai ruột non xẹp.
Nếu có tắc nghẽn, hãy cố gắng xác định nguyên nhân và vị trí của nó (liên kết, khối u, xoắn, lồng ruột, thóat vị bẹn).
Dính chiếm 60-80% các trường hợp và là nguyên nhân có thể xảy ra khi ghi nhận sự chuyển tiếp từ giãn sang thu gọn các quai ruột nhỏ.
The 'Small Bowel Feces Sign' (SBFS) is a very useful sign as it is seen at the zone of transition thus facilitating identification of the cause of the obstruction.
The SBFS has been defined as gas and particulate material within a dilated small-bowel loop that simulates the appearance of feces.
Scroll through the images on the left to see the small bowel feces sign indicating the site of obstruction.Dấu hiệu ruột non Feces (SBFS) là một dấu hiệu rất hữu ích vì nó được nhìn thấy ở vùng chuyển tiếp, do đó tạo điều kiện thuận lợi cho việc xác định nguyên nhân gây tắc nghẽn.
SBFS đã được định nghĩa là vật liệu dạng khí và dạng hạt trong một quai ruột non giãn mô phỏng sự xuất hiện của phân.
Cuộn qua các hình ảnh bên trái để xem dấu hiệu phân ruột non cho thấy vị trí tắc nghẽn.
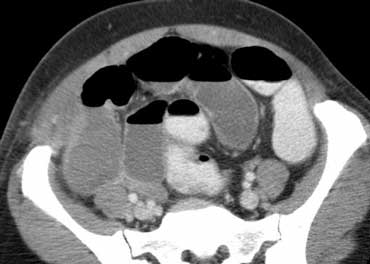
Alternatively, an ileus without any normal bowel loops strongly suggests a paralytic cause.
This is usually a response to general peritonitis, wich may have many possible causes of the inflammation.Ngoài ra, tắc ruột không có bất kỳ các quai ruột bình thường nào gợi ý mạnh mẽ nguyên nhân gây liệt.
Đây thường là một phản ứng với viêm phúc mạc nói chung, có thể có nhiều nguyên nhân có thể gây viêm.
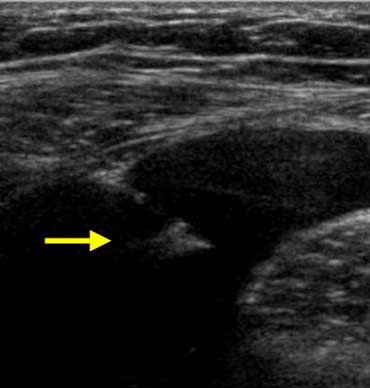 Clinically appendicitis. US only showed a little bit of ascites. A diagnostic puncture (arrow marks needletip) revealed blood. In a woman this finding is very suspicious of an EUG.Trên lâm sàng viêm ruột thừa. siêu âm chỉ thấy một chút cổ trướng. Một dấu hiệu chẩn đoán (mũi tên đánh dấu đầu kim) cho thấy máu. Ở một phụ nữ, phát hiện này rất đáng ngờ về một EUG.
AscitesCổ trướng
Asymptomatic volunteers do not have a detectable amount of free intraperitoneal fluid, with the exception of an incidental drop of fluid in Douglas in fertile women.
The presence of ascites is a nonspecific sign of abdominal pathology, indicating that 'something is wrong'.
You may want to perform a US-guided diagnostic puncture of the ascites, in order to investigate whether it is sterile reactive fluid, pus, blood, urine, or bile.Những người tình nguyện không có triệu chứng không có lượng dịch tự do trong phúc mạc có thể phát hiện được, ngoại trừ một giọt dịch tình cờ trong Douglas ở phụ nữ có khả năng sinh sản.
Sự hiện diện của cổ trướng là một dấu hiệu không đặc hiệu của bệnh lý ổ bụng, cho thấy rằng có gì đó không ổn.
Bạn có thể muốn thực hiện chọc dò chẩn đoán cổ trướng dưới hướng dẫn siêu âm, để kiểm tra xem đó là dịch phản ứng vô trùng, mủ, máu, nước tiểu hay mật.
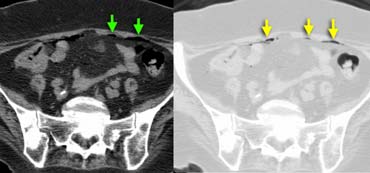 Intraperitoneal air in a patient suspected of having appendicitis. Air better seen on images with lungsetting on the right.Không khí trong phúc mạc ở bệnh nhân nghi ngờ có viêm ruột thừa Không khí nhìn thấy rõ hơn trên hình ảnh với phổi ở bên phải.
Free airHơi tự do
The presence of free intraperitoneal air is proof of bowel perforation, and indicates a surgical emergency.
A pneumoperitoneum has only two frequent causes:Sự hiện diện của khí tự do trong phúc mạc là bằng chứng của thủng ruột, và cho thấy một trường hợp cấp cứu phẫu thuật.
Tràn khí ổ bụng chỉ có hai nguyên nhân thường gặp:
- Perforation of a gastric ulcer
- Perforation of colonic diverticulitis - Thủng ổ loét dạ dày
- Thủng đại tràng viêm túi thừa
Free air is usually not seen in perforated appendicitis).
Always examine the images in lungsetting for better detection of free intraabdominal air (figure).Hơi tự do thường không thấy trong viêm ruột thừa bị thủng).
Luôn kiểm tra các hình ảnh trong phổi để phát hiện tốt hơn khí tự do trong ổ bụng (hình).
Differential diagnosisChẩn đoán phân biệt
A complete list of all possible causes of an acute abdomen is of little use in daily practice, therefore we just provide some imaging examples of several frequent causes of acute abdominal pain Một danh sách đầy đủ tất cả các nguyên nhân có thể gây ra đau bụng cấp tính ít được sử dụng trong thực hành hàng ngày, do đó chúng tôi chỉ cung cấp một số ví dụ về hình ảnh về một số nguyên nhân thường gặp gây đau bụng cấp.
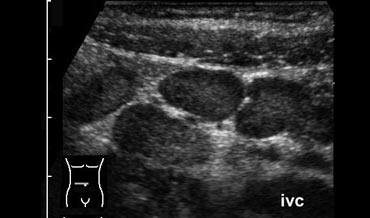 US shows enlarged mesenteric lymph nodes in the right lower quadrant, with no other abnormalitiesSiêu âm cho thấy hạch mạc treo mở rộng trong vùng bụng dưới phải, không có bất thường nào khác
Mesenteric lymphadenitis.Viêm hạch mạc treo.
Mesenteric lymphadenitis is a common mimicker of appendicitis.
It is the second most common cause of right lower quadrant pain after appendicitis.
It is defined as a benign self-limiting inflammation of right-sided mesenteric lymph nodes without an identifiable underlying inflammatory process, occurring more often in children than in adults..
This diagnosis can only be made confidently when a normal appendix is found, because adenopathy also frequently occurs with appendicitis.
Key finding: Lymphadenopathy with a normal appendix and normal mesenteric fat.
Viêm hạch mạc treo là một biểu hiện phổ biến của viêm ruột thừa.
Đây là nguyên nhân phổ biến thứ hai gây đau vùng bụng dưới phải sau viêm ruột thừa.
Nó được định nghĩa là tình trạng viêm tự giới hạn lành tính của hạch mạc treo bên phải mà không có quá trình viêm cơ bản có thể xác định được, xảy ra thường xuyên hơn ở trẻ em so với người lớn.
Chẩn đoán này chỉ có thể được thực hiện một cách tự tin khi tìm thấy ruột thừa bình thường, bởi vì hạch cũng thường xuyên xảy ra với viêm ruột thừa.
Kết quả: bệnh hạch có ruột thừa bình thường và mỡ mạc treo bình thường.
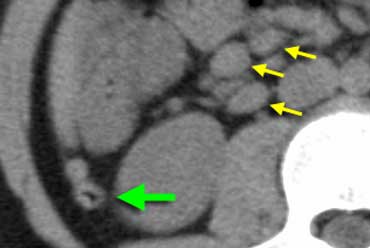 Normal appendix (green arrow) and enlarged mesenteric lymphnodes (yellow arrows).Ruột thừa bình thường (mũi tên màu xanh lá cây) và các hạch bạch huyết mạc treo to (mũa tên màu vàng).
On the left a CT of mesenteric lymphadenitis in a child suspected of appendicitis.Bên trái là hình ảnh chụp cắt lớp vi tính viêm hạch mạc treo ở một đứa trẻ nghi ngờ viêm ruột thừa.
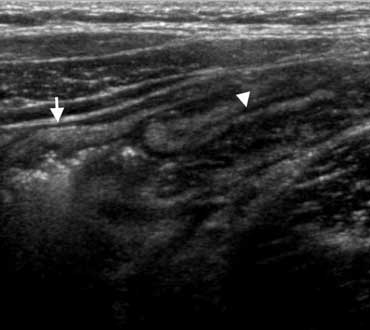 US typically shows submucosal wall thickening (arrowheads) of the terminal ileum and cecum without inflammation of the surrounding fat.Siêu âm thường cho thấy dày thành dưới niêm mạc (các đầu mũi tên) của đoạn cuối hồi tràng và manh tràng mà không có viêm mỡ xung quanh.
Bacterial ileocecitisViêm hồi–manh tràng do vi khuẩn
Infectious enterocolitis may cause mild symptoms resembling a common viral gastroenteritis, but it may also clinically present with features indistinguishable from appendicitis especially in bacterial ileocecitis, caused by Yersinia, Campylobacter, or Salmonella.
Key finding: ileocecal wall thickening without inflamed fat, adenopathy, normal appendixViêm ruột truyền nhiễm có thể gây ra các triệu chứng nhẹ giống như viêm dạ dày ruột do vi rút thông thường, nhưng nó cũng có thể biểu hiện lâm sàng với các đặc điểm không thể phân biệt được với viêm ruột thừa đặc biệt là viêm hồi–manh tràng do vi khuẩn, gây ra bởi Yersinia, Campylobacter, hoặc Salmonella.
Dấu hiệu chính: thành hồi tràng dày không có mỡ viêm, hạch to, ruột thừa bình thường
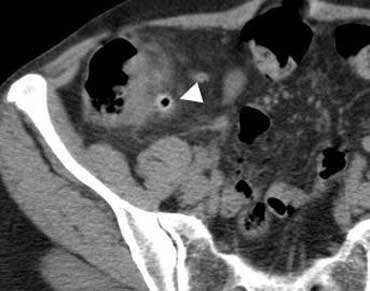 CT shows an inflamed cecal diverticulum (arrowhead) with regional colonic wall thickening.CT cho thấy một túi thừa manh tràng (đầu mũi tên) bị viêm với dày thành đại tràng khu vực.
Right-sided diverticulitisViêm túi thừa bên phải
Right-sided colonic diverticulitis may clinically mimic appendicitis or cholecystitis, though the patient's history is generally more protracted.
In contrast to sigmoid diverticula, right-sided colonic diverticula are usually true diverticula, that is, outpouchings of the colonic wall containing all layers of the wall.
This may possibly explain the essentially benign self- limiting character of right-sided diverticulitis.Viêm túi thừa đại tràng phải có thể giống với viêm ruột thừa hoặc viêm túi mật, mặc dù tiền sử của bệnh nhân thường kéo dài hơn.
Trái ngược với túi thừa đại tràng sigma, túi thừa đại trực tràng bên phải thường là túi thừa thực sự, nghĩa là các túi thừa của thành đại tràng chứa tất cả các lớp của thành.
Điều này có thể giải thích đặc tính tự giới hạn lành tính của viêm túi thừa bên phải.
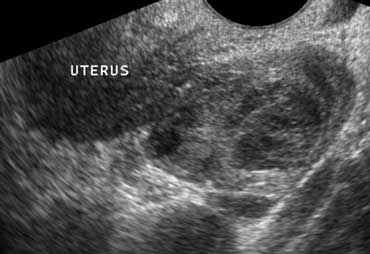
 Enlarged adnex due to salpingitisViêm vòi tử cung do viêm phần phụ
Pelvic inflammatory diseaseBệnh viêm vùng chậu
Pelvic inflammatory disease is a common mimicker of both of appendicitis and diverticulitis.
Transvaginal sonography depicts an inhomogeneous enlarged inflamed ovary.Bệnh viêm vùng chậu là một biểu hiện phổ biến của cả viêm ruột thừa và viêm túi thừa.
Siêu âm qua âm đạo mô tả một buồng trứng bị viêm to không đồng nhất.
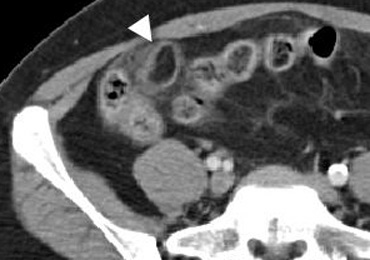 CT characteristic of epiploic appendagitis with a right-sided fatty mass surrounded by a hyperattenuating ring.Đặc điểm cắt lớp vi tính của viêm bờm mỡ đại tràng với khối mỡ bên phải được bao quanh bởi viền tăng tỷ trọng.
Epiploic appendagitis.Viêm phần phụ mỡ đại tràng.
Epiploic appendages are small adipose protrusions from the serosal surface of the colon.
An epiploic appendage may undergo torsion and secondary inflammation causing focal abdominal pain that simulates appendicitis when located in the right lower quadrant or diverticulitis when located in the left lower quadrant.
The characteristic ring-sign corresponds to inflamed visceral peritoneal lining surrounding an infarcted fatty epiploic appendage.
Các bờm mỡ đại tràng là các phần nhô ra của mỡ từ bề mặt thanh mạc của đại tràng.
bờm mỡ đại tràng có thể bị xoắn và viêm thứ phát gây đau bụng khu trú giống viêm ruột thừa khi nằm trong vùng bụng dưới phải hoặc viêm túi thừa khi nằm ở vùng bụng dưới trái.
Dấu hiệu vòng đặc trưng tương ứng với niêm mạc phúc mạc nội tạng bị viêm xung quanh một bờm mỡ đại tràng bị nhồi máu.
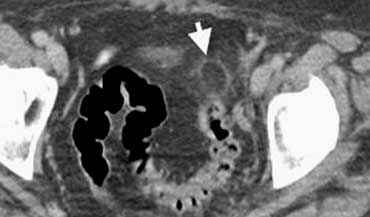 Left sided epiploic appendagitis in patient clinically suspected of having a diverticulitis.Characteristic hyperattenuating ring sign.Viêm bờm mỡ đại tràng bên trái ở bệnh nhân nghi viêm túi thừa trên lâm sàng. Lưu ý dấu hiệu viền tăng tỷ trọng đặc trưng.
Epiploic appendagitis has been reported in approximately 1% of patients clinically suspected of having appendicitis.
It is very important to make a positive diagnosis of this characteristic entity since epiploic appendagitis is a self-limiting disease.
Both US and CT will depict an inflamed fatty mass adjacent to the colon.Viêm bờm mỡ đại tràng đã được báo cáo ở khoảng 1% bệnh nhân nghi ngờ lâm sàng có viêm ruột thừa.
Việc chẩn đoán xác định thực thể đặc trưng này là rất quan trọng vì viêm bờm mỡ đại tràng là một bệnh tự khỏi.
Cả siêu âm và CT đều cho thấy một khối mỡ bị viêm nằm cạnh đại tràng.
Key finding: inflamed fatty mass adjacent to the colon with characteristic ring sign.Một số đặc điểm chính: khối mỡ viêm liền kề đại tràng có dấu hiệu hình vòng đặc trưng.
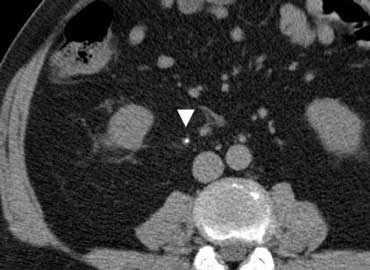 Small stone in right ureter (arrow) causing right flank pain.Sỏi niệu quản phải (mũi tên) có kích thước nhỏ gây đau hông lưng phải.
UrolithiasisSỏi đường tiết niệu
Urolithiasis often causes flank pain, but an ureteral stone (arrowhead) may occasionally present with clinical signs simulating appendicitis, cholecystitis or diverticulitis.
Appendicitis on the other hand may cause hematuria, pyuria and albuminuria in up to 25% of patients because of ureteral inflammation from an adjacent inflamed appendix.
Sỏi niệu thường gây đau hông lưng, nhưng sỏi nòng (đầu mũi tên) đôi khi có thể có các dấu hiệu lâm sàng mô phỏng viêm ruột thừa, viêm túi mật hoặc viêm túi thừa.
Mặt khác, viêm ruột thừa có thể gây tiểu máu, đái mủ và albumin niệu ở 25% bệnh nhân do viêm niệu quản từ một ruột thừa bị viêm liền kề.
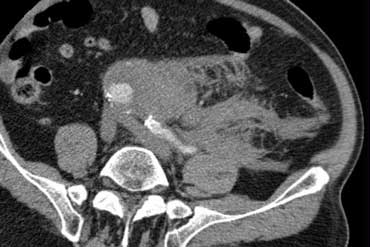 Left retroperitoneal fluid collection due to ruptured aneurysm.Chảy dịch sau phúc mạc trái do vỡ phình động mạch.
Ruptured AneurysmPhình động mạch
Most abdominal aortic aneurysms rupture into the left retroperitoneum (4).
Clinically this may simulate sigmoid diverticulitis or renal colic due to impingement of the hematoma on adjacent structures.
However most patient will present with the classic triad of hypotension, a pulsating mass and
back pain.
Continuous leakage will lead to rupture into the peritoneal cavity and eventually death.
Sonography is a quick and convenient modality, but it is much less sensitive and specific for the diagnosis of aneurysmal rupture than CT.
The absence of sonographic evidence of rupture does not rule out this entity if clinical suspicion is high.
Hầu hết các phình động mạch chủ bụng vỡ vào sau phúc mạc trái (4).
Trên lâm sàng, điều này có thể giống với đại tràng sigma viêm túi thừa hoặc đau quặn thận do sự tác động của khối máu tụ lên các cấu trúc lân cận.
Tuy nhiên, hầu hết bệnh nhân sẽ có bộ ba điển hình là tụt huyết áp, khối u đập và đau lưng.
Rò liên tục sẽ dẫn đến vỡ vào khoang phúc mạc và cuối cùng là tử vong.
Siêu âm là một phương pháp nhanh chóng và thuận tiện, nhưng nó ít nhạy và đặc hiệu hơn trong chẩn đoán vỡ túi phình so với CT.
Không có bằng chứng siêu âm về vỡ không loại trừ thực thể này nếu nghi ngờ lâm sàng cao.
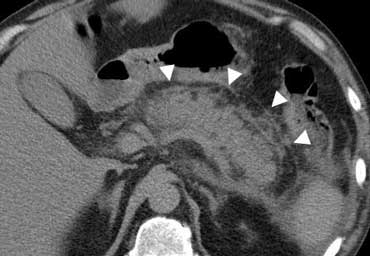 Pancreas surrounded by fat stranding due to exsudative pancreatitis.Tuỵ được bao quanh bởi thâm nhiễm mỡ do viêm tụy đột ngột.
PancreatitisViêm tụy
CT depicts fat-stranding (arrowheads) surrounding the primary focus of the inflammation: the pancreas. CT mô tả thâm nhiễm mỡ (các đầu mũi tên) xung quanh vị trí tập trung chính của viêm: tuyến tụy.
Conclusion
In patients with an acute abdomen 'the stakes are high'.
A misdiagnosis may have serious consequences. We advocate a systematic approach:
1. First focus on the most common diseases and make a firm diagnosis or exclude them.
2. Always screen the whole abdomen for general signs of pathology. Kết luận
Ở những bệnh nhân bị bụng cấp tính, nguy cơ cao.
Chẩn đoán sai có thể gây hậu quả nghiêm trọng. Chúng tôi ủng hộ một cách tiếp cận có hệ thống:
1. Đầu tiên tập trung vào các bệnh phổ biến nhất và chẩn đoán chắc chắn hoặc loại trừ chúng.
2. Luôn sàng lọc toàn bộ vùng bụng để tìm các dấu hiệu chung của bệnh lý.
ReferencesTài liệu tham khảo
-
A prospective study of ultrasonography in the diagnosis of appendicitis
Nghiên cứu tiền cứu siêu âm trong chẩn đoán viêm ruột thừa
JB Puylaert et al; NEJM Volume 317:666-669 JB Puylaert và cộng sự; NEJM Tập 317: 666-669
-
Signs in Imaging, The Hyperattenuating Ring Sign
Dấu hiệu trong hình ảnh, dấu hiệu viền tăng tỷ trọng
Adriaan C. van Breda Vriesman et al ; Radiology 2003;226:556-557 Adriaan C. van Breda Vriesman và cộng sự ; X quang 2003;226:556-557
-
Frequency and Relevance of the 'Small-Bowel Feces' Sign on CT in Patients with Small-Bowel Obstruction
Tần suất và sự liên quan của dấu hiệu 'phân ruột non' trên CT ở bệnh nhân có Small-tắc ruột
Dawn E. Lazarus et al, AJR 2004; 183:1361-1366 Dawn E. Lazarus và cộng sự, AJR 2004; 183:1361-1366
-
Abdominal Aortic Aneurysm, Rupture in eMedicine
Phình động mạch chủ bụng, vỡ động mạch chủ trên eMedicine
by Walter A Tan, MD, MS and Michel S Makaroun, MD Walter A. Tan, MD, MS và Michel S. Makaroun, MD