
Shoulder UltrasoundSiêu âm vai
¹Radiology department of the faculty of Medicine - Mansoura University, Egypt and ²Alrijne hospital in Leiden, the Netherlands¹ Khoa Xạ của Khoa Y - Đại học Mansoura, Ai Cập và Bệnh viện ²Alrijne ở Leiden, Hà Lan
Ngày đăng / cập nhật: 31-01-2025
Bản gốc trên radiologyassistant.nl ↗ · tải về lúc 2026-11-19 20:19 · bản dịch máy có chuẩn hóa thuật ngữ chẩn đoán hình ảnh
This article is currently in preparation. Once it is finalized, we will provide an announcement on the homepage.Bài viết này hiện đang được chuẩn bị. Sau khi hoàn thiện, chúng tôi sẽ thông báo trên trang chủ.
This article serves as an introduction to shoulder ultrasound. Ultrasound is a non-invasive, easily accessible imaging technique that allows for thorough evaluation of the shoulder, including dynamic assessment in patients with impingement.Bài viết này giới thiệu về siêu âm vai. Siêu âm là một kỹ thuật hình ảnh không xâm lấn, dễ tiếp cận, cho phép đánh giá kỹ lưỡng khớp vai, bao gồm cả đánh giá động ở bệnh nhân có chèn ép khớp.
We will review the sonographic anatomy of the shoulder, outline the examination protocol—including proper patient positioning—and discuss common pathologies encountered during shoulder ultrasound.Chúng tôi sẽ xem xét giải phẫu siêu âm của vai, phác thảo quy trình khám – bao gồm cả việc định vị bệnh nhân – và thảo luận về các bệnh lý thường gặp trong quá trình siêu âm vai.
AnatomyGiải phẫu
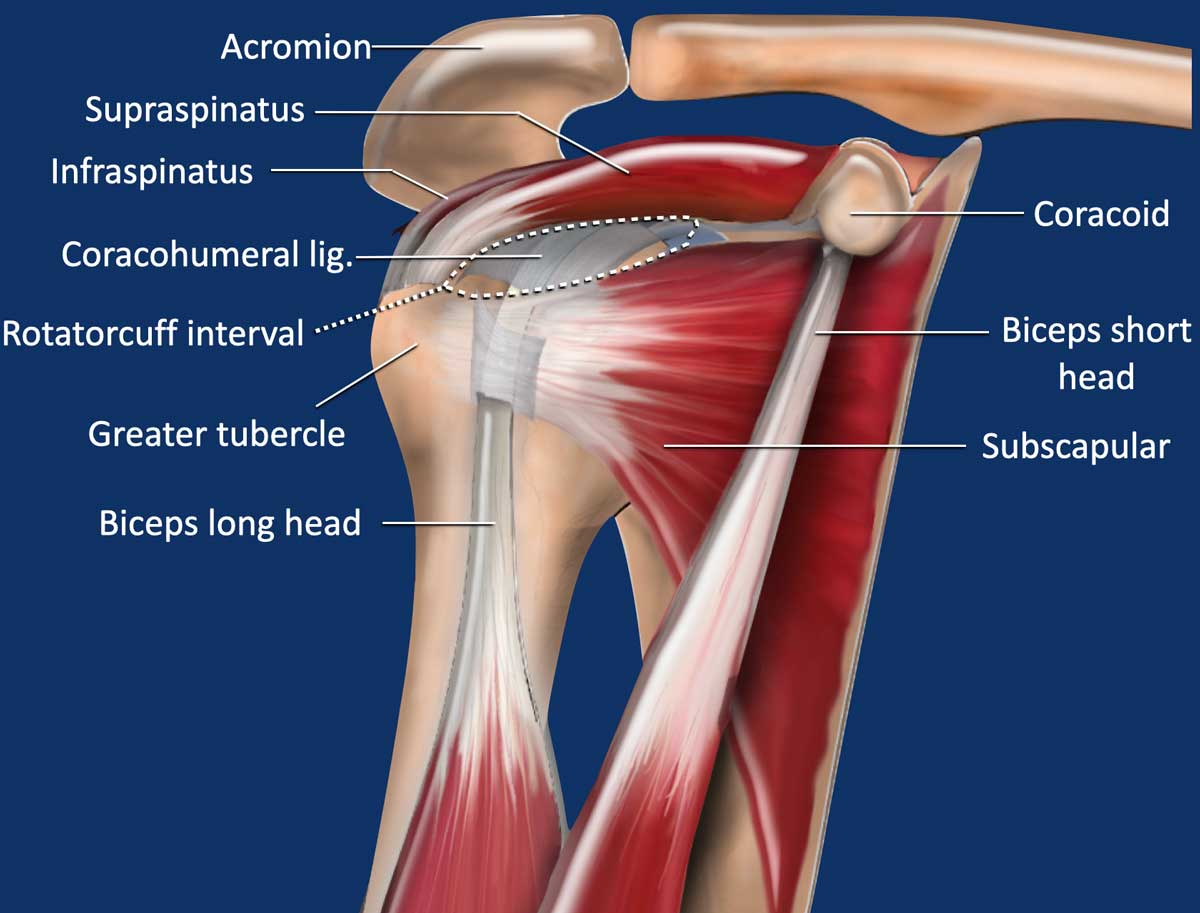

Glenohumeral Joint StabilizationỔn định khớp vai
A key stabilizer of the glenohumeral joint is the rotator cuff, which is composed of the subscapularis tendon anteriorly, the supraspinatus tendon superiorly, and the infraspinatus and teres minor tendons posteriorly.
Of these posterior tendons, only the infraspinatus tendon is partially visible in this illustration.Một bộ phận cố định quan trọng của khớp ổ chảo cánh tay là chóp xoay, bao gồm gân dưới vai trước, gân trên gai phía trên, gân dưới gai và gân cơ tròn nhỏ phía sau.
Trong số các gân sau này, chỉ có gân dưới gai là có thể nhìn thấy một phần trong hình minh hoạ này.
The normal anatomy is also discussed here.Giải phẫu bình thường cũng được thảo luận ở đây.
Rotator cuff intervalKhoảng chóp xoay
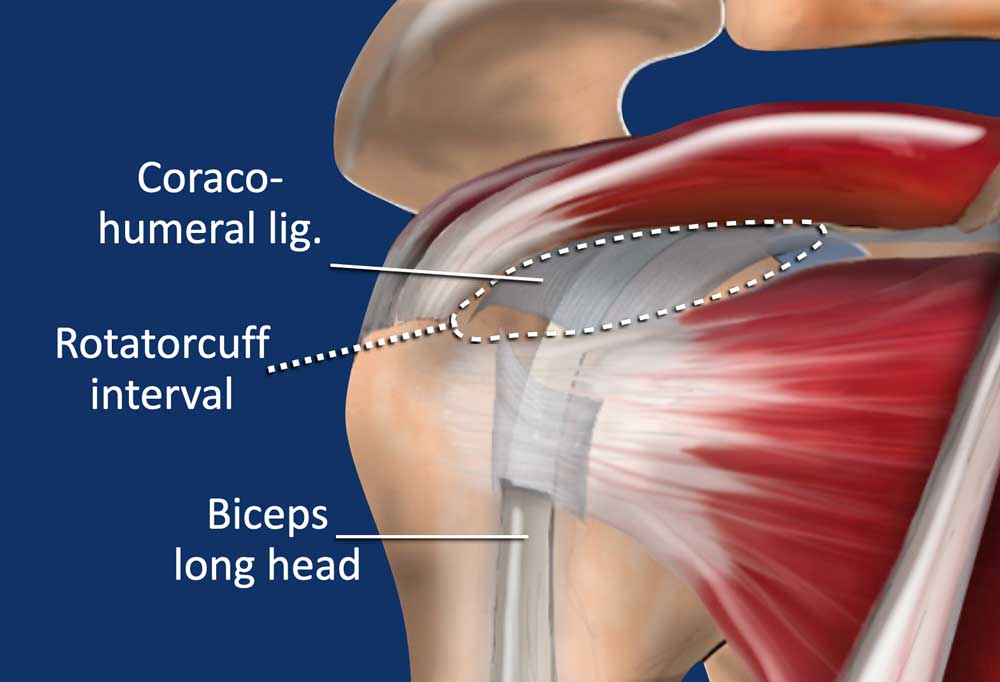
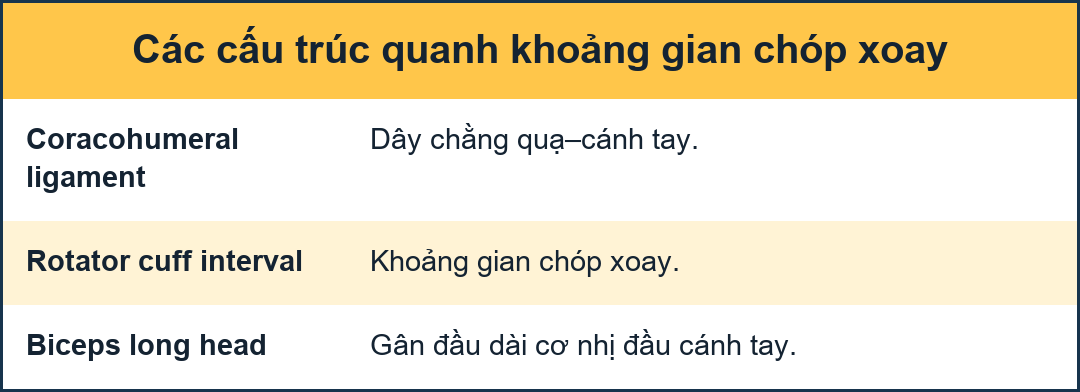
The rotator cuff interval is a distinct gap in the rotator cuff located between the superior edge of the subscapularis tendon and the anterior edge of the supraspinatus tendon.Khoảng chóp xoay là khoảng trống riêng biệt trong chóp xoay nằm giữa bờ trên của gân dưới vai và bờ trước của gân trên gai.
In this interval, the humeral head is not covered by the rotator cuff but is instead covered by the intra-articular portion of the long head of the biceps tendon, which is stabilized by the coracohumeral ligament.Trong khoảng thời gian này, đầu xương cánh tay không được chóp xoay bao phủ mà thay vào đó được bao phủ bởi phần trong khớp của đầu dài của gân cơ nhị đầu, được ổn định bởi dây chằng coracohumeral.
When assessing for supraspinatus tendon tears, it is crucial to examine its attachment to the greater tuberosity, particularly along the posterior border of the rotator cuff interval.
This anterior region of the supraspinatus tendon is a common site for partial-thickness tears, known as "rim-rent tears."Khi đánh giá đứt gân cơ trên gai, điều quan trọng là phải kiểm tra sự gắn kết của nó với lồi củ lớn hơn, đặc biệt là dọc theo bờ sau của khoảng chóp xoay.
Vùng trước của gân trên gai này là một vị trí phổ biến cho rách một phần độ dày, được gọi là "nước mắt có đường viền".
The biceps tendon is stabilized by the capsuloligamentous complex, referred to as the biceps pulley, which consists of the superior glenohumeral ligament, the coracohumeral ligament, and the distal insertion of the subscapularis tendon.Gân cơ nhị đầu cánh tay được cố định bởi phức hợp mao mạch, được gọi là ròng rọc cơ nhị đầu, bao gồm dây chằng ổ chảo cánh tay trên, dây chằng vòm cánh tay và đầu xa của gân dưới vai.
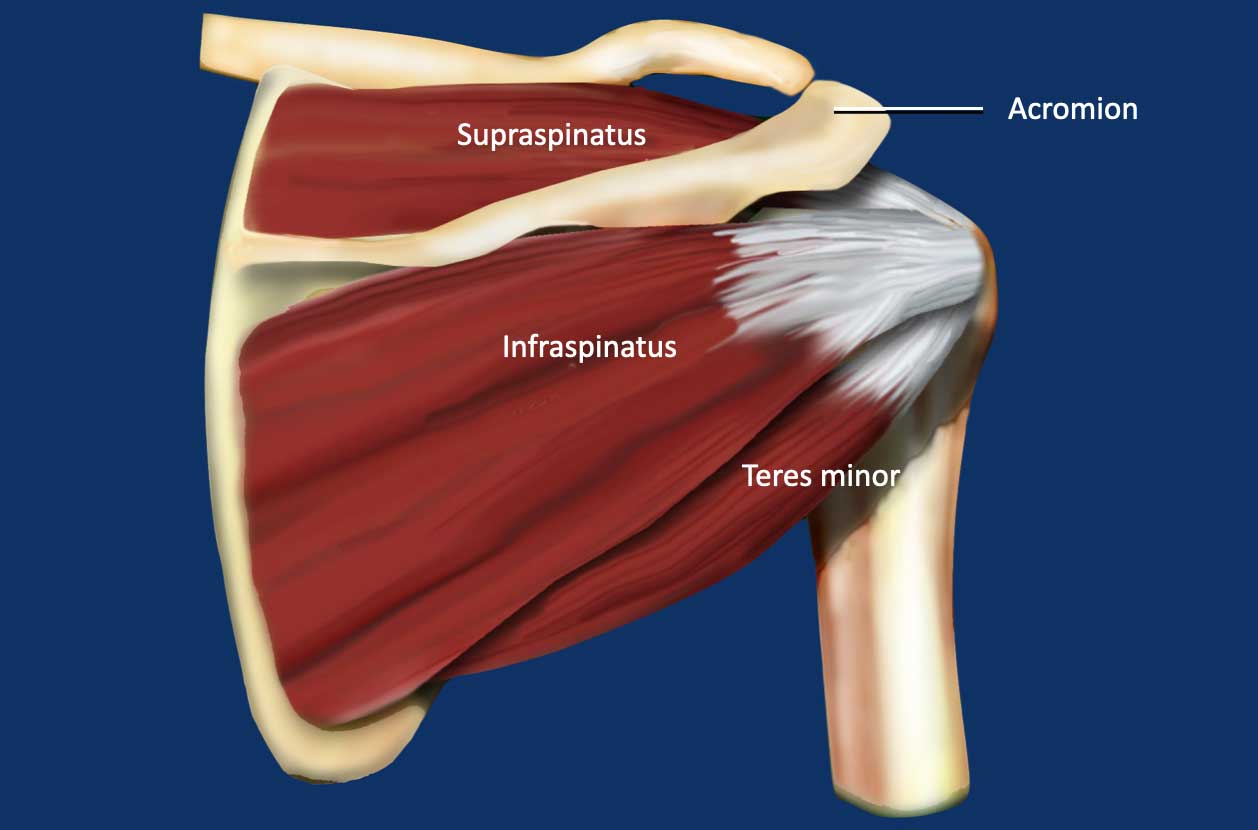

This posterior view of the shoulder highlights the supraspinatus, infraspinatus, and teres minor muscles and their associated tendons.Hình ảnh sau này của vai làm nổi bật cơ trên gai, cơ dưới gai, cơ tròn và các gân liên quan của chúng.
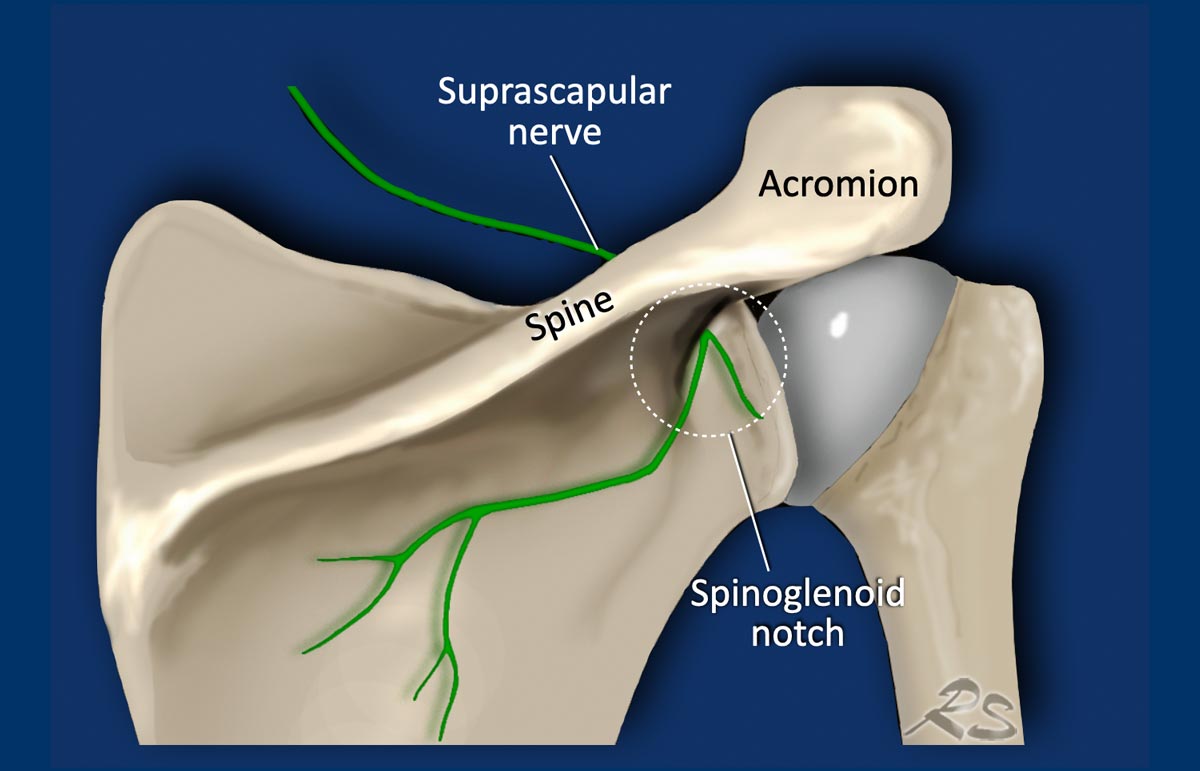

Spinoglenoid notchVết cắt gai lốm đốm
The spinoglenoid notch is the anatomical region located between the lateral base of the scapular spine and the glenoid process.
It serves as a connection between the supraspinatus and infraspinatus fossae and allows passage for the suprascapular nerve and artery.
Ganglion cysts can develop in this area, potentially compressing the suprascapular nerve and leading to shoulder pain and atrophy of the infraspinatus muscle.
These cysts are often secondary to tears in the posterosuperior glenoid labrum.Khe mỏm gai là vùng giải phẫu nằm giữa nền ngoài của gai vai và mỏm ổ chảo.
Nó đóng vai trò như một kết nối giữa cơ trên gai và cơ dưới gai và cho phép đi qua dây thần kinh và động mạch trên vai.
Nang hạch có thể phát triển ở khu vực này, có khả năng chèn ép dây thần kinh trên vai và dẫn đến đau vai và teo cơ dưới gai.
Những nang này thường là thứ phát sau khi rách ở sụn viền ổ chảo sau trên.
Standard Ultrasound ExaminationKhám siêu âm tiêu chuẩn
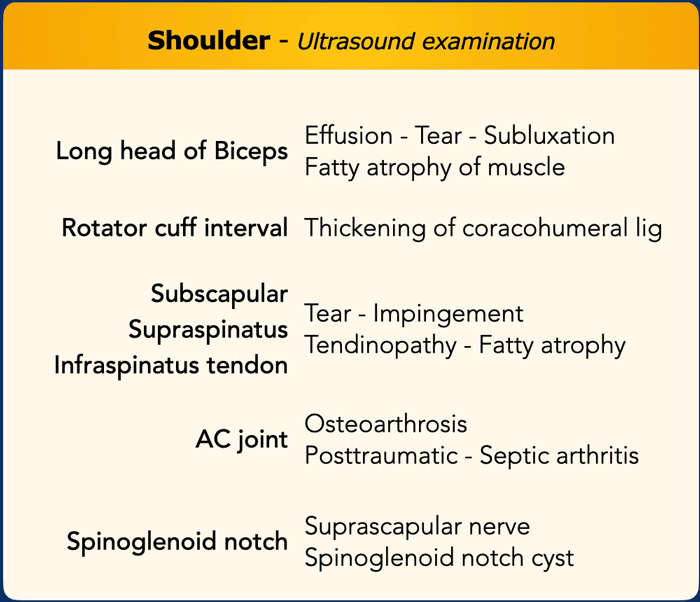
Ultrasound Examination of the Shoulder
A high-resolution linear probe (≥10 MHz) is typically used for shoulder ultrasound. Occasionally, a curvilinear probe (3.5 MHz) is employed to provide a broader view of the glenohumeral joint.Khám siêu âm khớp vai
Đầu dò tuyến tính độ phân giải cao (≥ 10 MHz) thường được sử dụng cho siêu âm vai. Đôi khi, đầu dò đường cong (3,5 MHz) được sử dụng để cung cấp cái nhìn rộng hơn về khớp ổ chảo-mũi.
The examination generally begins with the long head of the biceps (LHB) tendon, assessing for effusion, tears, or subluxation.
Fatty atrophy may also be observed, either within the muscle belly or at the myotendinous junction.
Next, the tendons of the subscapularis, supraspinatus, and infraspinatus muscles are evaluated, with particular attention to identifying tears.
The examination can be expanded to include the acromioclavicular (AC) joint, spinoglenoid notch, posterior labrum, and the glenohumeral joint.
A checklist (see Table) is recommended to ensure all structures have been thoroughly examined.Khám thường bắt đầu bằng việc khám đầu dài của gân cơ nhị đầu (LHB), đánh giá tình trạng tràn dịch, rách hoặc bán trật.
Teo mỡ cũng có thể được quan sát thấy, hoặc trong bụng cơ hoặc tại chỗ nối cơ.
Tiếp theo, đánh giá gân cơ dưới vai, cơ trên gai và cơ dưới gai, đặc biệt chú ý đến việc xác định các vết rách.
Khám có thể mở rộng để bao gồm khớp cùng vai đòn (AC), rãnh gai, xương ức sau và khớp ổ chảo cánh tay.
Một danh sách kiểm tra (xem Bảng) được khuyến cáo để đảm bảo tất cả các cấu trúc đã được kiểm tra kỹ lưỡng.
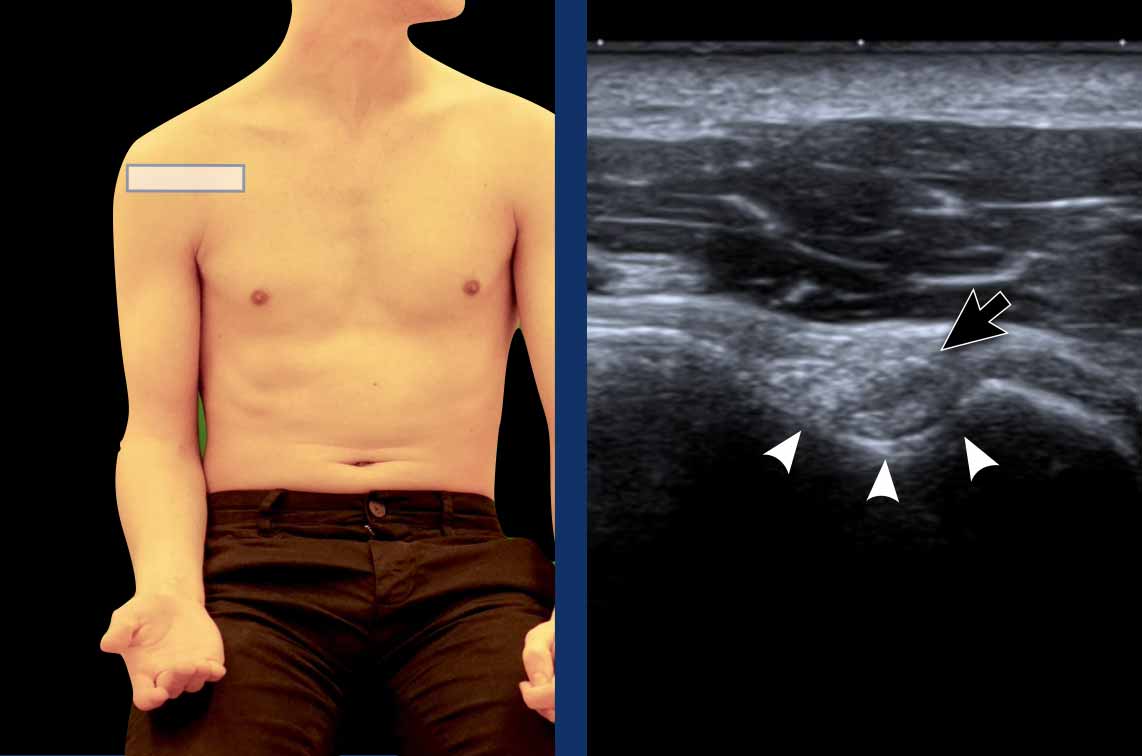
Long head of the biceps tendonĐầu dài gân cơ nhị đầu
The LHB tendon is best visualized by positioning the probe over the muscle belly of the biceps brachii in the upper arm and moving proximally to the myotendinous junction and the tendon.
The patient’s forearm should be supinated and slightly internally rotated toward the contralateral knee.Gân LHB được nhìn thấy rõ nhất bằng cách đặt đầu dò lên bụng cơ nhị đầu cánh tay ở cánh tay trên và di chuyển về phía gần đến khớp nối cơ và gân.
Cẳng tay của bệnh nhân nên được ngửa ra và hơi xoay trong về phía đầu gối đối bên.
In this position, the LHB appears as a rounded structure with a fibrillary echotexture (black arrow) situated within the intertubercular groove (white arrowheads).Ở vị trí này, LHB xuất hiện dưới dạng một cấu trúc tròn với một vải siêu âm dạng sợi (mũi tên đen) nằm trong rãnh liên củ (đầu mũi tên màu trắng).

Video of the examination of the long head of the biceps in the transverse plane.Video chụp quan sát đầu dài cơ nhị đầu trên mặt phẳng ngang.
Click in the left upper corner for a full screen view.Nhấp vào ở góc trên bên trái để xem toàn màn hình.
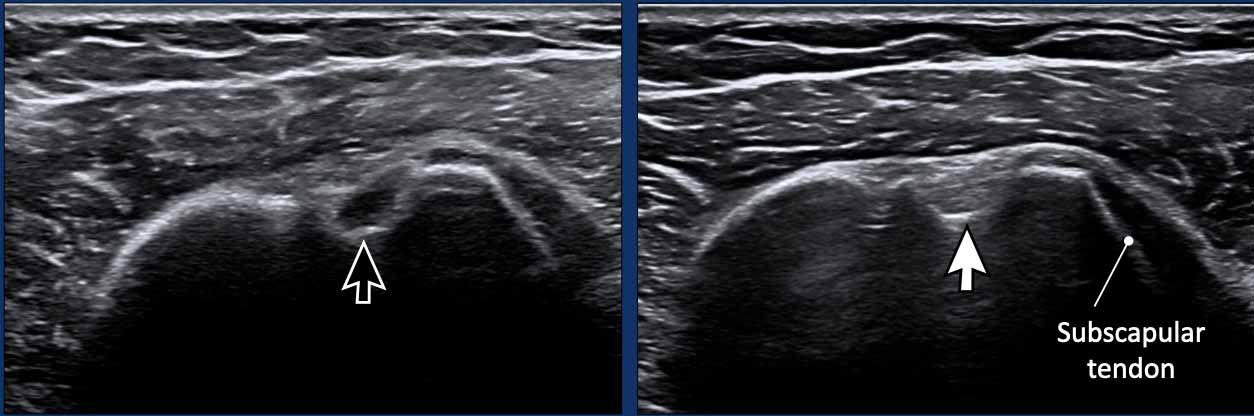
 Anisotropy of the LHBTính bất đẳng hướng của LHB
Anisotropy
Anisotropy is an artifact that occurs when the ultrasound beam is not perpendicular to the LHB tendon. This misalignment leads to reduced sound wave reflection, resulting in a loss of resolution and a darkened, hypoechoic appearance of the structure (black arrow). In some cases, this may give the impression that the LHB tendon is dislocated from the intertubercular groove.
Bất đẳng hướng
Bất đẳng hướng là hiện tượng xảy ra khi chùm tia siêu âm không vuông góc với gân LHB. Sự lệch hướng này dẫn đến giảm phản xạ sóng âm, dẫn đến mất độ phân giải và xuất hiện cấu trúc giảm âm tối màu (mũi tên đen). Trong một số trường hợp, điều này có thể gây ấn tượng rằng gân L HB bị trật khỏi rãnh liên củ.
To correct for anisotropy, reposition the transducer so that the ultrasound beam is perpendicular to the tendon. The LHB will then regain its typical echogenic, fibrillary appearance (white arrow).
It is important to note that anisotropy can also affect other structures, such as the subscapularis tendon in this image, which similarly appears anechoic due to this artifact.Để hiệu chỉnh dị hướng, đặt lại đầu dò sao cho chùm tia siêu âm vuông góc với gân, sau đó LHB sẽ lấy lại hình dạng tiếng vang, sợi điển hình (mũi tên trắng).
Điều quan trọng cần lưu ý là dị hướng cũng có thể ảnh hưởng đến các cấu trúc khác, chẳng hạn như gân dưới vai trong hình ảnh này, có hình dạng tương tự trống âm do tạo tác này.
Rotator cuff intervalKhoảng chóp xoay
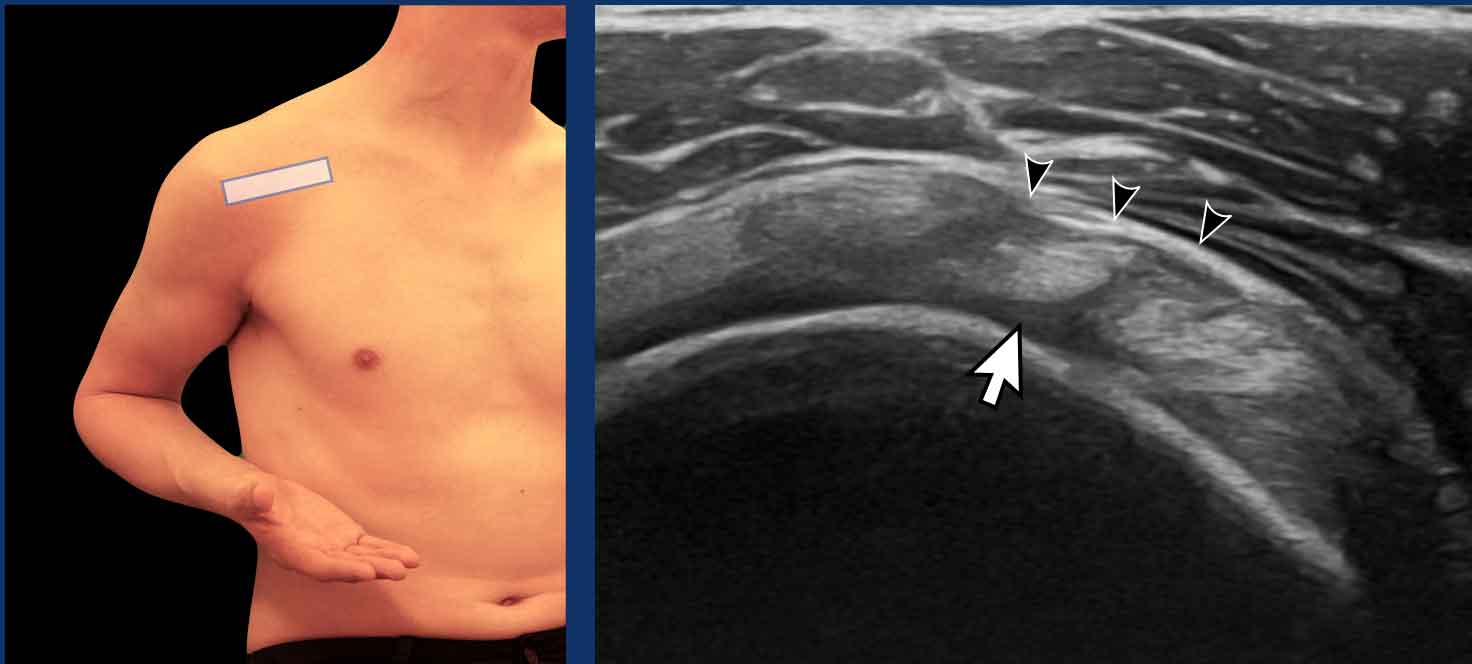
When the patient moves the elbow slightly backward while maintaining forearm supination, the intra-articular portion of the biceps tendon within the rotator cuff interval becomes more clearly visualized. This positioning is referred to as the Jugger’s position (see figure).Khi bệnh nhân di chuyển khuỷu tay hơi về phía sau trong khi vẫn duy trì tư thế ngửa cẳng tay, phần trong khớp của gân cơ nhị đầu trong khoảng chóp xoay sẽ được nhìn thấy rõ hơn Vị trí này được gọi là vị trí của Jugger (xem hình).
Image
Transverse view of the rotator cuff interval.
The LHB (arrow) is located between the subscapularis tendon anteriorly and the supraspinatus tendon posteriorly.
The LHB is covered by the coracohumeral ligament (arrowheads).Hình ảnh
Mặt cắt ngang của khoảng chóp xoay.
LHB (mũi tên) nằm giữa gân dưới vai trước và gân trên gai sau.
LHB được bao phủ bởi dây chằng coracohumeral (các đầu mũi tên).
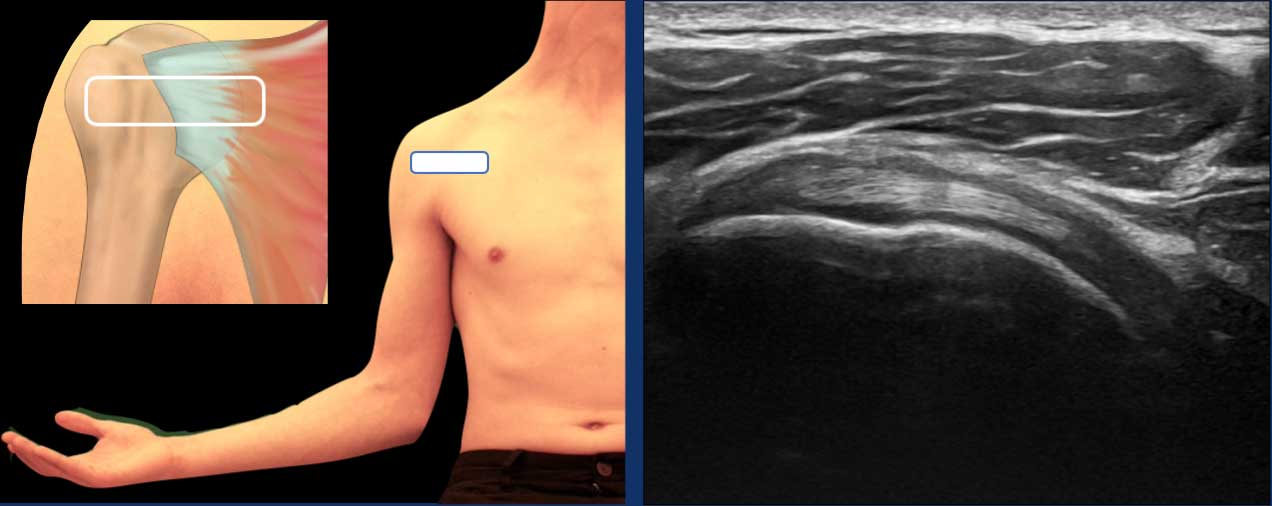
Subscapular tendonGân dưới vai
The arm is positioned alongside the trunk, with the elbow flexed at a 90º angle between the arm and forearm.
The forearm is placed in supination and external rotation.
The ultrasound probe is positioned medially to visualize the subscapularis (SSC) tendon as it passes beneath the coracoid process.Cánh tay được đặt dọc theo thân mình, với khuỷu tay gấp ở góc 90o giữa cánh tay và cẳng tay.
Cẳng tay được đặt ngửa và xoay ngoài.
Đầu dò siêu âm được đặt ở vị trí trung gian để quan sát gân dưới vai (SSC) khi nó đi qua bên dưới mỏm quạ.

Video of normal subscapular movement
During internal and external rotation of the forearm, the whole tendon should be seen sliding under the coracoid (see video).
Impingement is noted when there is incomplete or delayed passage of the tendon (see chapter on impingement).Video về vận động dưới vai bình thường
Trong quá trình xoay trong và ngoài của cẳng tay, toàn bộ gân phải được nhìn thấy trượt dưới mỏm quạ (xem video).
Chèn ép được ghi nhận khi có sự đi qua không hoàn toàn hoặc chậm trễ của gân (xem chương về chèn ép).
Double click on the video for a full screen view.Nhấp đúp vào video để xem toàn màn hình.
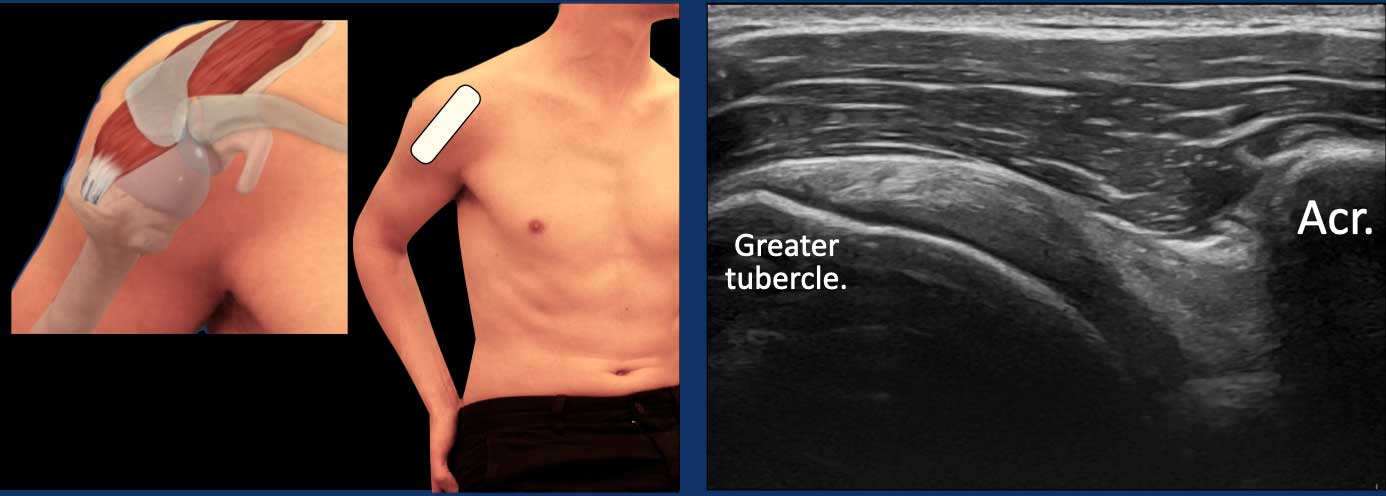

Supraspinatus tendonGân cơ trên gai
The optimal position for examining the supraspinatus tendon is the modified Crass position. In this position, the patient is instructed to place their hand on the ipsilateral hip or toward their back pocket (see figure).Vị trí tối ưu để kiểm tra gân trên gai là tư thế Crass đã được sửa đổi Ở vị trí này, bệnh nhân được hướng dẫn đặt tay lên hông cùng bên hoặc về phía túi sau của họ (xem hình).
An alternative is the Crass position, in which the patient places their arm in internal rotation behind the back.Một cách khác là tư thế Crass, trong đó bệnh nhân đặt cánh tay của họ trong vòng xoay bên trong phía sau lưng.
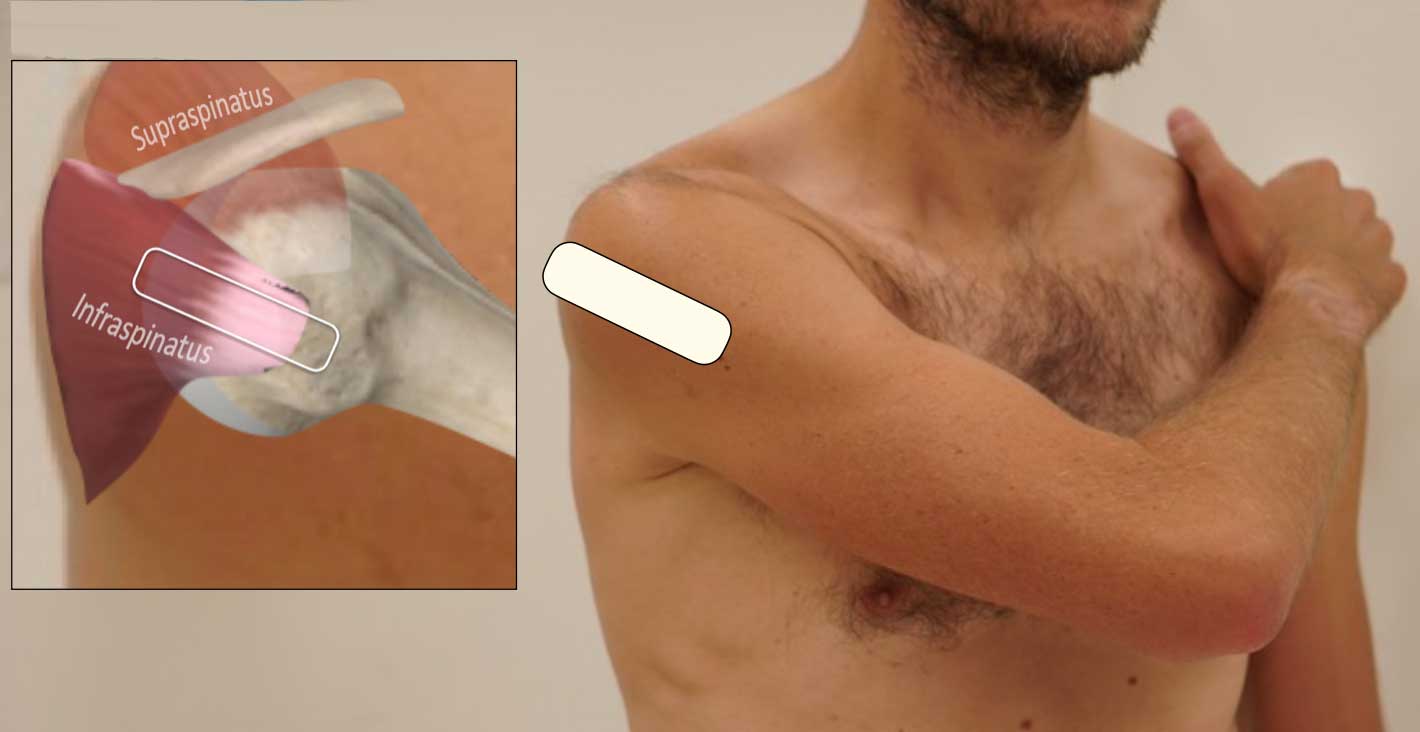
Infraspinatus tendonGân cơ dưới gai
Examining the infraspinatus tendon can be challenging due to the difficulty in distinguishing it from the supraspinatus tendon. The optimal position for visualizing the infraspinatus tendon is to have the patient place their hand on the contralateral shoulder.Khám gân cơ dưới gai có thể là một thách thức do khó phân biệt với gân cơ trên gai.Vị trí tối ưu để quan sát gân cơ này là bệnh nhân đặt tay lên vai đối diện.
Position the probe in the same orientation as for examining the supraspinatus tendon. Once the supraspinatus is in view, gradually move the probe inferiorly. A subtle gap will become evident, followed by the smaller, distinct outline of the infraspinatus tendon.Đặt đầu dò theo cùng hướng như khi kiểm tra gân trên gai. Khi đã nhìn thấy gân trên sống, di chuyển dần dần đầu dò xuống dưới. Một khoảng trống nhỏ sẽ trở nên rõ ràng, tiếp theo là đường viền nhỏ hơn, khác biệt của gân dưới gai.
Video of the infraspinatus tendon.Hình ảnh gân cơ dưới gai.
Double click on the video for a full screen view.Nhấp đúp vào video để xem toàn màn hình.
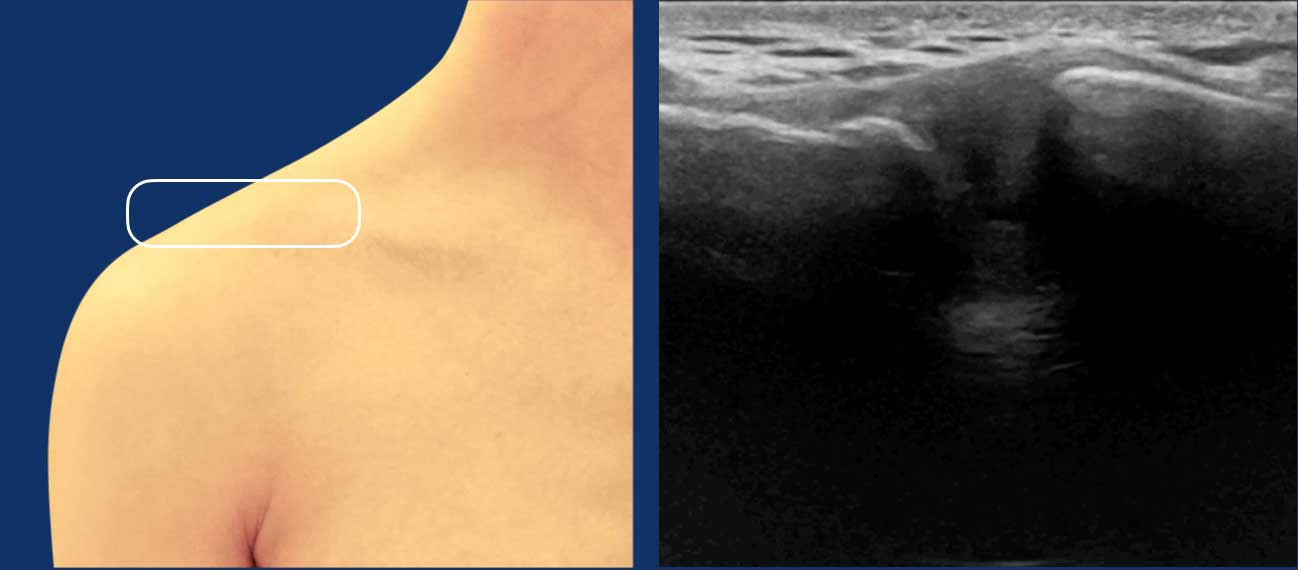
Acromioclavicular jointKhớp cùng vai đòn
The acromioclavicular joint is easily appreciated by palpating the bony projection and then placing the probe over it.
A normal acromioclavicular joint shows a smooth
contour of the bony articular surfaces.Khớp cùng vai đòn dễ dàng được đánh giá bằng cách sờ vào phần xương và sau đó đặt đầu dò lên trên nó.
Khớp cùng vai đòn bình thường cho thấy một đường viền mịn của bề mặt khớp xương.
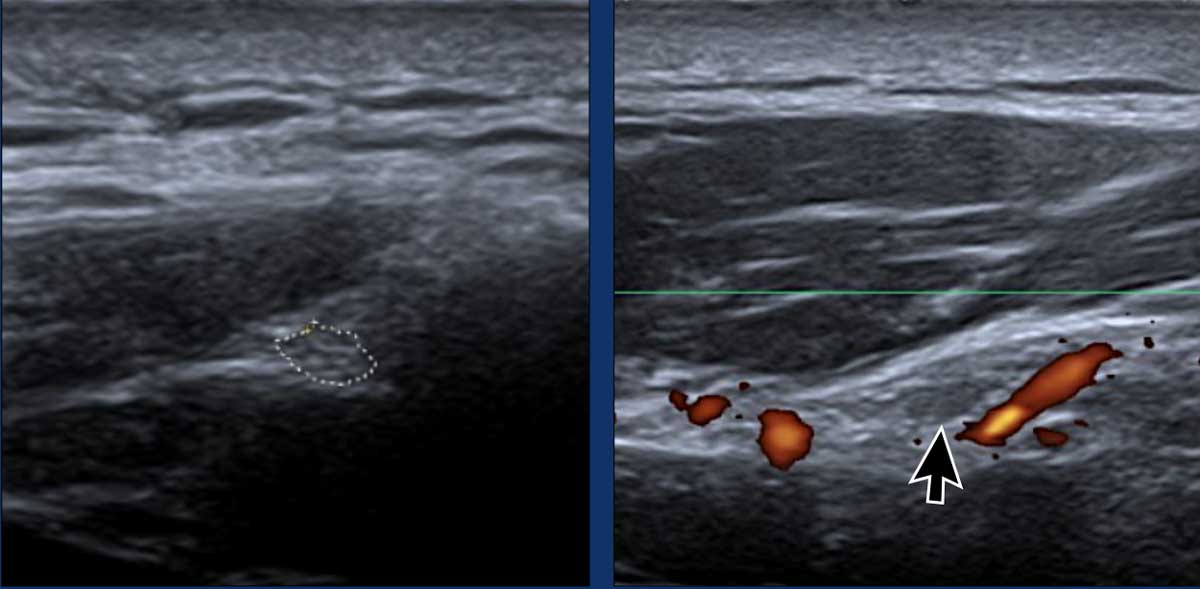
Spinoglenoid notchVết cắt gai lốm đốm
Identify the scapular spine as a hyperechoic bony landmark.
Move the probe laterally until you locate the spinoglenoid notch, which is situated between the lateral scapular spine and the glenoid process.Xác định cột sống vai là mốc xương tăng âm.
Di chuyển đầu dò sang bên cho đến khi bạn xác định được rãnh xương chũm, nằm giữa xương vai bên và mỏm ức.
The
suprascapular nerve appears as a hypoechoic tubular structure with a fascicular pattern (arrow).
Power Doppler can be beneficial to trace the suprascapular vessels in order to find the nerve.Dây thần kinh trên vai có dạng cấu trúc ống giảm âm với hình dạng cân (mũi tên).
Power Doppler có thể có lợi để theo dõi các mạch máu trên vai để tìm ra dây thần kinh.
Examine for ganglion cysts, which may appear as hypoechoic, fluid-filled structures compressing the suprascapular nerve.
These cysts are often associated with tears of the posterosuperior glenoid labrum.Kiểm tra các nang hạch, có thể xuất hiện dưới dạng giảm âm, các cấu trúc chứa đầy dịch chèn ép dây thần kinh trên vai.
Các nang này thường liên quan đến nước mắt của sụn viền ổ chảo sau trên.
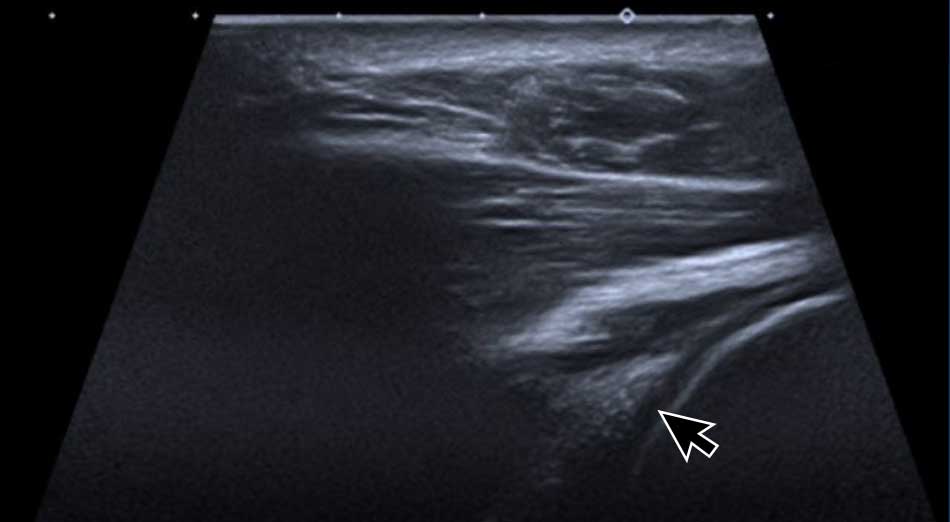
Posterior labrum and glenohumeral jointKhớp sau cánh tay và khớp ức
The posterior labrum can be examined by placing the probe
at the posterior aspect of the glenohumeral articulation.
The
labrum is seen as a triangular echogenic structure, which is more echogenic than the
adjacent cartilage (arrow).Có thể kiểm tra xương ức sau bằng cách đặt đầu dò ở mặt sau của khớp ổ chảo cánh tay.
Xương ức được xem như là một cấu trúc echogenic hình tam giác, có nhiều echogeic hơn sụn liền kề (mũi tên).
PathologyBệnh lý
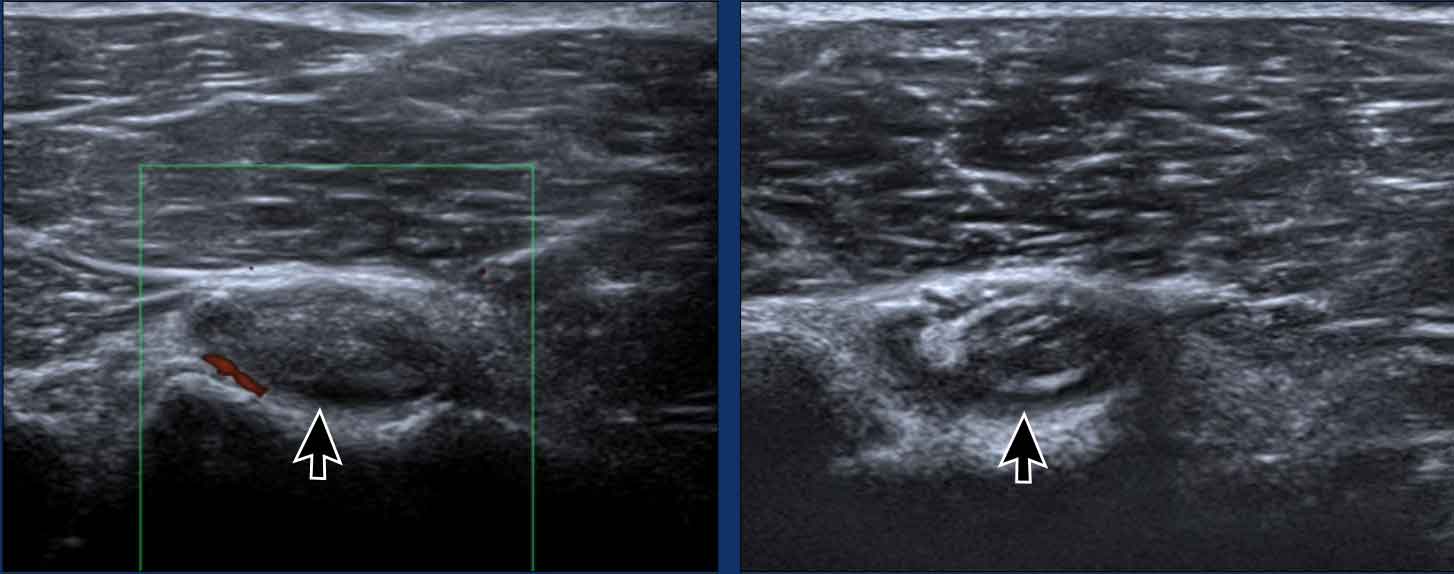
Biceps tendinopathyBệnh lý gân cơ nhị đầu
Images
Two examples of a thickened long head of the biceps tendon.
Notice the irregular echo-pattern especially on the image on the right.
There is hypervascularity and some surrounding fluid (arrows).Hình ảnh
Hai ví dụ về một đầu dài của gân cơ nhị đầu.
Chú ý đến hình ảnh siêu âm không đều, đặc biệt là trên hình ảnh bên phải.
Có tăng sinh mạch máu và một số dịch xung quanh (các mũi tên).
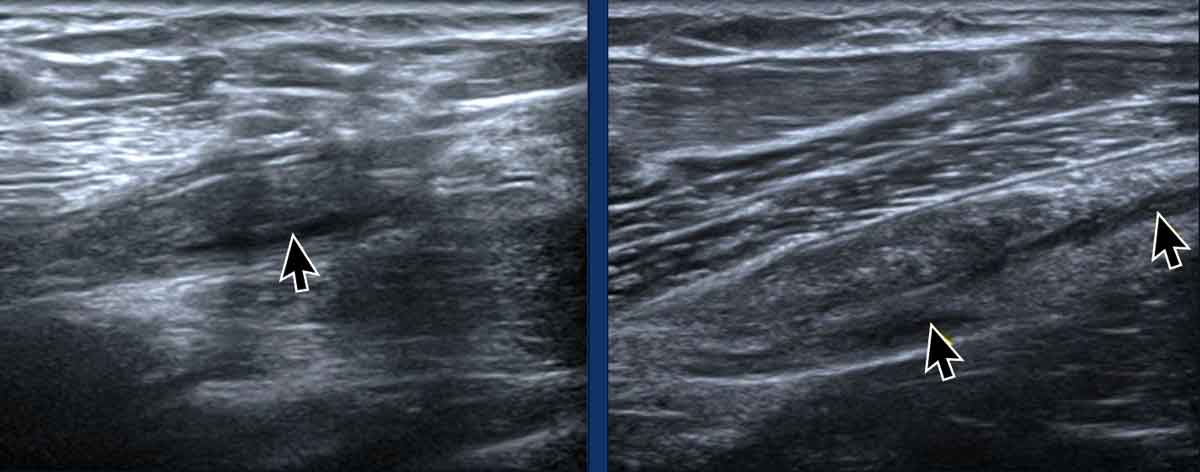
Tear of the long head of the biceps (LHB)
The most common site of injury to the LHB is at the myotendinous junction and the adjacent portion of the tendon.
LHB tears are readily identified on ultrasound as anechoic fluid disrupting the continuity of the muscle fibers.
The echogenicity of the fluid varies depending on the chronicity of the injury:Xé rách đầu dài cơ nhị đầu (LHB)
Vị trí tổn thương phổ biến nhất của LHB là ở chỗ nối cơ và phần liền kề của gân.
Rách LHB dễ dàng được xác định trên siêu âm là dịch trống âm làm gián đoạn sự liên tục của các sợi cơ.
Tính gây tiếng vang của dịch thay đổi tuỳ thuộc vào mức độ mạn tính của chấn thương:
- Acute tears typically appear as anechoic fluid.Nước mắt cấp tính thường xuất hiện dưới dạng dịch trống âm.
- Chronic tears may demonstrate echogenic debris or reflective echoes within the fluid.
Rách mạn tính có thể cho thấy các mảnh vỡ phản xạ hoặc phản xạ phản xạ trong dịch.
Images
The accompanying examples illustrate tears at the myotendinous junction of the LHB. The tears appear completely anechoic, consistent with acute injuries.Hình ảnh
Các ví dụ kèm theo minh hoạ nước mắt ở chỗ nối cơ của LHB. Nước mắt xuất hiện hoàn toàn trống âm, phù hợp với các tổn thương cấp tính.
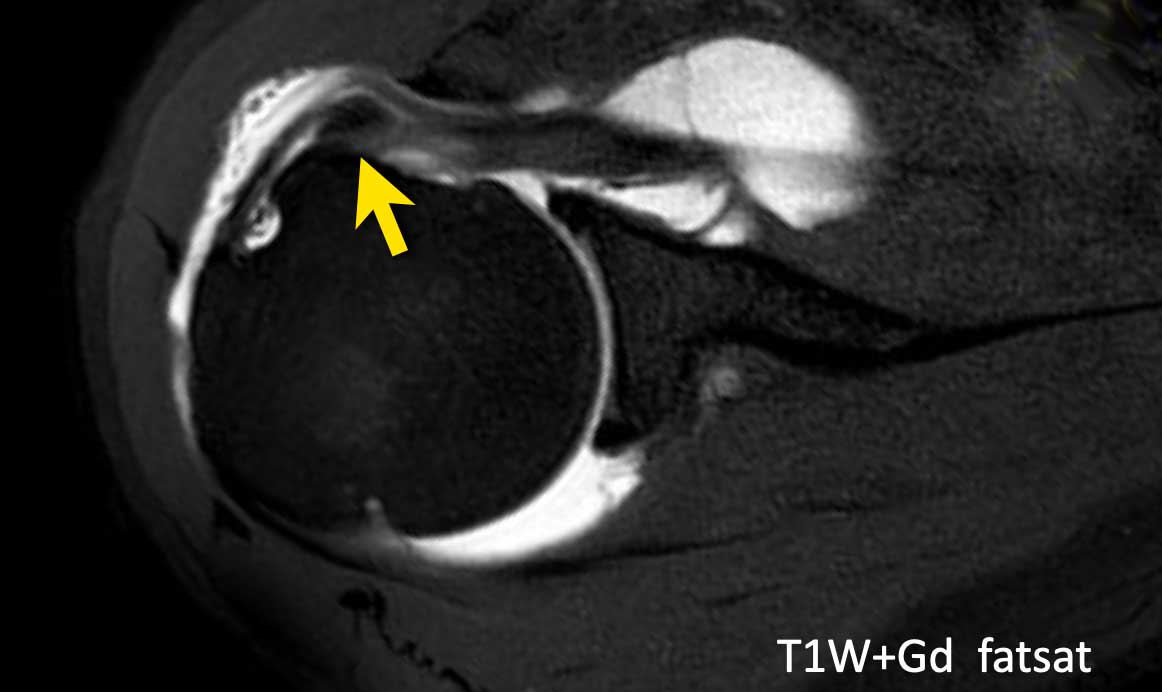
Biceps tendon dislocationTrật gân cơ nhị đầu
The long head of the biceps (LHB) tendon is normally located centrally within the bicipital groove. An abnormal, eccentric, or displaced positioning of the tendon may indicate laxity or rupture of the biceps pulley.Đầu dài của gân cơ nhị đầu (LHB) thường nằm ở trung tâm trong rãnh cơ nhị đầu. Việc định vị gân bất thường, lệch tâm hoặc di lệch có thể cho thấy sự lỏng lẻo hoặc vỡ của ròng rọc cơ nhị đầu
Imaging Findings
MR Arthrography with Axial T1-Weighted Fat-Suppressed Image: The biceps tendon is medially displaced within the subscapularis tendon, as indicated by the arrow.Hình ảnh học
Chụp cộng hưởng từ khớp vai với trục xung T1W xóa mỡ Hình ảnh: Gân cơ nhị đầu nằm trong gân dưới vai, như chỉ ra bởi mũi tên.
Continue with ultrasound images...Tiếp tục với hình ảnh siêu âm...
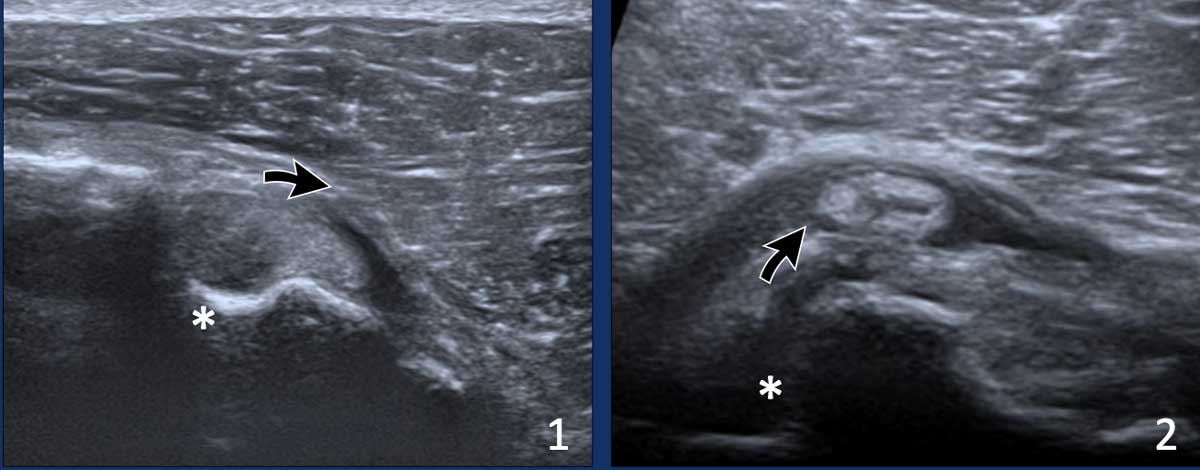
ImagesHình minh họa
- Eccentric position of the long head of the biceps tendon due to laxity of the biceps pulley.Vị trí lệch tâm của đầu dài gân cơ nhị đầu do sự lỏng lẻo của ròng rọc cơ nhị đầu.
- Dislocation of the biceps tendon. Notice the empty bicipital groove (asterix)Trật khớp gân cơ nhị đầu Chú ý rãnh cơ nhị đầu rỗng (asterix)
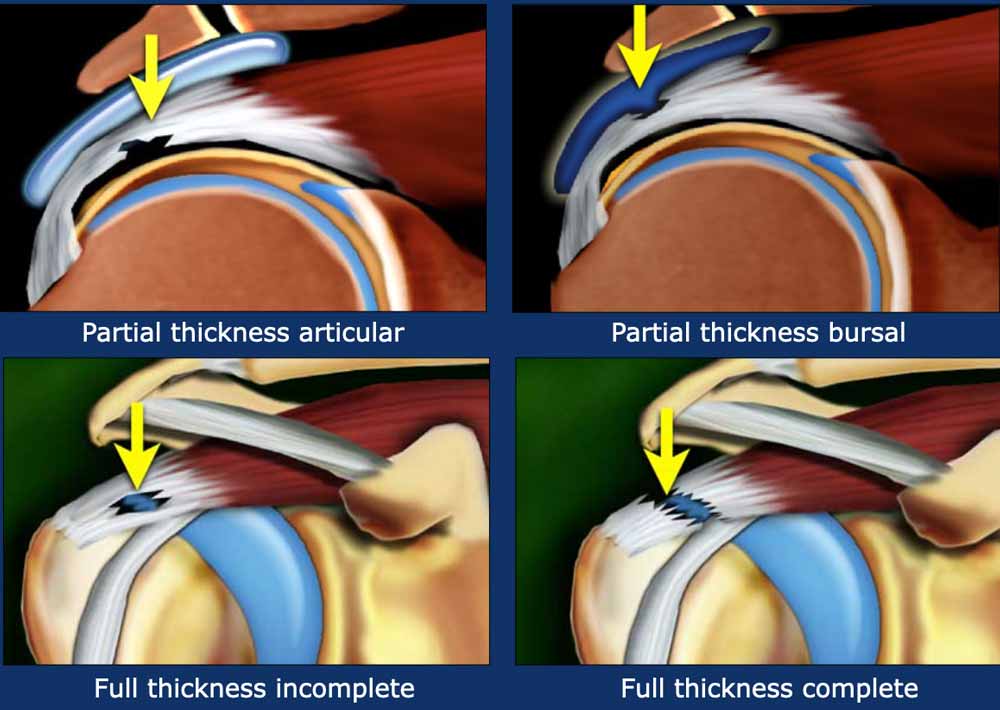
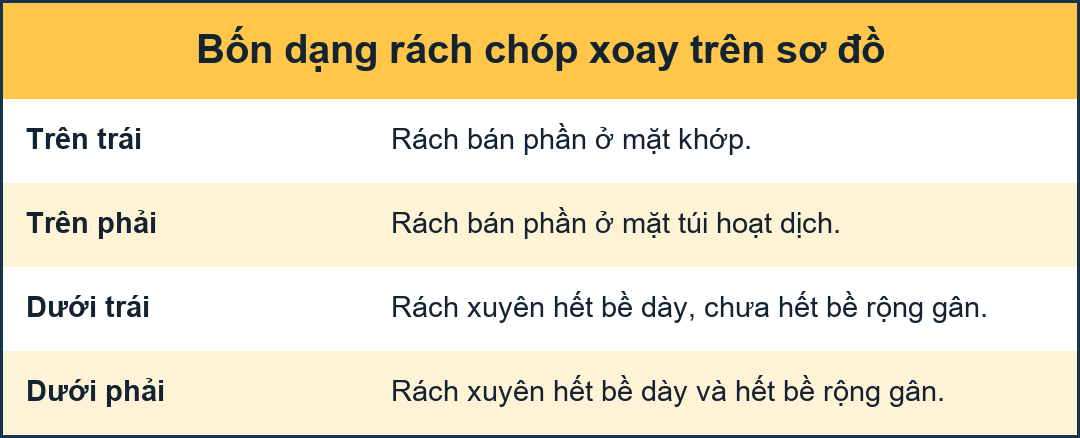
Rotator cuff tearsNước mắt chóp xoay
Partial thickness tears
Partial thickness tears involve only a part of the tendon and do not involve the full thickness.
It can be located on the articular or on the bursal side (figure).
An intrasubstance tear is also a partial thickness tear.Độ dày một phần
Rách một phần độ dày chỉ liên quan đến một phần của gân và không liên quan đến độ dày đầy đủ.
Nó có thể nằm ở khớp hoặc ở phía bao hoạt dịch (hình).
Rách nội chất cũng là rách một phần bề dày.
Full thickness tears
Full thickness tears can be complete or may involve only a part of a tendon.
This is called an incomplete full-thickness tear and is just like a hole in a tendon (figure).Nước mắt toàn bộ độ dày
Rách toàn bộ bề dày có thể hoàn toàn hoặc có thể chỉ liên quan đến một phần của gân.
Đây được gọi là rách toàn bộ không hoàn toàn và giống như một lỗ trên gân (hình).
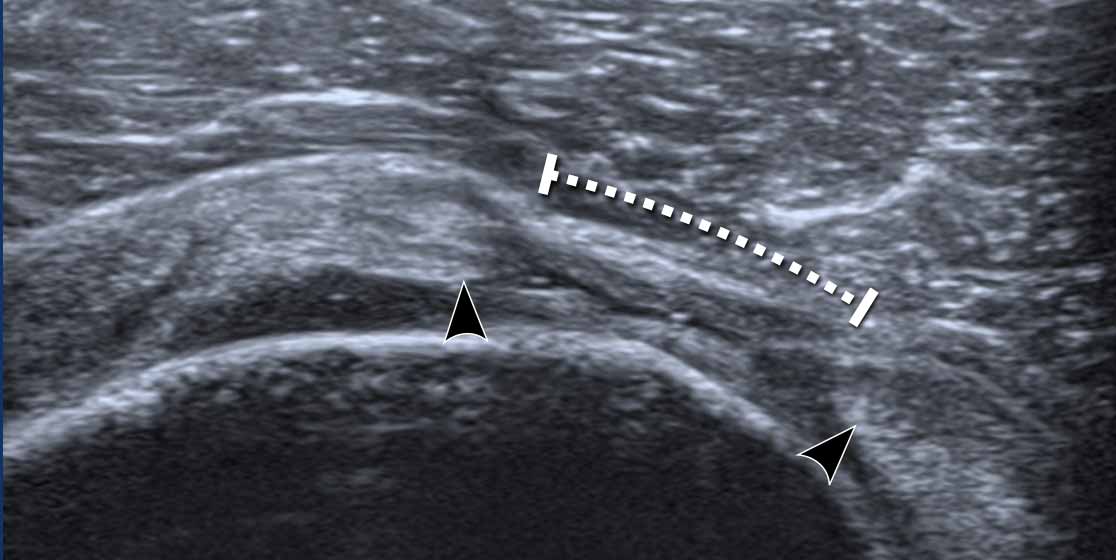
Full thickness tearsNước mắt toàn bộ độ dày
This image shows a complete full thickness tear of the supraspinatus tendon.
There is a small hypoechoic fluid collection.
Both tendon edges are blunt and retracted (arrowheads).Hình ảnh này cho thấy một vết rách hoàn toàn của gân trên gai.
Có một lượng nhỏ dịch giảm âm.
Cả hai gân đều bị cùn và co rút lại (các đầu mũi tên).
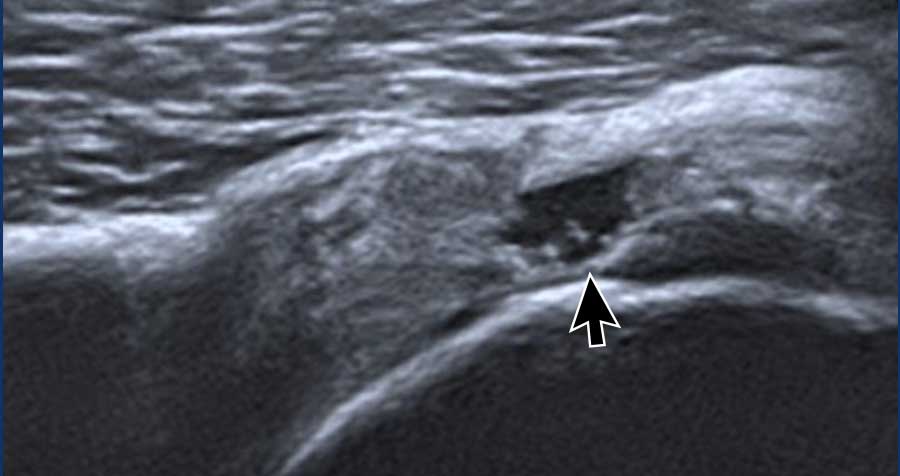
Here another example of a ful thickness tears of the supraspinatus tendon.
The gap is filled with some fluid from the glenohumeral joint (arrow)Đây là một ví dụ khác về đứt gân cơ trên gai.
Khoảng trống được lấp đầy bởi một số dịch từ khớp ổ chảo cánh tay (mũi tên)
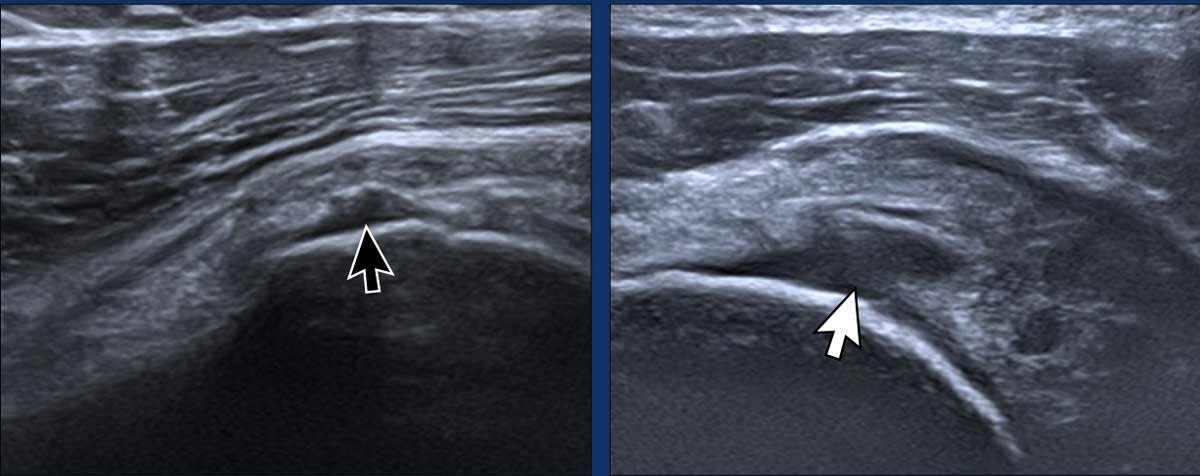
Partial thickness tearsĐộ dày một phần
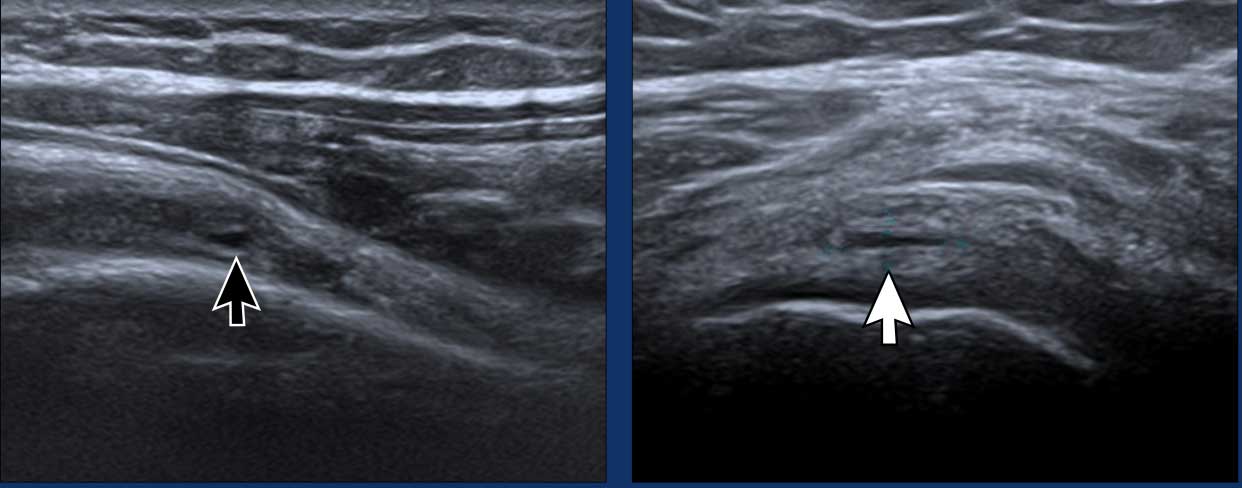
Here two examples of a partial tear on the articular side.Dưới đây là hai ví dụ về một vết rách một phần ở bên khớp.
Intrasubstance tearsNước mắt nội chất
Intrasubstance tears are partial-thickness tears that do not extend to either the articular or bursal surfaces of the tendon.Rách nội chất là những vết rách một phần không lan đến mặt khớp hoặc mặt bao của gân.
Images
The images demonstrate two examples of small intrasubstance tears.Hình ảnh
Các hình ảnh cho thấy hai ví dụ về các vết rách nội tại nhỏ.
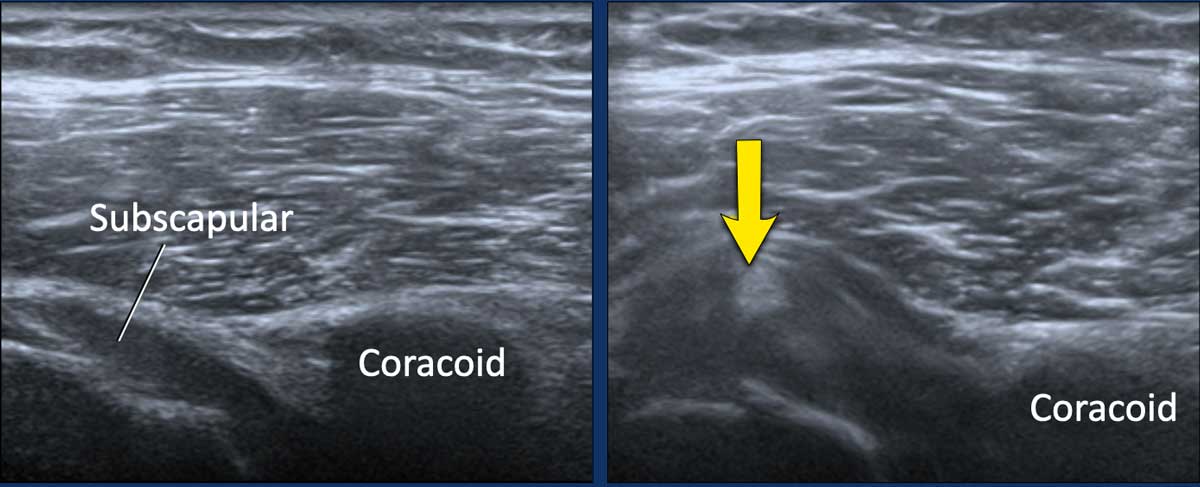
 Image during exoratation (left) and endorotation (right)Hình ảnh trong quá trình lột da (trái) và lột da(phải)
ImpingementTrang chủ
During endorotation a normal subscapular tendon should show almost complete passage underneath the coracoid process.
Impingement is suspected when a residual portion of the tendon is still visible during maximum endorotation.Trong quá trình nội soi, một gân dưới vai bình thường sẽ cho thấy gần như hoàn toàn đi qua bên dưới mỏm quạ.
Nghi ngờ có dấu hiệu chèn ép khi vẫn còn thấy phần còn lại của gân trong quá trình nội soi tối đa.
Images
During endorotation there is incomplete passage under the coracoid and buckling of the subscapular tendon.Hình ảnh
Trong quá trình nội mạc có sự đi qua không hoàn toàn dưới mỏm quạ và sự uốn cong của gân dưới vai.
Video of subscapular impingement.
Video chụp động tác chèn ép dưới vai.
Double click on the video for a full screen view.
Notice the limited range of motion.Nhấp đúp vào video để xem toàn màn hình.
Lưu ý tầm vận động giới hạn.
This video is of a 58-year-old female experiencing severe pain and limited movement in her shoulder.
In full external rotation, a large subcoracoid bursa bulges over the subscapular tendon.Video này là của một phụ nữ 58 tuổi bị đau dữ dội và hạn chế vận động ở vai.
Trong xoay ngoài hoàn toàn, một bao hoạt dịch dưới mỏm quạ lớn phình ra trên gân dưới vai.
Double click on the video for a full screen view.
Notice the limited range of motion.Nhấp đúp vào video để xem toàn màn hình.
Lưu ý tầm vận động giới hạn.
TendinopathyBệnh lý gân
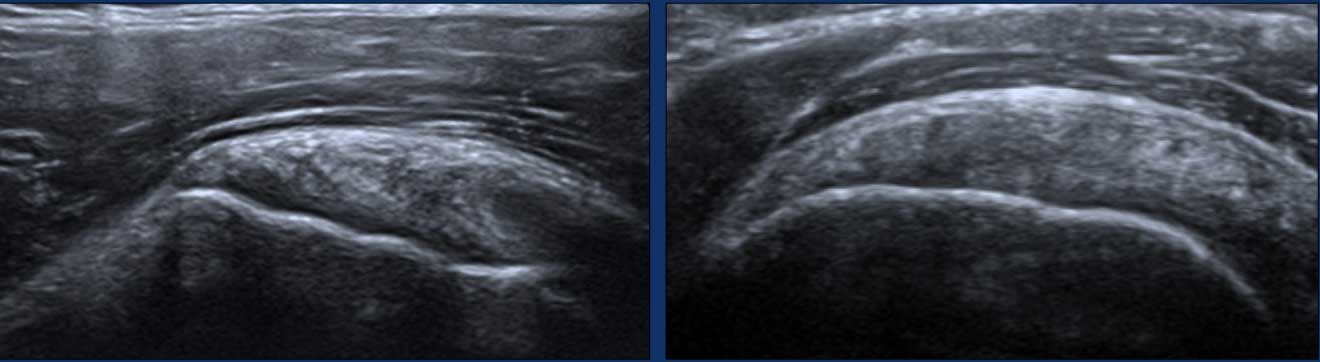
The term tendinopathy is used rather than tendinitis because there is no active inflammation, but instead it is a degenerative process with mucoid degeneration.
The tendon is frequently thickened and may show hypoechoic striated areas.Thuật ngữ bệnh lý gân được sử dụng thay vì viêm gân vì không có viêm hoạt động, nhưng thay vào đó là một quá trình thóai hóa với thóai hóa niêm mạc.
Gân thường dày lên và có thể cho thấy các vùng có vân giảm âm.
Images
Thickened supraspinatus tendon with an inhomogeneous echo pattern.Hình ảnh
Gân trên gai dày lên với hình ảnh siêu âm không đồng nhất.
Calcific tendinopathy
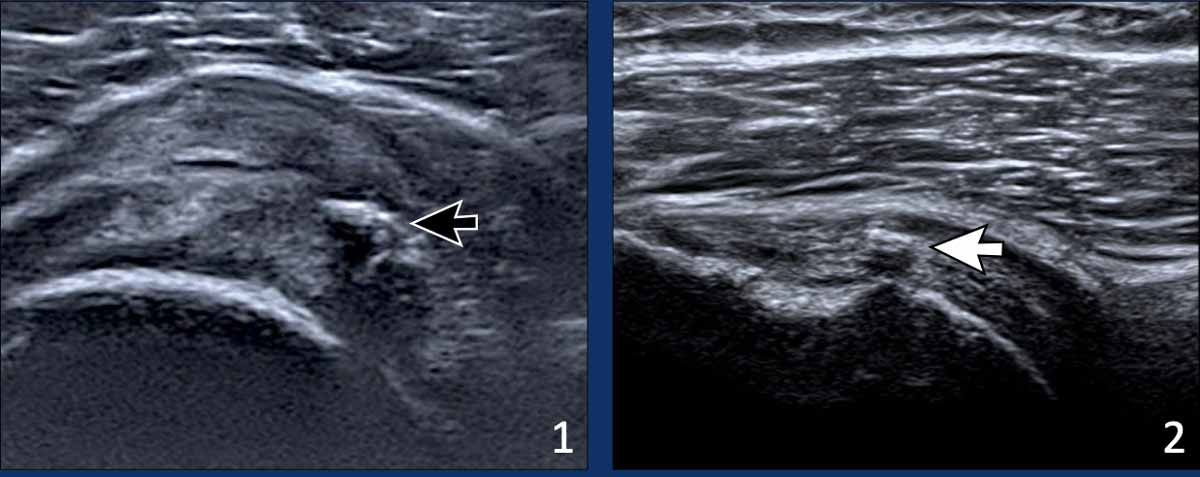
Calcific tendinopathy occurs when calcium deposits accumulate within the tendons. While this condition can affect tendons throughout the body, it most frequently involves the rotator cuff tendons of the shoulder. These calcium deposits may become inflamed, leading to pain.Bệnh lý gân Calcific
Bệnh gân do canxi xảy ra khi canxi lắng đọng trong gân Mặc dù tình trạng này có thể ảnh hưởng đến các gân trên khắp cơ thể, nhưng nó thường liên quan đến gân chóp xoay của vai Những lắng đọNG canxi này có thể bị viêm, dẫn đến đau.
Imaging Findings:Kết quả hình ảnh:
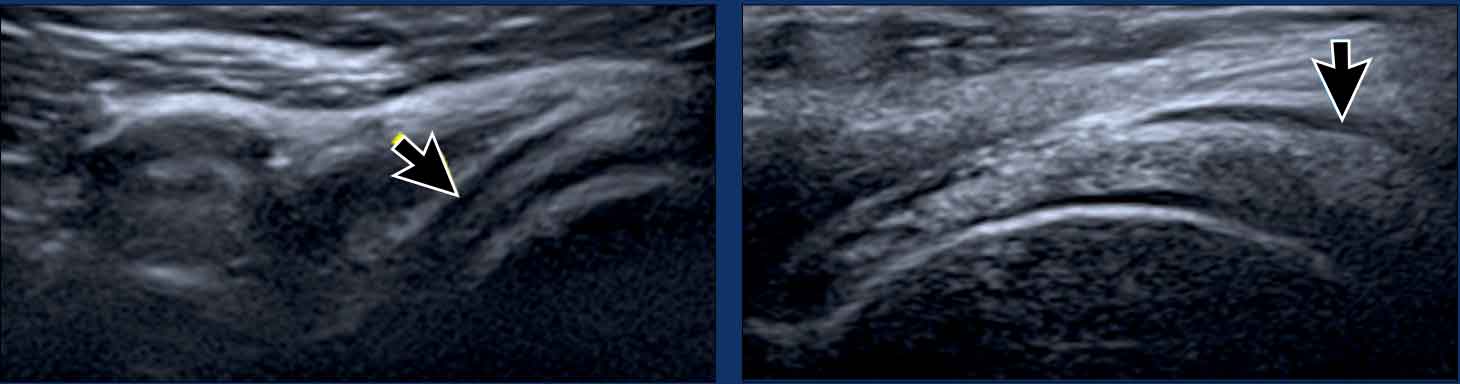
- Significant thickening of the supraspinatus tendon with large calcifications producing an extensive posterior acoustic shadow.Dày gân cơ trên gai với kích thước vôi hóa lớn tạo ra bóng sau rộng.
- A small calcification observed within the supraspinatus tendon.Một vôi hóa nhỏ được quan sát thấy trong gân cơ trên gai.
BursitisViêm bao hoạt dịch
The normal bursal space is collapsed and barely distinguishable by ultrasound (arrows). Không gian bao hoạt dịch bình thường bị xẹp và hầu như không thể phân biệt được bằng siêu âm (các mũi tên).
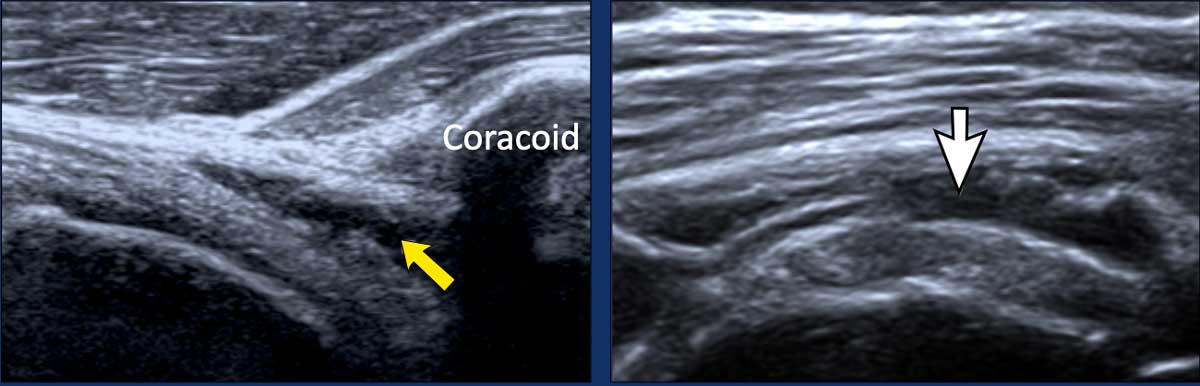
Acute bursitis appears sonographically as
distension of the bursa (yellow arrow).
Chronic bursitis may
show a thick wall (white arrow). Viêm bao thanh dịch cấp tính xuất hiện trên siêu âm như là sự căng giãn của bao thanh dịch (mũi tên màu vàng).
Viêm bao thanh dịch mạn tính có thể có thành dày (mũi tên trắng).
AC pathologyBệnh lý mạch vành
Osteoarthritis
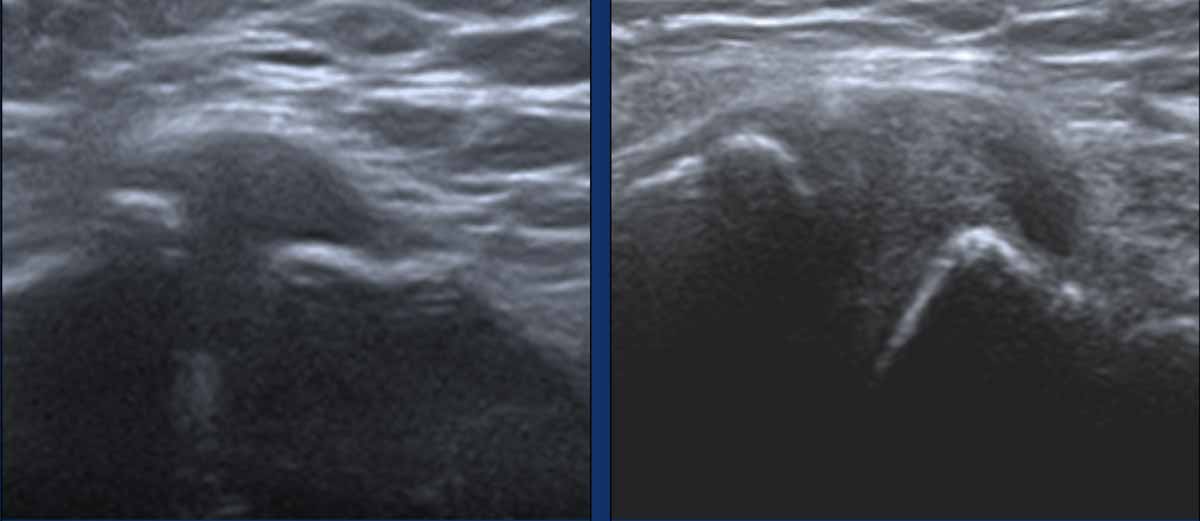
Diagnosing symptomatic osteoarthritis of the acromioclavicular joint can be difficult, as radiographic and ultrasound findings of joint degeneration are commonly seen in adults and have a poor correlation with clinical symptoms.Thóai hóa khớp
Chẩn đoán thóai hóa khớp cùng đòn có triệu chứng có thể khó khăn, vì các dấu hiệu trên X quang và siêu âm của thóai hóa khớp thường thấy ở người lớn và có mối tương quan kém với các triệu chứng lâm sàng.
Images
Osteoarthritis of the AC joint with cortical irregularity and bulging of the capsule. Hình ảnh
Thóai hóa khớp thái dương hàm với bất thường vỏ xương và phồng nang.
AC-arthritis
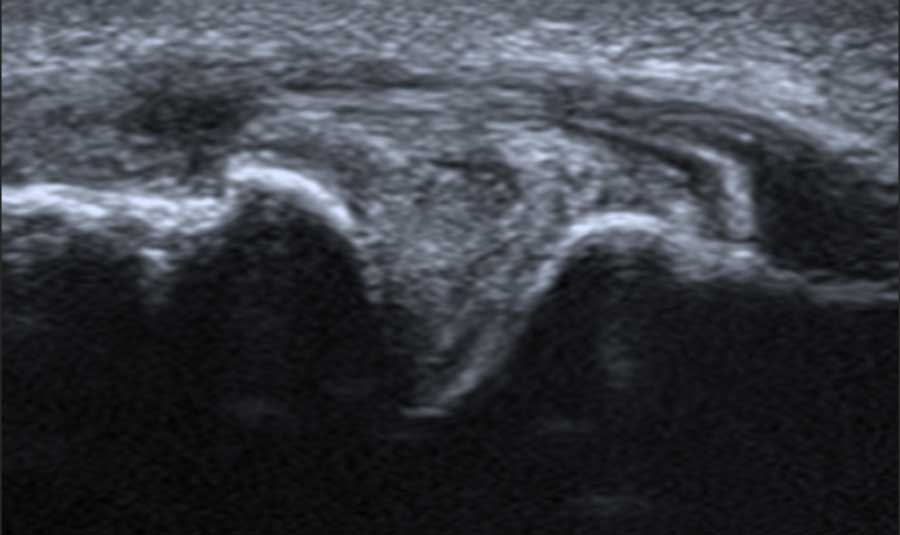
This image is of a 19-year-old male athlete who sustained an injury during a wrestling match.
There were no signs of septic arthritis and he was diagnosed with post-traumatic arthritis.
He improved with anti-inflammatory medication and rest.Viêm khớp dạng thấp
Hình ảnh này là của một vận động viên nam 19 tuổi bị chấn thương trong một trận đấu vật.
Không có dấu hiệu viêm khớp nhiễm khuẩn và được chẩn đoán viêm khớp sau chấn thương.
Bệnh nhân cải thiện với thuốc kháng viêm và nghỉ ngơi.
ReferencesTài liệu tham khảo
- Musculoskeletal Ultrasound Technical Guidelines of the European Society of MusculoSkeletal Radiology Hướng dẫn kỹ thuật siêu âm cơ xương của Hiệp hội X quang cơ xương châu Âu
- Radiology Key - Shoulder Ultrasound Chẩn đoán hình ảnh - Siêu âm vai